Hysterectomy for Endometriosis: What It Can and Can’t Do
Many women with endometriosis are told, at some point, that a hysterectomy will “fix it.” The truth is more complicated. Removing the uterus can help some people a great deal, but endometriosis grows mostly outside the uterus, so a hysterectomy on its own does not remove the disease.[1][2] What matters most is what else is done during the operation, whether the ovaries are kept, and how experienced the surgeon is with endometriosis.
This guide explains where endometriosis grows, what a hysterectomy can and cannot do for it, what the research says about pain coming back, and how to find a surgeon who can treat the disease properly. If you are still exploring the basics, start with our guide to what a partial hysterectomy is.
Key points
- Endometriosis affects about 1 in 10 women of reproductive age. There is no treatment that cures it for certain.[1]
- A hysterectomy removes the uterus, not the endometriosis around it. European guidelines say women should be told that hysterectomy “will not necessarily cure the symptoms or the disease.”[2]
- When a hysterectomy is done for endometriosis, the visible endometriosis lesions should be removed in the same operation.[2]
- Keeping the ovaries protects long-term health but raises the chance that pain returns. This trade-off depends a lot on your age.[7][8][10]
- Deep endometriosis (bowel, bladder, ureters, nerves) should be treated at a center with real expertise in this disease.[2][3]
What endometriosis is, and where it grows
Endometriosis is a long-term inflammatory condition in which tissue similar to the lining of the uterus grows outside it. The international definition agreed in 2021 by the main gynecologic surgery and fertility societies describes it as lining-like tissue found outside the endometrium and the uterine muscle, usually with inflammation around it.[15] These patches (called lesions or implants) react to hormones, cause inflammation and scar tissue, and can make organs stick together. The most common symptoms are very painful periods, pelvic pain between periods, pain during or after sex, pain with bowel movements or urination, fatigue and difficulty getting pregnant.[1]
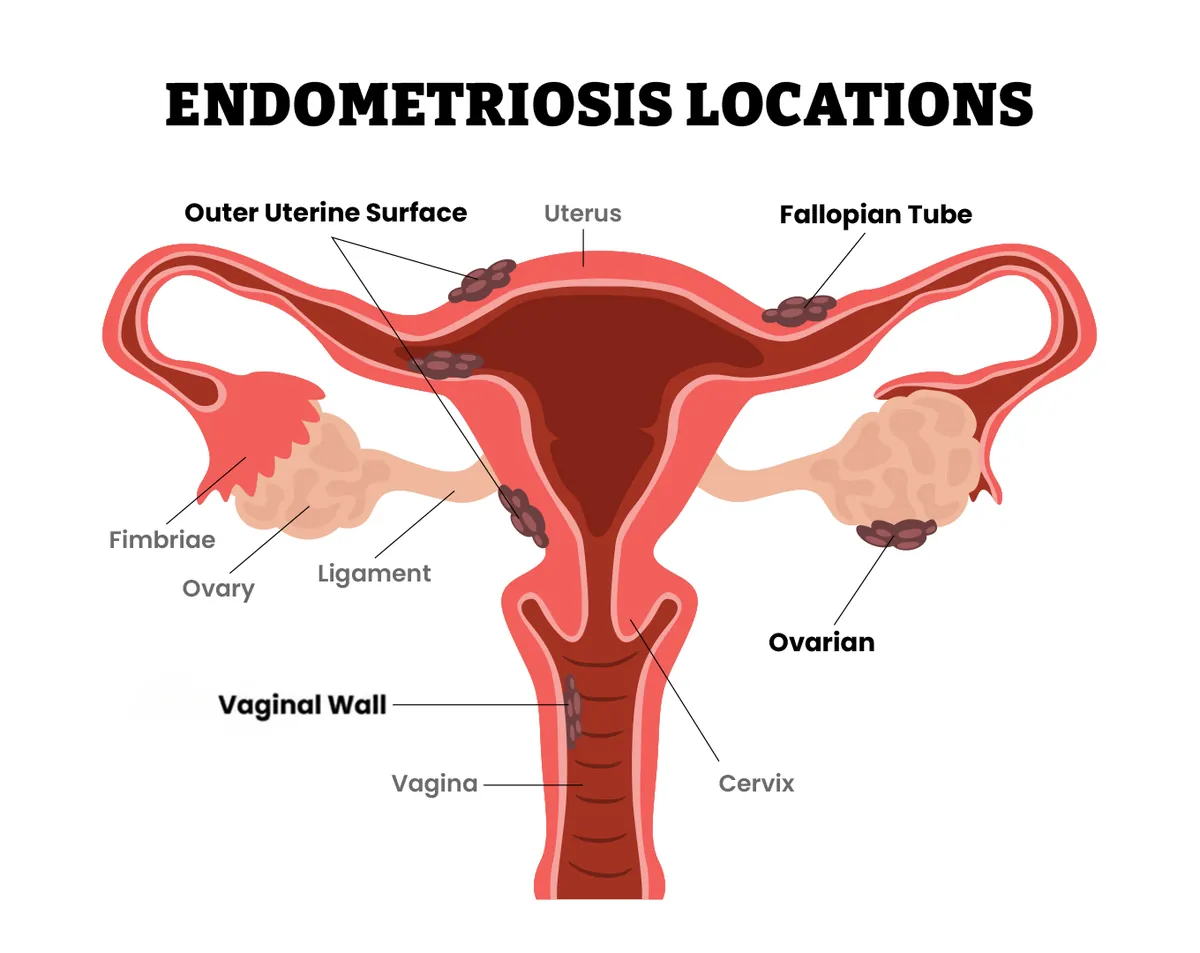
Specialists usually describe three main forms, and many women have more than one at the same time:[2][5]
- Superficial peritoneal endometriosis: flat or small lesions on the peritoneum, the thin membrane that lines the pelvis and covers the organs.
- Ovarian endometriomas: cysts inside the ovary filled with old, dark blood, often called “chocolate cysts.” Our guide to ovarian cysts after hysterectomy explains why the ovaries can still form cysts once the uterus is gone.
- Deep endometriosis: lesions that grow more than 5 mm below the surface and can invade the ligaments behind the uterus, the area between the vagina and the rectum, the bowel, the bladder, the ureters (the tubes that carry urine from the kidneys) and pelvic nerves. Bowel involvement is estimated in 8 to 12% of women with endometriosis.[3]
Less often, endometriosis is found outside the pelvis. The most typical site is the diaphragm, the muscle under the lungs, where it can cause shoulder or chest pain around the period and, rarely, a collapsed lung. Up to 80% of women with endometriosis in the chest also have it in the pelvis.[4][5]
Adenomyosis: the related condition that lives inside the uterus
Adenomyosis is a related condition in which lining-like tissue grows into the muscle wall of the uterus. It causes heavy, painful periods and often exists together with endometriosis.[5] Because adenomyosis is inside the uterus, removing the uterus does remove it: specialists describe hysterectomy as the only definitive cure for adenomyosis, although it is not right for everyone.[20] This is one reason a hysterectomy helps some women with endometriosis more than others: part of their pain may be coming from adenomyosis.
Why removing the uterus does not remove endometriosis
A hysterectomy takes out the uterus. The lesions on the peritoneum, the ovaries, the bowel, the bladder or the nerves stay where they are unless the surgeon finds them and removes them. The World Health Organization puts it plainly: hysterectomy “is not a cure, and some patients have symptoms that remain.”[1]
Specialist centers say the same thing. The Bucharest Endometriosis Center in Romania, which treats complex and deep endometriosis, lists “hysterectomy or induced menopause is an effective treatment” among the common myths about the disease. Its explanation: lesions left in the pelvis are not removed by stopping periods, and endometriosis tissue can produce some of its own estrogen, so lowering hormone levels does not reliably shrink it.[5][6][12] Laboratory research supports that last point: endometriosis tissue contains the full set of enzymes, including aromatase, needed to make estradiol on its own.[14]
This does not mean hysterectomy has no place. It means the question to ask is not “Should I have a hysterectomy?” but “What exactly will be removed, and by whom?”
When a hysterectomy may be considered
The 2022 guideline of the European Society of Human Reproduction and Embryology (ESHRE), one of the most complete reviews of the evidence, says doctors can consider hysterectomy, with or without removing the ovaries, for women who no longer wish to become pregnant and whose symptoms have not improved with more conservative treatments. It adds three conditions:[2]
- Women should be told that hysterectomy will not necessarily cure the symptoms or the disease.
- When a hysterectomy is done, all visible endometriosis lesions should be removed at the same time.
- A total hysterectomy (uterus and cervix) is preferred over leaving the cervix.
In practice, the women most likely to benefit are those who have finished having children, whose pain is closely tied to their periods, who have heavy bleeding or adenomyosis, or who have already had surgery to remove endometriosis and still have symptoms. Our article on the signs and reasons you might need a hysterectomy covers the other common reasons, and partial vs total hysterectomy explains the difference between keeping and removing the cervix.
What the research says about results
There are no large trials comparing every option head to head, but several long-term studies give a useful picture:
- Cleveland Clinic, 7-year follow-up (2008): among women who had laparoscopic removal of endometriosis while keeping the uterus and ovaries, 44.6% had needed no further surgery after 7 years. After hysterectomy with the ovaries kept, the figure was 77.0%, and after hysterectomy with both ovaries removed, 91.7%. In women aged 30 to 39, removing the ovaries did not make a significant difference.[7]
- Johns Hopkins (1995): women who kept ovarian tissue at hysterectomy had about 6 times the risk of pain coming back and 8 times the risk of another operation compared with women whose ovaries were removed. The study was small (29 women kept their ovaries).[8]
- Ontario, Canada (2021): in nearly 85,000 women followed for a median of 10 years, only a few of those who had a hysterectomy needed repeat surgery, while up to 1 in 4 who had smaller conservative surgery and 1 in 5 who had major conservative surgery with the ovaries kept needed another endometriosis operation.[9]
Two cautions. First, “no further surgery” is not the same as “no pain”: these studies count operations, which is easier to measure than quality of life. Second, the results depend on how thoroughly the endometriosis itself was removed. The Bucharest center reports that when excision is done completely, recurrence falls below 20%, with ovarian endometriomas being the least predictable.[5]
Keeping or removing the ovaries
This is often the hardest part of the decision. The ovaries make the estrogen that can keep remaining endometriosis active, which is why removing them lowers the chance of pain coming back.[7][8] But removing both ovaries before natural menopause causes sudden (surgical) menopause and has long-term costs. In the Nurses’ Health Study, which followed almost 30,000 women for 24 years after hysterectomy for non-cancer reasons, removing both ovaries was linked to a higher risk of death from all causes and of heart disease. For women under 50 who never used estrogen therapy, the risks of death, heart disease and stroke were higher.[10]
A reasonable summary is that the closer you are to natural menopause, the more removing the ovaries tends to make sense; the younger you are, the more there is to lose. Many surgeons keep healthy ovaries in younger women and remove only the endometriosis on them. If you keep your ovaries, our guide to ovary pain after hysterectomy explains what can happen later.
Hormone therapy after surgical menopause
Having endometriosis does not mean you must go without hormone therapy after your ovaries are removed. ESHRE recommends continuing treatment after surgical menopause, using combined estrogen and progestogen therapy at least until the age of natural menopause, and avoiding estrogen-only therapy in women with a history of endometriosis.[2][17] This is different from the usual advice after hysterectomy (estrogen alone), because estrogen without a progestogen could reactivate endometriosis that was left behind. Make sure whoever prescribes your hormones knows you have had endometriosis.
Why the surgeon’s experience matters so much
Deep endometriosis can involve the bowel, bladder, ureters and nerves. Removing it safely may mean shaving a nodule off the bowel wall, removing a disc or a segment of bowel, freeing a ureter, or working near the nerves that control the bladder and bowel. ESHRE recommends that women with deep endometriosis be referred to a center of expertise, and an international expert review states that when surgery is chosen, “a complete resection by the most appropriate surgical team” is needed for the best outcome.[2][3]
What does a center of expertise look like in practice? One example is the Bucharest Endometriosis Center in Romania, founded in 2018 by Dr. Gabriel Mitroi, a gynecologic oncologist and laparoscopic and robotic surgeon, and now working within the MedLife hospital network. Women travel there from across Europe and beyond for complex surgery. According to the center:[5][11][12][13]
- Volume: in early 2025 its website listed about 400 surgeries a year, including some 250 for deep endometriosis, 150 involving the bowel and 70 bowel resections.
- A team, not a single surgeon: gynecologic surgeons work alongside colorectal and general surgeons (who also handle diaphragm endometriosis), a dedicated anesthetist and imaging specialists. The most complex operations can last 10 to 12 hours, and the center says it schedules no more than about 7 cases a week so that each takes “as long as it takes.”
- Mapping before surgery: a specialized MRI, with gel placed in the vagina and rectum to outline the walls, shows how deep the lesions go and whether the bowel needs to be resected. Ultrasound, CT, urography or cystoscopy are added when the urinary tract may be involved, so patients know before the operation what may need to be done.
- Where it finds the disease: outside the reproductive organs, the most commonly affected sites are the rectum, the sigmoid colon, the bladder, the pelvic ureters and the small intestine. The team also treats nerve endometriosis (including pudendal nerve decompression), diaphragm and chest disease, and adenomyosis.
- Technique: laparoscopic and robotic (da Vinci Xi) surgery, with excision (cutting the lesions out at their full depth) rather than ablation (burning the surface), which can leave active disease underneath.
A real experience at a center of expertise
Shared anonymously by our editor’s family. This is one family’s experience, not medical advice or a promise of results.
A few years ago, our editor went with a close family member to the Bucharest Endometriosis Center for complex endometriosis surgery and stayed in Bucharest for almost a month: consultations, tests, the specialized MRI, preparation, the operation, the hospital stay, follow-up visits and a return to the hospital. The surgery was complex and involved specialists from other fields working alongside the gynecologic surgeons. Demand was high: when it was time to book, the next three to four months were already full, so the operation was scheduled for the following year. At that time the team was operating on three to four patients a day; on the day of this operation there were four, two from Romania and two from abroad.
The family’s impression of the whole process was that it was exceptionally good. What stood out most was the level of expertise at every step, starting with the MRI: the radiologist’s reading of the scan was far more detailed than anything they had seen from leading specialists in their home country. The planning, the coordination between specialists and the follow-up after surgery were just as thorough.
In the United States: the Center for Endometriosis Care
For readers in the US, the Center for Endometriosis Care in Atlanta is one of the longest-running excision centers. It was founded in 1991 by Dr. Robert Albee and is now led by medical director Dr. Ken Sinervo, a former chair of the endometriosis special interest group of the AAGL (the main US society for minimally invasive gynecologic surgery), with his partner Dr. José Eugenio-Colón. The center says it has treated patients from more than 70 countries. According to the center:[16][17][18][19]
- It aims to excise endometriosis from every area where it is found, including outside the pelvis and on the diaphragm, while preserving healthy organs, and sends all removed tissue for biopsy to confirm the diagnosis.
- It treats related problems such as adenomyosis, fibroids and adhesions in the same operation, because endometriosis rarely comes alone.
- After excision, it reports that true recurrence of endometriosis in its patients is around 10 to 20%, and that about 15 to 20% need another operation for any reason, including problems unrelated to endometriosis.
- It notes that relief can be achieved either by excision while keeping the uterus or by excision together with hysterectomy. The key in both cases is that the endometriosis itself is removed.
You do not have to travel far to get this level of care, but these are the features worth looking for wherever you are: a surgeon who operates on endometriosis every week, a team that includes bowel and urinary specialists, detailed imaging before surgery, complete excision and biopsy of what is removed.
On excision versus ablation, the evidence for superficial disease is still limited: ESHRE says doctors “may consider” excision over ablation to reduce pain, a weak recommendation.[2] For deep disease, removing the lesions completely is what specialists aim for.[3]
Whether the operation is laparoscopic or robotic matters less than the skill and experience of the team. Our guides to laparoscopic hysterectomy and robotic hysterectomy explain how each approach works.
Questions to ask a surgeon before endometriosis surgery
- How many endometriosis operations do you do each year, and how many involve deep disease or the bowel?
- Do you excise the lesions or ablate them? Will you remove all the endometriosis you see, not only the uterus?
- What imaging will you do before surgery (specialized ultrasound or MRI) to map the disease?
- If my bowel, bladder or ureters are involved, will a colorectal surgeon or urologist be part of the operation?
- What do you recommend for my ovaries, and why, at my age?
- What happens if you find more disease than expected during the operation?
Our checklist of recommendations before your hysterectomy covers the practical side of preparing for surgery.
Options to try before a hysterectomy
Most women start with medicines, and many never need a hysterectomy. ESHRE lists these options for endometriosis pain:[2]
- Pain relievers such as NSAIDs (for example, ibuprofen).
- Combined hormonal contraceptives (pill, patch or vaginal ring).
- Progestogens, including tablets, the hormonal IUD (levonorgestrel) or the contraceptive implant.
- GnRH agonists or antagonists, which lower estrogen levels. They are usually second-line because of side effects such as hot flashes and bone loss.
Be clear about what these medicines do. They can relieve symptoms while you take them, but they do not remove the lesions, and symptoms often come back when they are stopped. Some, like GnRH drugs, can only be used for a limited time because of side effects. Excision specialists stress this point, and it is worth weighing if you have been on medication for years without real relief.[1][17]
Surgery to remove the endometriosis while keeping the uterus is another option, and the only surgical one for women who still want to become pregnant. For ovarian endometriomas, ESHRE recommends removing the cyst wall (cystectomy) rather than only draining it.[2] Note that imaging can miss endometriosis, especially the superficial kind, so a normal ultrasound or MRI does not rule it out.[2]
Recovery after hysterectomy for endometriosis
Recovery depends on how much was done. A hysterectomy alone by keyhole surgery usually means a short hospital stay and a few weeks of recovery, while surgery that also involves the bowel or urinary tract can take longer and may need a temporary drain, catheter or, rarely, a temporary stoma. Ask your surgeon what to expect for your specific operation. Our week-by-week recovery guide and our hysterectomy FAQ answer the most common questions.
When to call your doctor after surgery
Contact your surgical team or seek urgent care if you have:
- A fever of 100.4°F (38°C) or higher, or chills.
- Heavy vaginal bleeding, or discharge that smells bad.
- Belly pain that gets worse instead of better, or a swollen, hard belly with vomiting.
- Trouble passing urine, pain in your side or back, or leakage of urine or stool from the vagina.
- Pain, swelling or redness in one leg.
- Chest pain or shortness of breath: call 911.
Pain that comes back months or years later is not something you have to accept. It can be caused by remaining endometriosis, an ovary, adhesions or problems unrelated to endometriosis, and it deserves a proper evaluation, ideally by someone who specializes in the disease.
Sources
- World Health Organization. Endometriosis (fact sheet). 2025. who.int
- Becker CM, Bokor A, Heikinheimo O, et al.; ESHRE Endometriosis Guideline Group. ESHRE guideline: endometriosis. Human Reproduction Open. 2022;2022(2):hoac009. pmc.ncbi.nlm.nih.gov
- Abrão MS, Petraglia F, Falcone T, Keckstein J, Osuga Y, Chapron C. Deep endometriosis infiltrating the recto-sigmoid: critical factors to consider before management. Human Reproduction Update. 2015;21(3):329–339. pubmed.ncbi.nlm.nih.gov
- Nezhat C, Main J, Paka C, Nezhat A, Beygui RE. Multidisciplinary treatment for thoracic and abdominopelvic endometriosis. JSLS. 2014;18(3):e2014.00312. pubmed.ncbi.nlm.nih.gov
- MedLife. Bucharest Endometriosis Center (coordinated by Dr. Gabriel Mitroi). In Romanian. medlife.ro
- MedLife medical team, with Dr. Gabriel Mitroi. Chirurgia endometriozei profunde (Deep endometriosis surgery). 2023. In Romanian. medlife.ro
- Shakiba K, Bena JF, McGill KM, Minger J, Falcone T. Surgical treatment of endometriosis: a 7-year follow-up on the requirement for further surgery. Obstetrics & Gynecology. 2008;111(6):1285–1292. pubmed.ncbi.nlm.nih.gov
- Namnoum AB, Hickman TN, Goodman SB, Gehlbach DL, Rock JA. Incidence of symptom recurrence after hysterectomy for endometriosis. Fertility and Sterility. 1995;64(5):898–902. pubmed.ncbi.nlm.nih.gov
- Bougie O, McClintock C, Pudwell J, Brogly SB, Velez MP. Long-term follow-up of endometriosis surgery in Ontario: a population-based cohort study. American Journal of Obstetrics and Gynecology. 2021;225(3):270.e1–270.e19. pubmed.ncbi.nlm.nih.gov
- Parker WH, Broder MS, Chang E, et al. Ovarian conservation at the time of hysterectomy and long-term health outcomes in the Nurses’ Health Study. Obstetrics & Gynecology. 2009;113(5):1027–1037. pubmed.ncbi.nlm.nih.gov
- Bucharest Endometriosis Center. Home page (surgical volume, team and approach). Archived March 2025. web.archive.org
- Bucharest Endometriosis Center. Diagnosis and treatment. Archived May 2025. web.archive.org
- Bucharest Endometriosis Center. Our doctors. Archived March 2025. web.archive.org
- Bulun SE, Utsunomiya H, Lin Z, et al. Steroidogenic factor-1 and endometriosis. Molecular and Cellular Endocrinology. 2009;300(1-2):104–108. pubmed.ncbi.nlm.nih.gov
- International Working Group of AAGL, ESGE, ESHRE and WES; Tomassetti C, Johnson NP, Petrozza J, et al. An international terminology for endometriosis, 2021. Human Reproduction Open. 2021;2021(4):hoab029. pubmed.ncbi.nlm.nih.gov
- Center for Endometriosis Care (Atlanta). About the Center for Endometriosis Care. centerforendo.com
- Center for Endometriosis Care. LAPEX: laparoscopic excision of endometriosis. centerforendo.com
- Center for Endometriosis Care. Frequently asked questions. centerforendo.com
- Center for Endometriosis Care. Meet Dr. Ken Sinervo. centerforendo.com
- Center for Endometriosis Care. Adenomyosis. centerforendo.com
This article is for general information and is not a substitute for medical advice. Endometriosis is different in every woman, so always discuss your own situation, including what will be removed and whether to keep your ovaries, with a gynecologist experienced in endometriosis, and contact your doctor or emergency services if you are worried about any symptom.