Pictures of Hysterectomy Scars: What Each Type of Incision Looks Like and How It Heals
What your scar looks like after a hysterectomy depends mostly on one thing: how the surgery was done. An open (abdominal) operation leaves one longer scar, keyhole surgery leaves a few small ones, and a vaginal hysterectomy leaves no visible scar at all. This guide shows what each type of scar usually looks like, how it changes as it heals, what actually helps it fade, and which changes mean you should call your doctor.
Your scar depends on how the surgery is done
A hysterectomy can be done through a cut in the abdomen (open or abdominal hysterectomy), through small keyhole cuts (laparoscopic or robot-assisted hysterectomy), or entirely through the vagina (vaginal hysterectomy and vNOTES). Your surgeon chooses the route based on the size of the uterus, the reason for surgery, previous operations and your general health. For example, an open operation may be recommended when the uterus is enlarged by fibroids and can’t be removed through the vagina.
Whether the cervix is removed or kept doesn’t change the scar. A partial (supracervical) hysterectomy and a total hysterectomy can both be done through any of these routes, so two women with the same type of hysterectomy can have very different scars.
Abdominal (open) hysterectomy scars
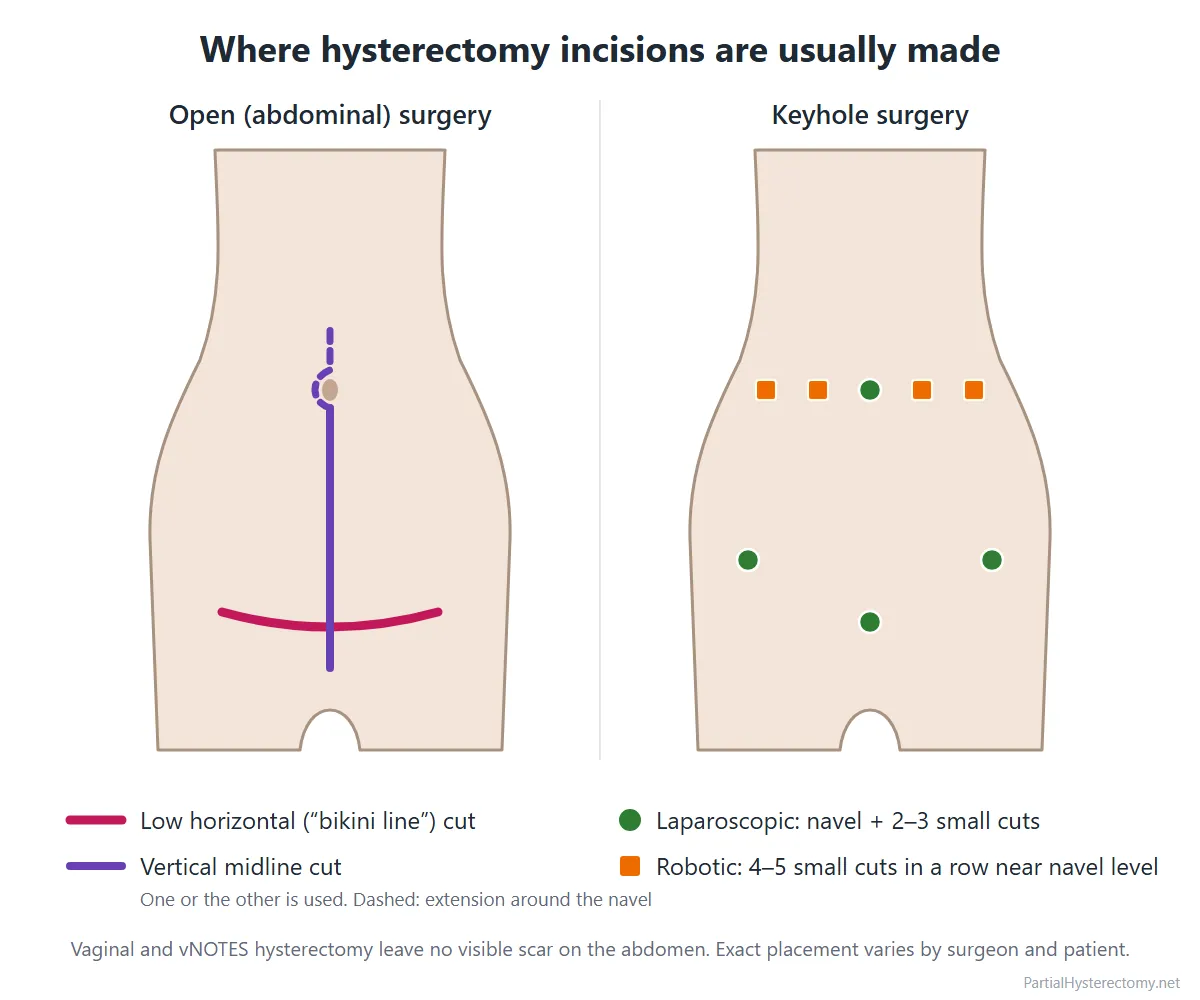
In an abdominal hysterectomy, the uterus is removed through a single cut in the lower abdomen. The cut is usually horizontal along the bikini line, but sometimes it has to be vertical. Open surgery leaves the largest scar of all the approaches, and recovery takes longer than after keyhole or vaginal surgery.
Low horizontal (“bikini line”) scar
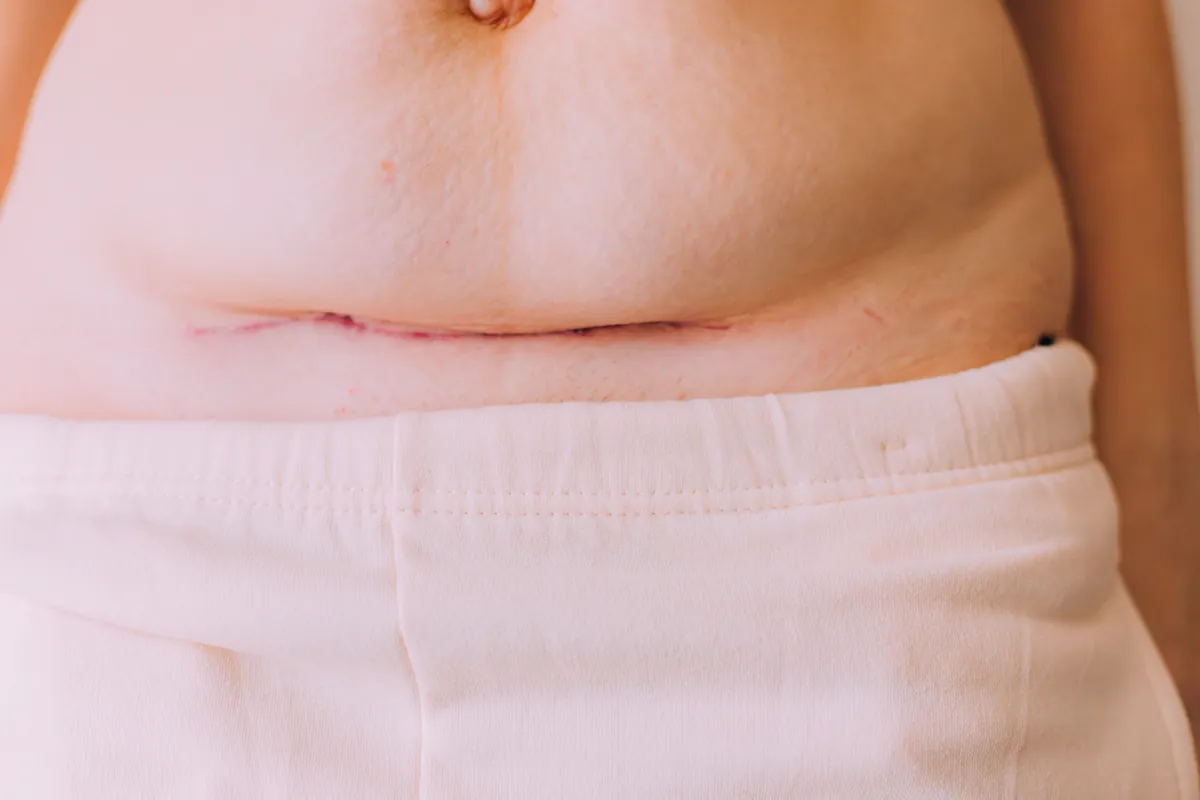
This is the most common incision for an open hysterectomy. It runs side to side just above the pubic hairline, often in a slight smile shape, and is usually hidden by underwear or a bikini bottom once healed. If you have had a caesarean section, your surgeon will often use the same line, so you may not end up with a second scar.
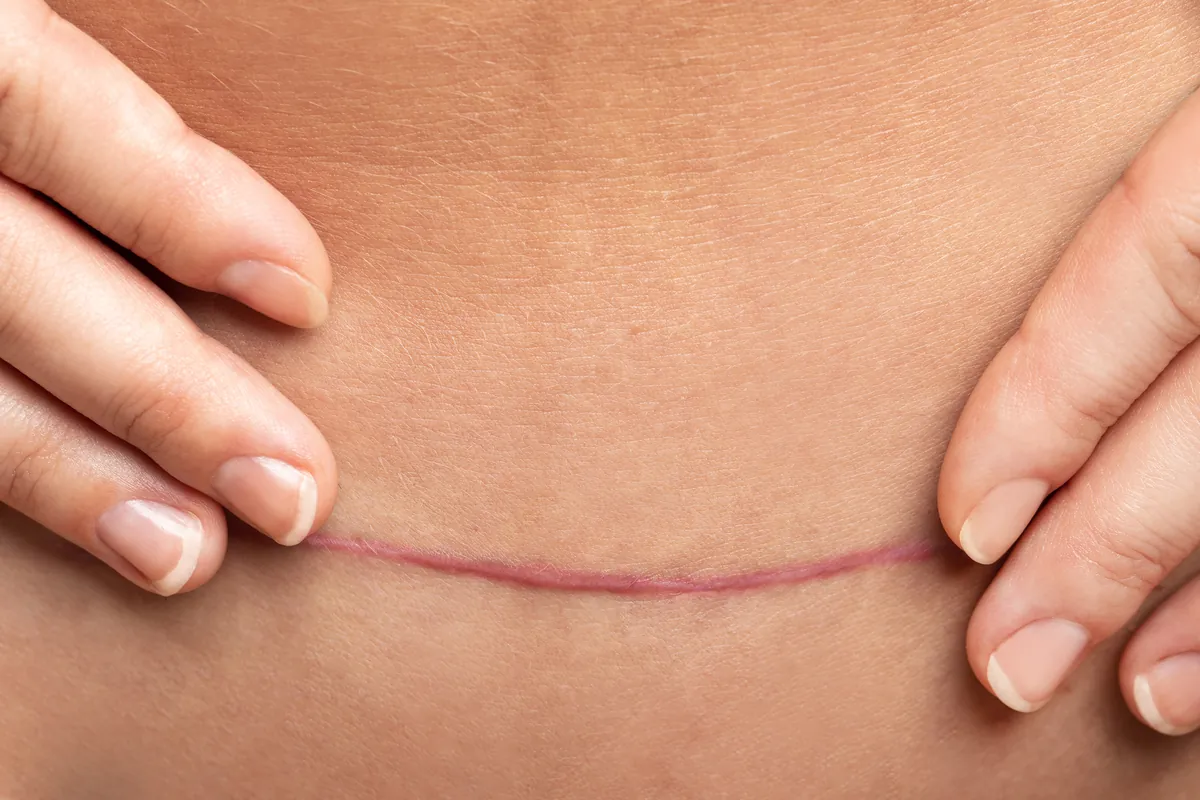
In the first months a horizontal scar is usually pink or red and slightly raised, and the skin just above it can look puffy. Both settle gradually.
Vertical midline scar
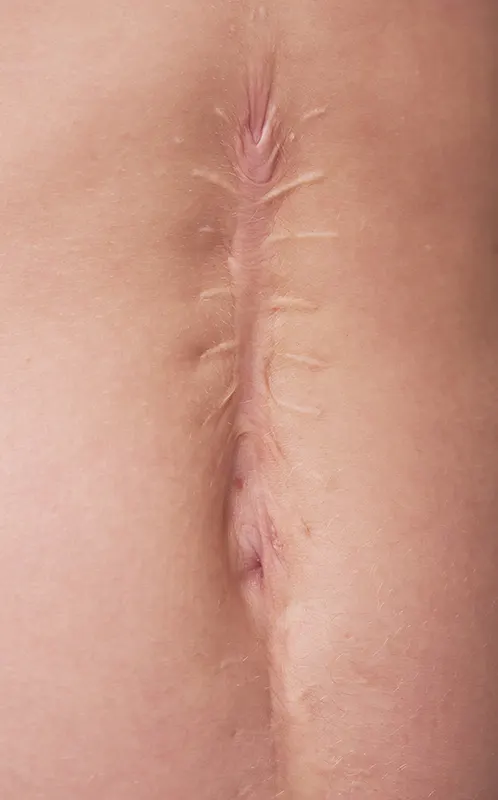
A vertical cut runs down the middle of the lower abdomen, from below the navel toward the pubic bone. Surgeons use it when they need more room: for a very large uterus or large fibroids, a big ovarian cyst, some cancer operations, or an emergency. If even more space is needed, the cut can be extended upward, curving around the navel.
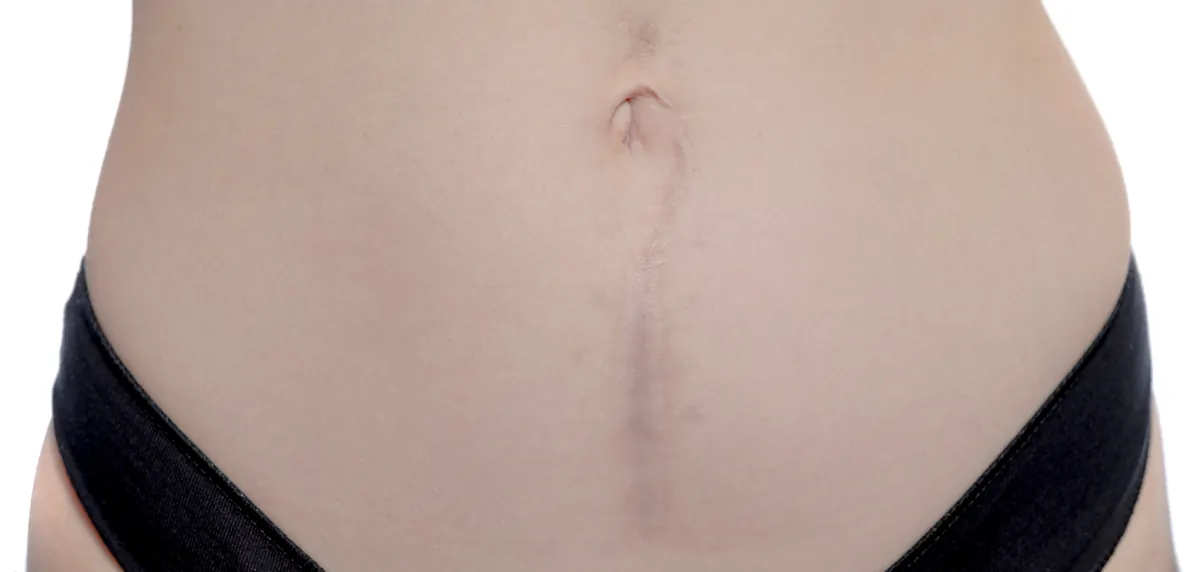
Vertical scars are more visible than bikini-line scars, and the incision itself carries a higher risk of an incisional hernia later on (see when to call your doctor). Some closures, such as staples or stitches tied over the skin, can leave small dots on either side of the scar line.
Laparoscopic (keyhole) hysterectomy scars
In a laparoscopic hysterectomy, the surgeon inserts a thin camera through a small cut, usually in or just below the navel, and works through two or three more small cuts lower on the abdomen. The uterus is then removed through the vagina or, in a laparoscopic supracervical hysterectomy, sometimes through one of the abdominal openings. In a laparoscopically assisted vaginal hysterectomy (LAVH), part of the operation is done through these small cuts and part through the vagina.
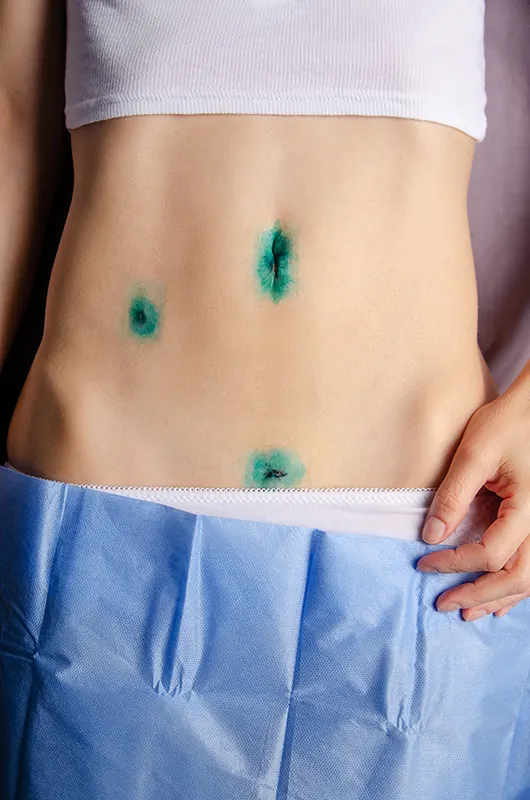
The result is several small scars instead of one long one. The navel scar often hides inside the belly button fold, and the others usually fade to small pale marks. Bruising around the cuts in the first week or two is common.
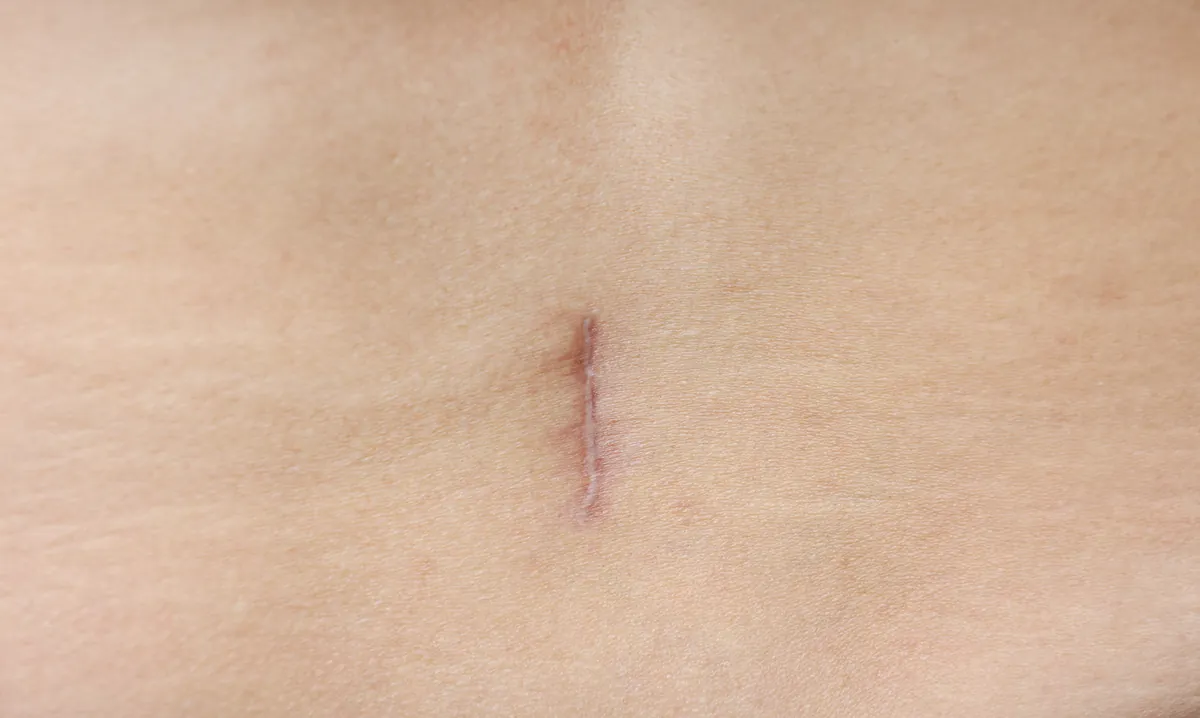
Robotic hysterectomy scars
A robot-assisted hysterectomy is a type of keyhole surgery in which the surgeon controls the instruments from a console. The scars look much like laparoscopic scars, but there are often four or five of them, and they are frequently placed in a row across the abdomen at about the level of the navel rather than low on the belly. Like other keyhole cuts, they usually fade to small marks.
Vaginal and vNOTES hysterectomy: no visible scar
In a vaginal hysterectomy, the uterus and cervix are removed through a cut at the top of the vagina, which is then closed with dissolving stitches. A vNOTES hysterectomy uses keyhole instruments passed through the vagina. Neither leaves a scar on the abdomen. The internal wound still needs time to heal, which is why the usual advice about avoiding sex and heavy lifting for several weeks still applies.
How a hysterectomy scar changes over time
The first two weeks
Your wound may be closed with dissolving stitches, removable stitches, staples, clips, skin glue or adhesive strips. Glue and dissolving stitches don’t need removing. Removable stitches and staples are typically taken out by a nurse about nine to ten days after surgery; your hospital will tell you which type you have.
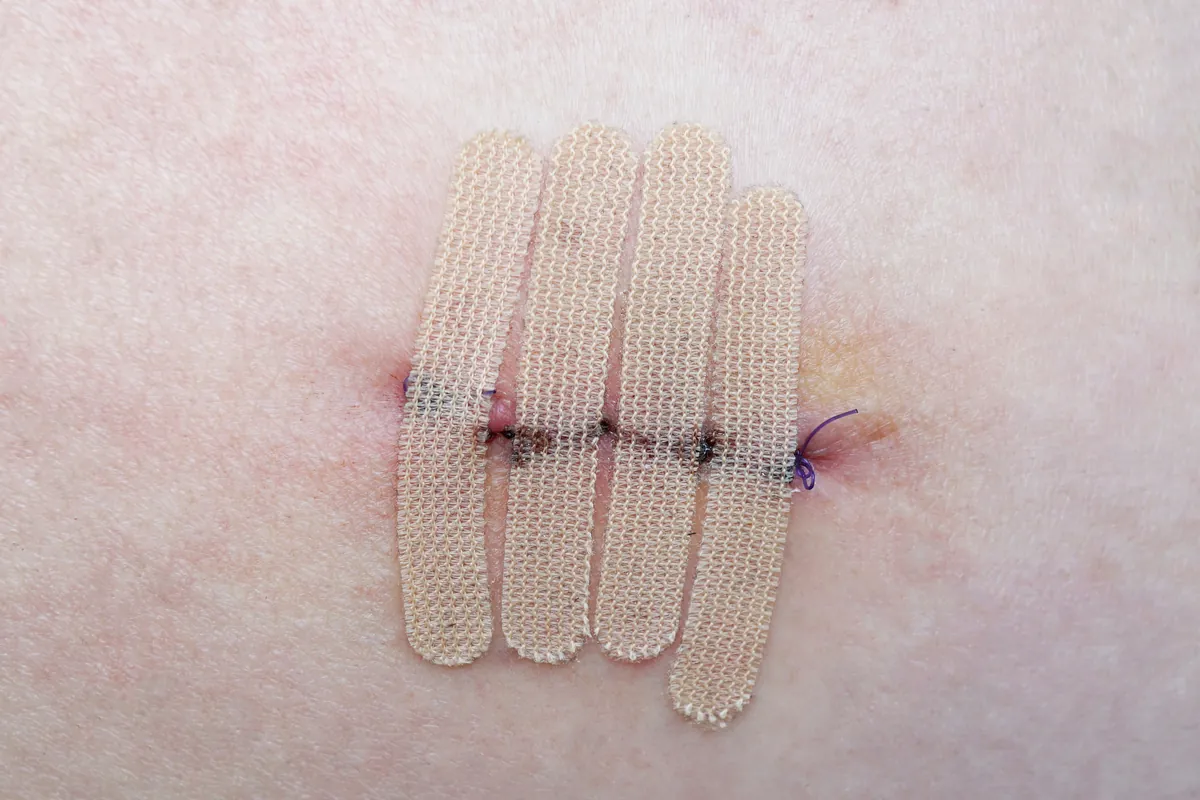
Unless you were told otherwise, you can usually remove the dressing and shower about 24 hours after surgery. Letting water run over the scar is fine; pat it dry with a clean towel or tissue, or let it air dry. Avoid soaking in a bath, pool or hot tub until the wound has fully closed, usually after about two weeks. For a broader picture of the first weeks, see our week-by-week recovery guide.
The first months
Once the wound has closed, the scar is usually pink, red or purplish and may be slightly raised, firm and itchy. This is the body laying down new collagen, and it is normal. A raised scar that thickens over the first few months may be a hypertrophic scar (see below), which usually improves with time.
Up to two years
Scars keep maturing for a long time. According to the NHS, most scars fade and flatten over a period of up to two years, and they are unlikely to change much after that. A scar never disappears completely. On lighter skin it usually ends up as a thin pale line; on darker skin it may settle as a brown or lighter mark.
Numbness, itching and the fold above the scar
Numbness and tingling. Small skin nerves are cut during surgery, so numbness, tingling or extra sensitivity around the scar is common, especially after open surgery. It usually improves over weeks to months as the nerves recover. A small numb patch can last much longer and is not a sign that anything is wrong.
Itching. An itchy scar is part of normal healing. Keeping the skin moisturized once the wound has closed often helps. Avoid scratching an unhealed wound.
A fold or “shelf” above a horizontal scar. Some women notice that the skin and tissue just above a bikini-line scar sit over it, forming a small overhang. Early on, much of this is swelling, which settles over several months. A fold that remains is a cosmetic issue rather than a medical one and depends partly on body shape. If it bothers you after the scar has matured, a plastic surgeon can talk you through the options.
What actually helps a scar heal and fade
No product can erase a scar, but a few simple steps have reasonable support, and a few popular ones don’t.
- Follow your wound care instructions. A wound that heals without infection or reopening is the single biggest factor in how the scar looks.
- Protect it from the sun. Once the wound has healed, the American Academy of Dermatology recommends a broad-spectrum sunscreen of SPF 30 or higher, which may reduce red or brown discoloration. A scar below the bikini line is usually covered anyway, but remember it on the beach or by the pool.
- Massage, but only after it has fully healed. The NHS suggests massaging a healed scar with a simple water-based moisturizing cream a few times a day for up to ten minutes. This can help soften it and keep the skin supple.
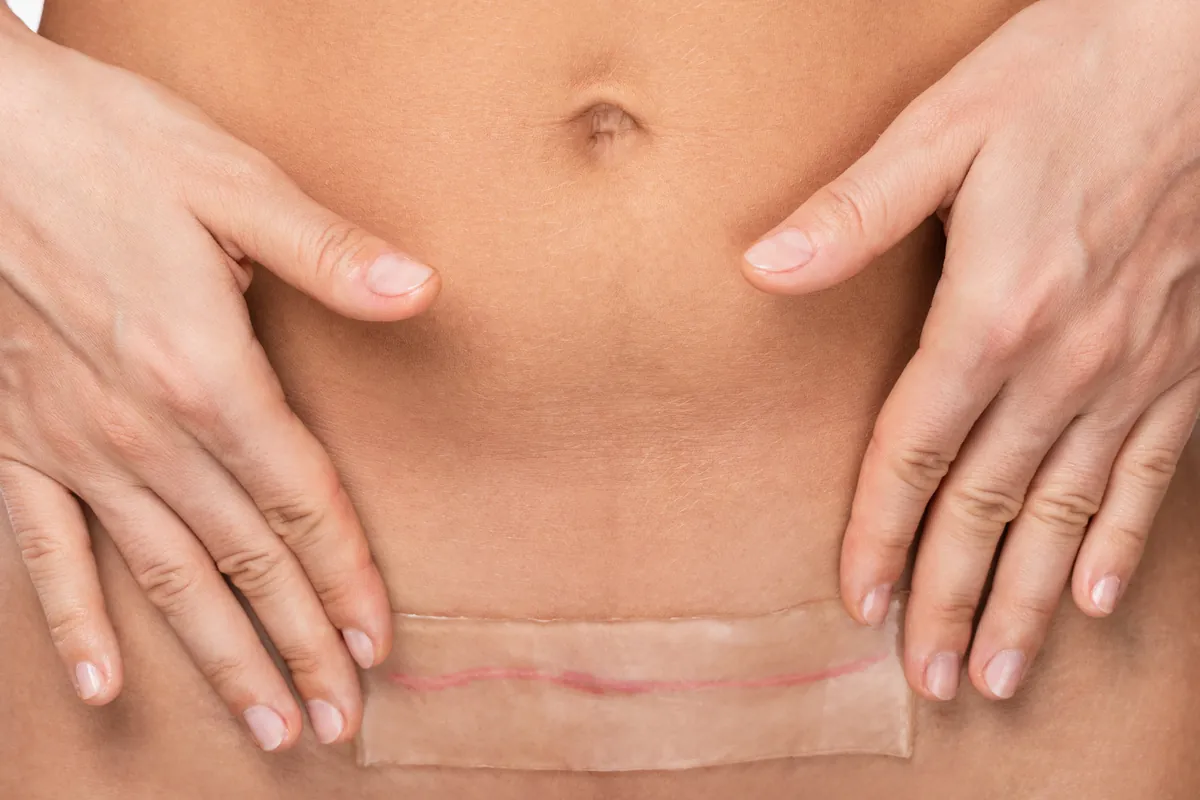
- Consider silicone gel or silicone sheets. These are the scar products with the most research behind them. A Cochrane review found weak evidence that silicone gel sheeting reduces raised scarring in people prone to it, although the studies were of poor quality. They are most worth trying if you have had raised or keloid scars before. Start only once the wound has closed.
- Don’t smoke. Smoking slows wound healing and raises the risk of infection.
What about vitamin E oil? It is widely recommended online, but the evidence doesn’t support it. In a small double-blind study of surgical scars, vitamin E either made no difference or made the scar look worse in 90% of cases, and a third of the patients developed an itchy skin rash (contact dermatitis) from it. The researchers concluded that it should not be used on surgical wounds.
Raised scars: hypertrophic scars and keloids
Sometimes the body produces too much collagen as a wound heals. A hypertrophic scar is red and raised but stays within the line of the original cut. It can keep thickening for up to six months and then usually flattens and pales over the following years. A keloid grows beyond the edges of the original wound, is usually firm and smooth, and does not normally flatten on its own. Keloids are more common in people with darker skin and tend to run in families.
If you have had keloids before, tell your surgeon before the operation. Raised scars can be treated by a dermatologist or plastic surgeon with steroid injections, steroid tape, silicone products, freezing (cryotherapy) or, in some cases, laser treatment or surgery. Treatment usually improves a keloid but rarely removes it completely.
When to call your doctor
Wound problems are not common, but they are easier to treat when caught early. Contact your surgical team, your doctor or an urgent care service if you notice:
- Redness that spreads, or skin around the wound that becomes hot, swollen or more painful instead of less.
- Pus, cloudy fluid or a bad-smelling discharge from the wound.
- A fever of 38°C (100.4°F) or higher, or feeling generally unwell.
- The wound edges coming apart, or a sudden gush of clear or blood-stained fluid from the scar.
- Abdominal pain that is getting worse rather than better.
- A bulge or lump in or near the scar, especially one that appears when you cough, strain or stand up. This can be an incisional hernia, which can appear months or years after surgery.
Incisional hernias are much more likely after a vertical midline cut than after a bikini-line cut. A large Swedish registry study of women who had open gynecological surgery found that a midline incision and obesity were the two strongest risk factors. If you are worried about this before surgery, our article on obesity and hysterectomy covers what you can discuss with your surgeon.
Frequently asked questions
Does a partial hysterectomy leave a smaller scar than a total hysterectomy?
No. The scar depends on the surgical route (open, keyhole or vaginal), not on whether the cervix is kept. You can read more about the difference between the two operations in partial vs total hysterectomy.
Can I choose which type of scar I get?
You can ask. If keyhole or vaginal surgery is safe and suitable for you, it means smaller or no visible scars and a quicker recovery. But the route depends on medical factors such as the size of the uterus, the reason for surgery and scar tissue from previous operations, so the final decision is made with your surgeon. If you have an existing caesarean scar, ask whether an open operation could go through it.
Is it normal for my scar to hurt months later?
Occasional twinges, pulling or sensitivity around a healing scar are common for several months, especially after open surgery. Pain that is getting worse, a new lump, or pain together with redness or fever should be checked. If the pain is mainly in your back, see back pain after hysterectomy.
Can a hysterectomy scar be removed?
No treatment removes a scar completely. Most scars fade a great deal without any treatment. For a scar that is raised, tight or bothering you once it has matured, a dermatologist or plastic surgeon can offer treatments that make it less noticeable, and special camouflage make-up can cover it.
Sources
- NHS. Hysterectomy: How it’s performed.
- Leeds Teaching Hospitals NHS Trust. Having a hysterectomy (patient information, including vNOTES).
- University Hospital Southampton NHS Foundation Trust. Recovering well after an abdominal hysterectomy. Patient factsheet adapted from the Royal College of Obstetricians and Gynaecologists, 2024.
- University Hospitals Coventry and Warwickshire NHS Trust. Abdominal hysterectomy (patient information leaflet).
- NHS. Scars.
- American Academy of Dermatology. Minimize a scar: Proper wound care tips from dermatologists.
- O’Brien L, Jones DJ. Silicone gel sheeting for preventing and treating hypertrophic and keloid scars. Cochrane Database of Systematic Reviews, 2013.
- Baumann LS, Spencer J. The effects of topical vitamin E on the cosmetic appearance of scars. Dermatologic Surgery, 1999.
- Archives of Gynecology and Obstetrics, 2019. Swedish national registry study of incisional hernia after open gynecological surgery (incidence and risk factors, including midline versus Pfannenstiel incisions).
This article is for general information and is not a substitute for medical advice. If you have concerns about your wound or scar, please talk to your surgical team or your own doctor.