Partial vs Total Hysterectomy: Key Differences, Evidence and How to Choose
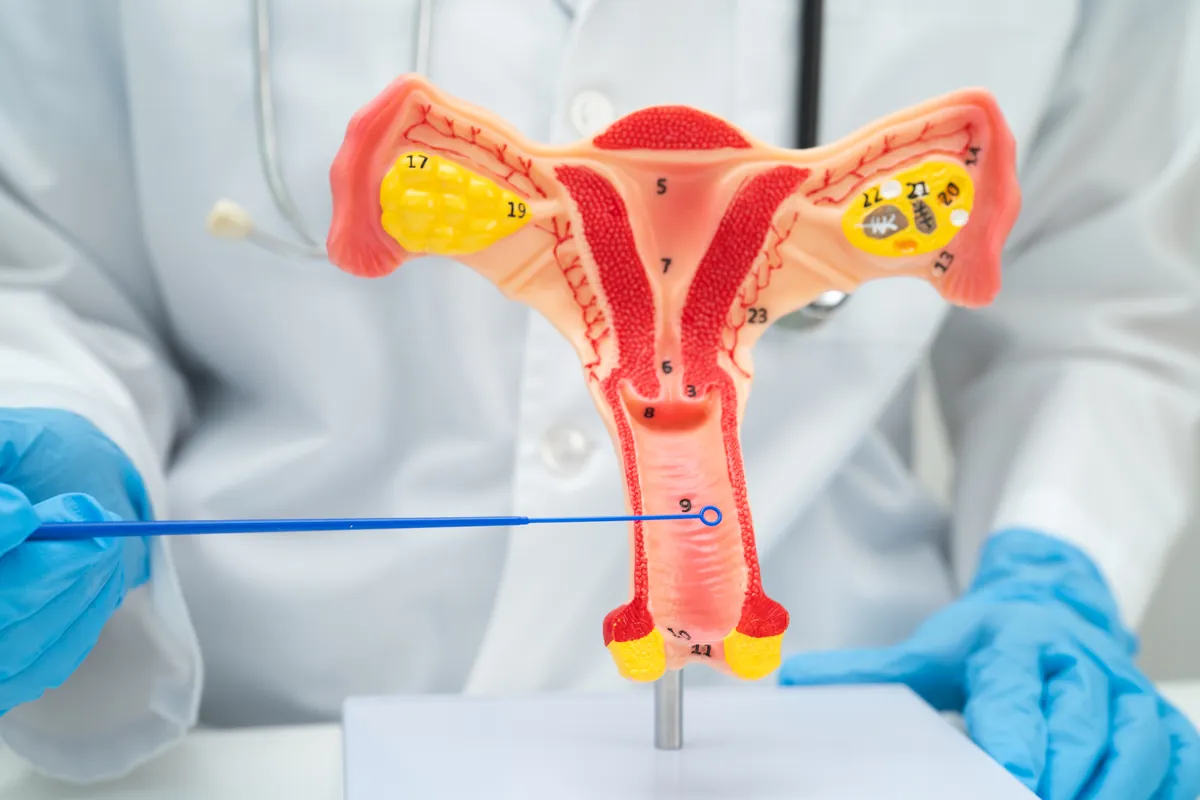
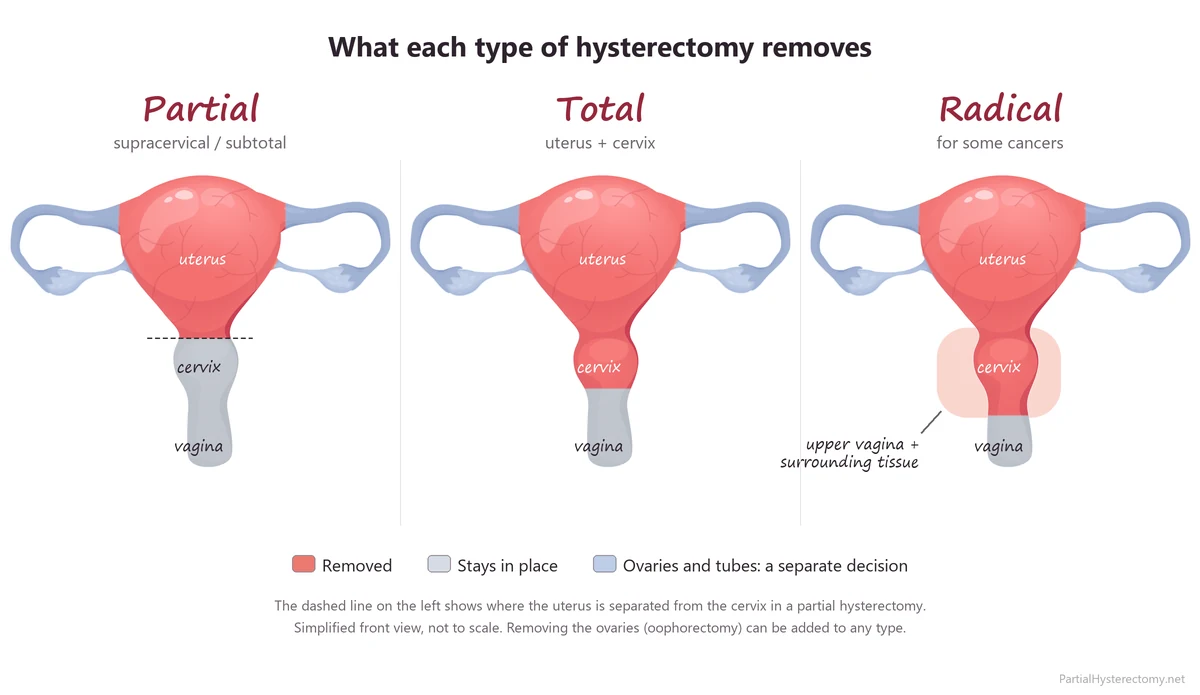
If your surgeon has offered you a choice between a partial and a total hysterectomy, the decision comes down to one organ: the cervix. A partial hysterectomy (also called supracervical or subtotal) removes the body of the uterus and leaves the cervix in place. A total hysterectomy removes the uterus and the cervix together.
Many women hear that keeping the cervix protects sex life, bladder control or pelvic support. The best randomized trials have not confirmed those benefits. What they do show is that keeping the cervix means you may still have some light monthly bleeding, and you will still need cervical screening. This guide explains the differences, what the research found, and the questions worth asking before you decide.
The short answer
- Partial (supracervical): uterus removed, cervix kept. Usually a slightly shorter operation. You keep needing cervical screening, and some women have light cyclical bleeding afterwards.
- Total: uterus and cervix removed. No more periods or spotting from the cervix, and cervical screening usually stops if the surgery was not for cancer or precancer.
- For sex, bladder and bowel function, recovery and overall complications, a Cochrane review of nine randomized trials found no clear difference between the two.1
- The ovaries are a separate decision. Either operation can be done with or without removing them.
What “partial” and “total” actually mean
The words are used loosely, which causes a lot of confusion. In medical terms:
- Partial, supracervical or subtotal hysterectomy all mean the same thing: the uterus is separated from the cervix and removed, and the cervix stays attached to the top of the vagina.
- Total hysterectomy means the uterus and cervix are removed. The top of the vagina is closed with stitches (this closed end is called the vaginal cuff).
- Radical hysterectomy is a bigger operation used for some cancers, mainly cervical cancer. It removes the uterus, cervix, the upper part of the vagina and the tissue around the cervix.
None of these terms tells you what happens to the ovaries. Many people say “partial hysterectomy” when they mean “my ovaries were left in”, but that is a different question. Removing the ovaries is called an oophorectomy, and it can be added to a partial or a total hysterectomy. If you are not sure what was removed in your own surgery, your operation notes or your surgeon’s office can tell you. For a full overview of the partial operation itself, see our guide Partial Hysterectomy: What It Is, How It’s Done and What Recovery Looks Like.
How each operation is done
The type of hysterectomy (partial or total) and the route (how the surgeon reaches the uterus) are two different choices, but they are linked.
- A total hysterectomy can be done through the vagina, by keyhole surgery (laparoscopic or robotic) or through an open cut in the abdomen.
- A partial hysterectomy is done by keyhole surgery or open surgery. It is not done through the vagina, because in a vaginal hysterectomy the surgeon reaches the uterus by working around the cervix, so the cervix comes out too.
The American College of Obstetricians and Gynecologists (ACOG) advises that, for non-cancerous conditions, a vaginal hysterectomy is the approach of choice whenever it is feasible, and that laparoscopic surgery is a better alternative to open surgery when it is not. ACOG notes that some patients choose a supracervical hysterectomy, and that in those cases a laparoscopic or open approach is the appropriate route.2 In practice, this means that if a vaginal hysterectomy would suit you, choosing to keep the cervix also means choosing a different route.
A note on morcellation
In a laparoscopic partial hysterectomy there is no opening at the top of the vagina, so the uterus has to be cut into smaller pieces to come out through a small incision. This is called morcellation. The US Food and Drug Administration (FDA) warns that if the uterus contains a cancer that was not suspected before surgery, cutting it up inside the abdomen can spread it. The FDA recommends that power morcellation is only used in carefully selected patients, always inside a containment bag, and not in women who are post-menopausal or over 50 with suspected fibroids.3 If you are offered a laparoscopic partial hysterectomy, it is reasonable to ask how the uterus will be removed and whether a bag will be used.
What the research shows
The strongest evidence comes from a Cochrane systematic review that combined nine randomized controlled trials with 1,553 women having hysterectomy for non-cancerous conditions.1 Compared with a total hysterectomy, a partial hysterectomy:
- made no clear difference to sexual, urinary or bowel function, either in the first two years or up to nine years later;
- made no clear difference to recovery, readmission, relief of the original symptoms or most complications;
- was about 11 minutes shorter and involved about 57 ml less blood loss, differences the authors considered unlikely to matter clinically;
- was linked to less fever and less urinary retention after surgery;
- was linked to a much higher chance of ongoing cyclical vaginal bleeding.
The review’s authors concluded that their results did not confirm the common belief that subtotal hysterectomy gives better sexual, urinary or bowel outcomes.
A Danish randomized trial followed women for an average of 14 years after open abdominal hysterectomy.4 It found no difference between the groups in pelvic organ prolapse, vaginal bleeding or discharge, sexual function or quality of life. Urinary incontinence was reported more often after the partial operation (33% versus 20%), but the difference was no longer significant once missing questionnaires were accounted for, and the authors asked for it to be interpreted with caution. Either way, the trial gave no support to the idea that keeping the cervix protects the bladder. The authors’ conclusion was that subtotal hysterectomy was not superior to total hysterectomy on any outcome.
You may still find hospital leaflets and websites that list better bladder or sexual outcomes as advantages of keeping the cervix. Those claims mostly come from older, non-randomized studies. The randomized trials, which are better at showing cause and effect, did not find them.
Downsides of keeping the cervix
Light monthly bleeding
A small amount of the uterine lining (endometrium) can remain at the top of the cervix. If your ovaries are still working, it can respond to your monthly hormones and cause light, period-like bleeding.5 In the Cochrane review this was far more likely after a partial than after a total hysterectomy.1 Individual studies report very different rates; one long-term study of women who had a laparoscopic partial hysterectomy found that about 1 in 10 had cyclical bleeding.6 For many women it is only spotting, but if the main reason for your surgery is to stop bleeding completely, this matters.
You still need cervical screening
Because the cervix is still there, it can still develop precancerous changes or cancer. The American Cancer Society says that if your cervix was left in place you still need screening, while after a total hysterectomy you generally do not, unless the surgery was done for cancer or a precancerous problem.7 UK screening services give the same advice: after a subtotal hysterectomy, keep attending routine screening.8 Read more in our guide to Pap smears after hysterectomy.
Possible later surgery on the cervix
Some women later need the remaining cervix removed (an operation called a trachelectomy), most often because of bleeding, discharge, pelvic pain or abnormal screening results.9 This second operation can be more difficult because of scar tissue from the first one, which can raise the risk of injury to the bladder, bowel or ureters.5 In one multicenter study of laparoscopic trachelectomy, 2 of 37 women had an injury to the bladder or bowel during the operation.9
Why some women still choose to keep the cervix
A partial hysterectomy remains a reasonable choice for some women with non-cancerous conditions such as fibroids or heavy bleeding, and ACOG acknowledges that some patients choose it.2 Common reasons include:
- a personal preference to keep as much of their body as possible;
- a slightly shorter operation with less handling of the tissue around the bladder;
- a surgeon’s judgement that removing the cervix would be technically difficult in their case, for example because of scar tissue from previous surgery.
If you are considering it, make sure you understand that the evidence does not show better sex or bladder function, and that you are comfortable with the possibility of light bleeding and ongoing screening.
When removing the cervix is usually advised
Keeping the cervix is generally not an option, or not a good one, when:
- the surgery is for cervical cancer, uterine cancer or a suspected cancer;
- you have had precancerous changes of the cervix, such as those treated with a LEEP procedure, or abnormal screening results that need follow-up;
- a vaginal hysterectomy is the best route for you, for example when the uterus has prolapsed;
- stopping all bleeding is your main goal;
- you would prefer not to continue cervical screening.
If you have endometriosis or adenomyosis, ask your surgeon specifically how they plan to handle the cervix, since tissue left behind can keep responding to hormones.
Sex after a partial or total hysterectomy
Concern about sex is one of the most common reasons women ask about keeping the cervix. In the randomized trials, sexual function was similar after both operations, both in the short term and years later.1,4 Many women find sex improves after hysterectomy because the pain or heavy bleeding that led to surgery has gone. After a total hysterectomy, the top of the vagina needs time to heal, so your surgical team will tell you when it is safe to have penetrative sex again; for keyhole surgery, NHS leaflets typically suggest around 4 to 6 weeks.8 For practical questions, see our guide to self-stimulation after hysterectomy.
Recovery
Recovery depends much more on the route (vaginal, keyhole or open) than on whether the cervix is kept. The Cochrane review found no clear difference in recovery time between partial and total hysterectomy.1 After keyhole surgery, many women return to most normal activities within about 4 to 6 weeks; open surgery usually takes longer. Our week-by-week recovery guide covers what to expect, and our pictures of hysterectomy scars show what each type of incision looks like.
When to get medical help
After either operation, contact your surgical team or doctor promptly if you have:8
- heavy vaginal bleeding, bleeding that starts again after it had settled, or a bad-smelling discharge;
- a fever, or abdominal pain that is getting worse rather than better, especially with vomiting or loss of appetite;
- burning when you pass urine or needing to go very often;
- red, hot or painful skin around a wound;
- a painful, swollen leg.
Call emergency services if you have chest pain, sudden breathlessness or cough up blood, as these can be signs of a blood clot in the lungs.
Questions to ask your surgeon
- Do you recommend removing or keeping my cervix, and why in my case?
- Which route will you use (vaginal, laparoscopic, robotic or open), and does keeping the cervix change that?
- If the uterus is removed by morcellation, will it be done inside a containment bag?
- What is the chance I will still have some monthly bleeding?
- Will my ovaries and fallopian tubes be removed or left in place?
- How often will I need cervical screening afterwards?
- What would happen if I needed the cervix removed later?
If your ovaries are being kept or removed, our article on hysterectomy and hormones explains how each option can affect you.
Sources
- Lethaby A, Mukhopadhyay A, Naik R. Total versus subtotal hysterectomy for benign gynaecological conditions. Cochrane Database of Systematic Reviews, 2012.
- American College of Obstetricians and Gynecologists. Committee Opinion No. 701: Choosing the Route of Hysterectomy for Benign Disease. Obstetrics & Gynecology, 2017.
- US Food and Drug Administration. UPDATE: Perform Only Contained Morcellation When Laparoscopic Power Morcellation Is Appropriate: FDA Safety Communication. 2020.
- Andersen LL, Ottesen B, Alling Møller LM, et al. Subtotal versus total abdominal hysterectomy: randomized clinical trial with 14-year questionnaire follow-up. American Journal of Obstetrics and Gynecology, 2015.
- East Sussex Healthcare NHS Trust. The Choice of Subtotal (leaving the Cervix) or Total (removal of Cervix) Hysterectomy. Patient leaflet.
- Levy BS. Review of the evidence on subtotal versus total hysterectomy (citing Okaro et al.). OBG Management, 2004.
- American Cancer Society. Cervical Cancer Screening Guidelines.
- University Hospitals Plymouth NHS Trust. Laparoscopic Subtotal Hysterectomy. Patient leaflet. See also Public Health Wales, I have had a hysterectomy, why am I still being invited for screening?
- Surgical outcomes of laparoscopic trachelectomy following supracervical hysterectomy: a multicenter study. Obstetrics & Gynecology Science, 2022.
This article is for general information and is not a substitute for medical advice. Talk to your doctor or surgeon about your own situation before making decisions about surgery.