Partial Hysterectomy: What It Is, How It’s Done and What Recovery Looks Like
A partial hysterectomy is surgery that removes the uterus but leaves the cervix in place. If your doctor has mentioned it, or you’ve just had one and are trying to understand what was done, this guide explains what the surgery involves, how it compares with other types of hysterectomy, what the research says about keeping the cervix, and what recovery usually looks like.
What is a partial hysterectomy?
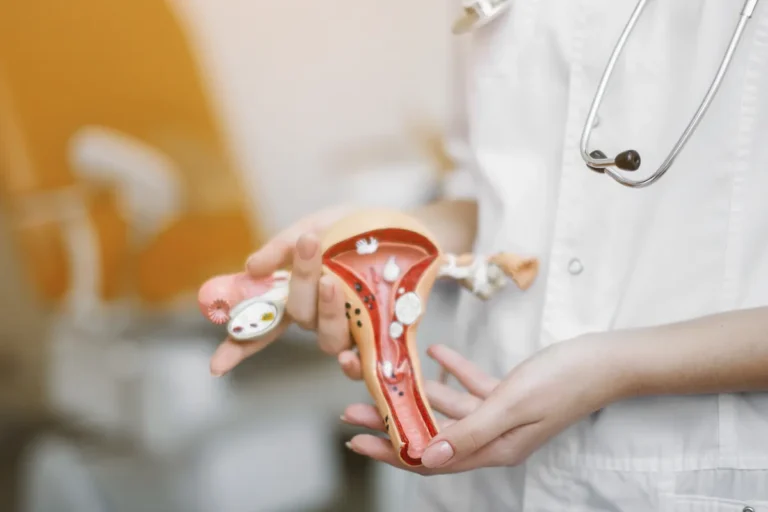
“Partial hysterectomy” is an everyday term, not a precise medical one. Doctors usually call this operation a supracervical or subtotal hysterectomy: the main body of the uterus is removed, and the cervix (the lower, narrow part of the uterus that opens into the vagina) stays where it is.
Because the terms are used loosely, many women aren’t sure afterwards exactly what was removed. It’s worth asking your surgeon for a clear answer, or checking your operative report, because it affects things like whether you still need cervical screening.
Partial, total and radical hysterectomy: what’s the difference?
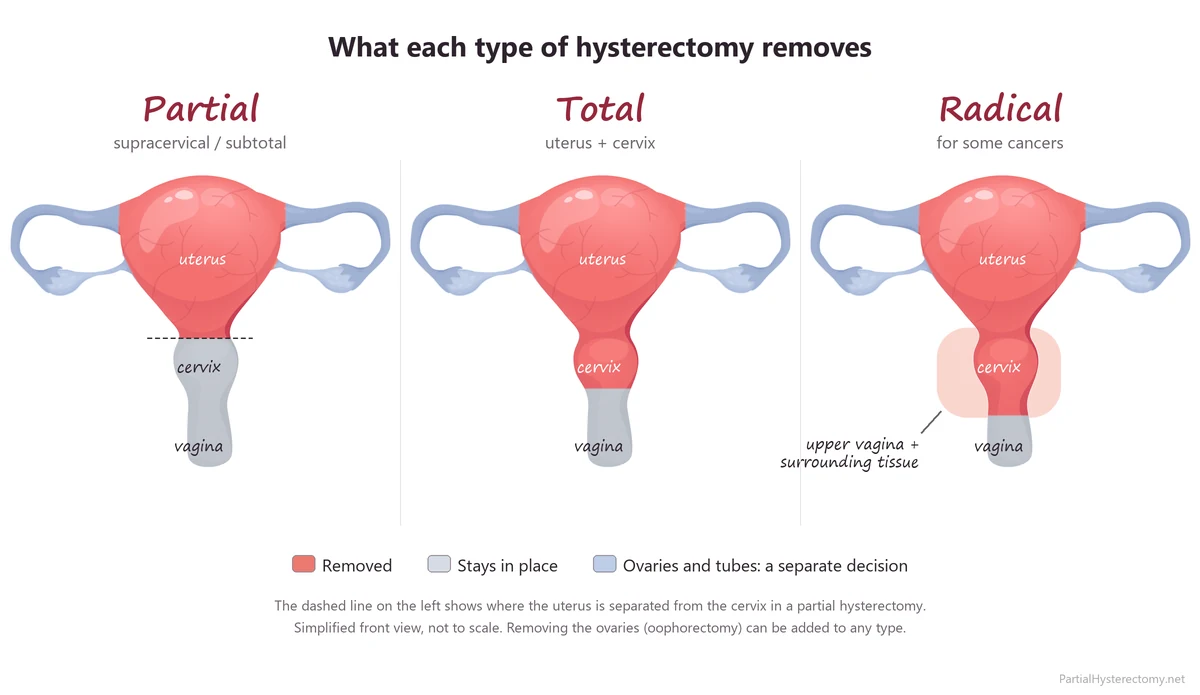
Total hysterectomy
The whole uterus is removed, including the cervix. This is the most common type of hysterectomy.
Partial (supracervical or subtotal) hysterectomy
The body of the uterus is removed and the cervix is kept.
Radical hysterectomy
The uterus, cervix, upper part of the vagina and some of the tissue around the cervix are removed. It’s mainly used to treat gynecologic cancers, such as cervical cancer, and recovery takes longer.
One common misunderstanding: none of these terms automatically includes the ovaries. Removing the ovaries (oophorectomy) and the fallopian tubes (salpingectomy) are separate decisions, even when they happen during the same operation. For a deeper comparison, see partial vs. total hysterectomy.
What happens to the ovaries and fallopian tubes?
If your ovaries are left in place, they keep producing hormones, so a partial hysterectomy on its own does not cause menopause. Your periods stop because the uterine lining is gone, but your hormonal cycle continues.
If both ovaries are removed before natural menopause, menopause begins right away (“surgical menopause”). The American College of Obstetricians and Gynecologists (ACOG) notes that removing both ovaries lowers ovarian cancer risk but may raise the risk of heart disease, osteoporosis, cognitive problems and overall mortality, which is why ovaries are often kept in women at average risk.
The fallopian tubes are a different story. Many ovarian cancers are now thought to start in the tubes, so ACOG recommends that surgeons discuss removing the tubes while keeping the ovaries (called opportunistic salpingectomy) with women having a hysterectomy for non-cancerous reasons. It doesn’t appear to affect how the ovaries work, and a large 2026 study reported a reduction of nearly 80% in ovarian cancer risk after the procedure. It lowers the risk, but doesn’t eliminate it entirely. If no one has raised this with you, it’s a good question to ask before surgery.
Why is a partial hysterectomy done?
A hysterectomy may be recommended for non-cancerous conditions such as uterine fibroids, heavy menstrual bleeding that hasn’t responded to other treatments, adenomyosis, endometriosis or chronic pelvic pain. Whether the cervix is kept depends on the condition, what the surgeon finds during the operation, and the patient’s preferences.
A partial hysterectomy is generally not an option when there is cancer or precancer of the cervix or uterus. According to MD Anderson Cancer Center, surgery for endometrial cancer calls for a total hysterectomy, and partial hysterectomy is rarely part of cancer treatment.
Hysterectomy isn’t the only option for many of these conditions. If you’re still deciding, read about alternatives for fibroids and the Mirena IUD vs. hysterectomy for heavy bleeding.
Does keeping the cervix make a difference?
For years, many women and doctors believed that keeping the cervix would protect sexual satisfaction, bladder control and bowel function. A Cochrane systematic review, which pooled randomized trials comparing the two operations for non-cancerous conditions, did not confirm that belief. Here’s what it found:
- Sexual, urinary and bowel function: no evidence of a difference between partial and total hysterectomy.
- The operation itself: partial hysterectomy was slightly shorter (about 11 minutes on average), with somewhat less blood loss and a lower chance of fever after surgery.
- Ongoing bleeding: women who kept their cervix were much more likely to have light, cyclical vaginal bleeding a year later. In the trials, this affected roughly 1 in 9 women after partial hysterectomy, compared with fewer than 1 in 100 after total hysterectomy. This happens because a small amount of uterine lining can remain near the cervix.
There’s one more important difference: if you keep your cervix, you can still develop cervical cancer. That means you need to continue regular cervical screening (Pap or HPV tests) on the usual schedule. After a total hysterectomy for a non-cancerous condition, routine screening is usually no longer needed. More on this in our guide to Pap smears after hysterectomy.
How is a partial hysterectomy performed?
Laparoscopic or robotic
The most common approach today. The surgeon works through a few small incisions in the abdomen using a camera and long instruments, sometimes with robotic assistance. Because the cervix stays in place, the uterus can’t be taken out through the vagina, so it’s usually cut into smaller pieces to remove it through the small incisions (a process called morcellation). Ask your surgeon how this will be done and whether a containment bag will be used.
Abdominal (open)
The uterus is removed through a larger incision in the lower abdomen. This may be needed for a very large uterus or complex cases, and it involves a longer hospital stay and recovery.
What about vaginal hysterectomy?
In a vaginal hysterectomy, the uterus is removed through the vagina, which means the cervix comes out with it. So a vaginal hysterectomy is a total hysterectomy, not a partial one. You can learn more in our guide to vaginal hysterectomy, and see what the scars look like for each approach in pictures of hysterectomy scars and incisions.
Recovery after a partial hysterectomy
Recovery depends mostly on how the surgery was done, more than on whether the cervix was kept.
- Hospital stay: after laparoscopic surgery, most women go home within a day or two, and some the same day. Abdominal surgery usually means a longer stay.
- Overall recovery: most women recover in about 3 to 4 weeks after laparoscopic surgery, and 4 to 6 weeks or more after abdominal surgery.
- Returning to work: UK clinical guidance suggests around 2 to 4 weeks for desk work, and 4 to 6 weeks (laparoscopic) or 6 to 8 weeks (abdominal) for physically demanding jobs.
- Sex and tampons: the usual advice is to avoid sex and putting anything in the vagina for about six weeks, or until your surgeon says it’s fine.
Light spotting or bleeding for a few weeks is normal and should gradually ease. For a detailed plan of what to do and avoid, see our week-by-week recovery guide and how to sit and protect your pelvic floor.
When to call your doctor
Contact your surgical team promptly if you have bleeding heavier than a period, foul-smelling discharge, a fever, pain that gets worse instead of better, redness or discharge from an incision, or trouble passing urine. Seek emergency care for chest pain, shortness of breath, or a painful, swollen leg, which can be signs of a blood clot.
Questions to ask your surgeon
- Do you recommend keeping or removing my cervix, and why in my case?
- Will my ovaries be kept? Should my fallopian tubes be removed?
- Which approach will you use: laparoscopic, robotic or abdominal?
- How will the uterus be removed, and will a containment bag be used?
- How long should I expect to be off work, and what should I avoid while I heal?
- Will I still need cervical screening afterwards?
Frequently asked questions
Will I still have periods after a partial hysterectomy?
Your regular periods stop. However, some women who keep their cervix notice light, monthly spotting, because a small amount of uterine lining can remain near the cervix. In the Cochrane review, this affected roughly 1 in 9 women a year after surgery.
Can I get pregnant after a partial hysterectomy?
No. Without a uterus, a pregnancy can’t develop, even if the ovaries and cervix remain.
Will a partial hysterectomy put me into menopause?
Not if your ovaries are kept. You may not be able to tell when menopause starts because you won’t have periods to track, so symptoms such as hot flashes become the main sign. Read more about menopause symptoms after hysterectomy with ovaries intact.
Do I still need Pap smears?
Yes. As long as you have a cervix, you should continue cervical screening on the normal schedule for your age.
Is a partial hysterectomy better for my sex life?
The best available evidence from randomized trials found no difference in sexual function between partial and total hysterectomy. If this matters to you, talk it through with your surgeon, and see our article on sexual pleasure after hysterectomy.
Sources
- Lethaby A, Mukhopadhyay A, Naik R. Total versus subtotal hysterectomy for benign gynaecological conditions. Cochrane Database of Systematic Reviews, 2012.
- Cochrane review findings summarized in: EurekAlert! news release on the Cochrane review of total vs. subtotal hysterectomy.
- American College of Obstetricians and Gynecologists. Committee Opinion No. 774: Opportunistic Salpingectomy as a Strategy for Epithelial Ovarian Cancer Prevention. Obstetrics & Gynecology, 2019.
- JAMA. Coverage of updated ACOG guidance on opportunistic salpingectomy, 2026.
- MD Anderson Cancer Center. What is a partial hysterectomy? Differences, benefits and risk factors.
- Public Health Wales. I have had a hysterectomy. Why am I still being invited for screening?
- UMass Memorial Health. Recovering from Hysterectomy: What You Should Know.
- Aneurin Bevan University Health Board (NHS Wales). Going Home after Laparoscopic Hysterectomy Surgery (patient leaflet).
- GPnotebook. Returning to work following hysterectomy.
This article is for general information and is not a substitute for medical advice. Every situation is different, so please talk to your own doctor about your options and recovery.