Prolapse After Hysterectomy: Why It Happens, Symptoms and Treatment
Pelvic organ prolapse means that one or more organs in the pelvis has dropped from its usual position and pushes into the vagina. It can happen after a hysterectomy, and many women only hear about it once they notice a bulge or a heavy, dragging feeling. The good news: serious prolapse after hysterectomy is not common, the early signs are easy to recognise, and there are effective treatments that don’t involve surgery.
This guide explains why prolapse can follow a hysterectomy, how likely it really is, what it feels like, and what you can do to lower your risk or treat it.
What pelvic organ prolapse is
The bladder, the uterus (if you still have it), the top of the vagina and the rectum are held in place by the pelvic floor muscles and by a network of ligaments and connective tissue. When that support weakens or stretches, an organ can sag downward and press against the vaginal walls. Doctors grade prolapse by how far it has descended, from mild (found only on examination) to a bulge that comes outside the vaginal opening.
Prolapse is very common in a mild form. Some degree of it is found on examination in roughly 41% to 50% of women, but only about 3% report symptoms from it [5]. In other words, a “prolapse” noted at a check-up is often small and harmless.
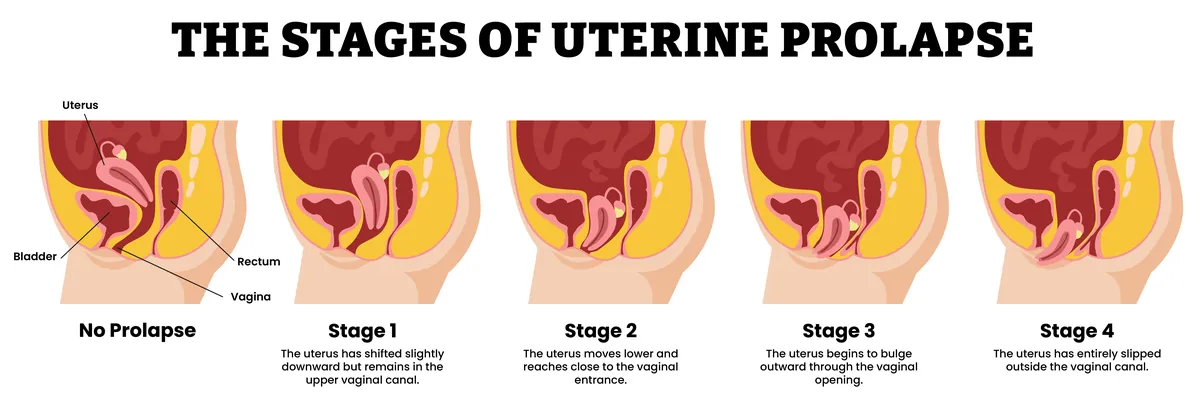
Why prolapse can happen after a hysterectomy
During a hysterectomy, the surgeon detaches the uterus from some of the ligaments that also help support the top of the vagina. In a total hysterectomy, the vagina is closed at the top, forming the vaginal cuff (or vault). If the cuff is not well anchored, or if the tissues were already weak, it can slowly sink over the years. The NHS lists pelvic surgery, including hysterectomy, among the causes of prolapse [1], and medical reviews list prior hysterectomy as a risk factor [5].
An important point that older articles often miss: the operation itself is only part of the story. In a Swiss study of more than 6,000 women who had a hysterectomy, the strongest predictor of later vault prolapse repair was having prolapse before the hysterectomy, which raised the odds about 6.6 times. Once that was taken into account, the type of hysterectomy (vaginal or abdominal) made no clear difference [4]. The authors concluded that later prolapse mostly reflects pelvic tissue weakness that was already present.
Keeping the cervix in a partial (supracervical) hysterectomy is sometimes suggested as a way to protect pelvic support, but the evidence has not shown a clear advantage. We cover that question in detail in Partial vs Total Hysterectomy.
How common is it?
Prolapse bad enough to need surgery after a hysterectomy is uncommon, though estimates vary between studies:
- In the long-running Oxford Family Planning Association study, about 1% of women needed prolapse surgery within 3 years of their hysterectomy, rising to about 5% at 15 years. Women whose hysterectomy had been done for prolapse were about 5.5 times more likely to need surgery again than women operated on for other reasons [3].
- The Swiss study found a much lower rate of vault prolapse repair: 0.36 per 1,000 women per year, or about 0.5% overall [4].
The differences come from how each study defined prolapse, how long women were followed and why they had a hysterectomy. The overall picture is reassuring: most women never develop prolapse that needs treatment, and the risk is concentrated in women who already had weak pelvic support.
Types of prolapse after hysterectomy
Prolapse is named by which part of the vagina bulges and what lies behind it. More than one type can happen at the same time.
Vaginal vault (apical) prolapse
The top of the vagina drops down toward the opening. This is the type most specific to women who have had the uterus removed. An enterocele, where a loop of small bowel pushes down behind the top of the vagina, often comes with it.
Bladder prolapse (cystocele)
The bladder sags into the front wall of the vagina. It can cause a feeling of not emptying the bladder fully, needing to pee more often or leaking when you cough or sneeze [1].
Rectal prolapse into the vagina (rectocele)
The rectum bulges into the back wall of the vagina. It can make bowel movements harder to complete; some women find they need to press on the vaginal wall or the area around it to empty their bowel. This is different from rectal prolapse through the anus, which is a separate condition.
Symptoms to watch for
Many women with mild prolapse have no symptoms at all. When symptoms do appear, the NHS describes these as typical [1]:
- A feeling of heaviness, pressure or dragging in the lower tummy or vagina, often worse at the end of the day or after standing for a long time
- A bulge or lump you can feel or see in or coming out of the vagina
- Bladder problems: needing to pee often, a slow stream, feeling the bladder hasn’t emptied, or small leaks
- Bowel problems such as constipation or difficulty emptying
- Discomfort, pain or reduced sensation during sex
In the first weeks after surgery, some pelvic heaviness is normal as tissues heal. Our week-by-week recovery guide explains what is expected. A bulge you can feel at the vaginal opening is different and should always be checked.
When to get medical help
Book a routine appointment if you notice a lump in or near the vagina or any of the symptoms above [1]. Seek care promptly if:
- You cannot pass urine, or you can only pass very small amounts despite feeling full
- A bulge outside the vagina becomes very painful, bleeds, or can’t be pushed back in
- In the early weeks after surgery, you feel something give way at the top of the vagina, or have a sudden gush of fluid, heavy bleeding or a fever
Who is at higher risk
Prolapse usually results from several factors adding up over time. Known risk factors include [1] [5]:
- Prolapse before the hysterectomy, or a hysterectomy done to treat prolapse [3] [4]
- Vaginal births, especially assisted (forceps or vacuum) deliveries
- Older age and the drop in estrogen after menopause
- Higher body weight (see obesity and hysterectomy)
- Long-term constipation and straining, or a chronic cough
- Repeated heavy lifting, for example at work
- A family history of prolapse, or connective tissue conditions such as Ehlers-Danlos syndromes or joint hypermobility
If prolapse is one of the reasons you are having a hysterectomy, ask your surgeon how the top of the vagina will be supported during the operation and what your chance of recurrence is.
Can you lower your risk?
You can’t change your age or your birth history, but several things are within reach:
Before and during surgery
Surgeons often attach the top of the vagina to the uterosacral ligaments while doing the hysterectomy, using techniques such as a McCall culdoplasty or a uterosacral plication, specifically to reduce the chance of vault prolapse later [10]. It is reasonable to ask whether this will be done, especially if you already have some prolapse.
Pelvic floor muscle training
Pelvic floor exercises are the main self-help measure, both for preventing symptoms and for treating mild prolapse. Once your surgeon says it’s fine to start, learning to do them correctly matters more than doing many. A pelvic floor physiotherapist can check your technique and set a program. Our guide on sitting comfortably and pelvic floor exercises after hysterectomy covers how to get started.
Everyday habits
The NHS suggests keeping a healthy weight, eating more fibre and drinking enough water to avoid constipation, staying active with gentle exercise such as walking, not smoking (a long-term cough strains the pelvic floor) and avoiding heavy lifting and high-impact activity if you have prolapse [2]. There is no evidence for a fixed, lifelong weight limit after a hysterectomy. What helps more is lifting with good technique: breathe out as you lift, keep the load close to your body and avoid holding your breath and bearing down.
Treatment options
Treatment depends on how much the prolapse bothers you, not only on how it looks on examination. A small prolapse without symptoms often needs nothing more than monitoring and pelvic floor exercises.

Supervised pelvic floor training
In the POPPY trial, 447 women with prolapse were given either five one-to-one sessions with a physiotherapist over 16 weeks or a lifestyle leaflet. The women who had the training reported fewer prolapse symptoms at 6 and 12 months, and the authors concluded that pelvic floor training should be recommended for conservative management of prolapse [6]. A Cochrane review also found evidence that this training improves prolapse symptoms and severity, though long-term effects are less clear [7].
Vaginal estrogen
After menopause, low-dose estrogen applied in the vagina (cream, tablet or ring) can help the vaginal tissues and is often used alongside a pessary [2]. It does not lift a prolapse on its own.
Vaginal pessary
A pessary is a soft silicone device placed in the vagina to hold the organs up [2]. More than 85% of women who choose one are fitted successfully, and up to 77% are still using it after a year. Fitting can be harder after a hysterectomy, especially if the vagina is short, so it may take a few tries to find the right shape and size [5]. Pessaries need regular check-ups to prevent irritation.
Surgery
Surgery is an option when symptoms are bothersome and other treatments haven’t helped enough. For vault prolapse, the main approaches are:
- Sacrocolpopexy (also called sacral colpopexy): through the abdomen, usually by keyhole or robotic surgery, the top of the vagina is attached to the base of the spine with a strip of mesh. A 2023 Cochrane review found it leads to less awareness of prolapse, fewer recurrences and fewer repeat operations than vaginal procedures [8].
- Vaginal repairs using your own tissue, such as sacrospinous fixation or uterosacral ligament suspension: done through the vagina, with no abdominal cuts and usually a quicker recovery.
- Colpocleisis: closing the vagina. It is a smaller operation with a high success rate, offered to women who do not plan to have vaginal intercourse in the future.
About mesh: in 2019 the US FDA ordered manufacturers to stop selling mesh designed for prolapse repair through the vagina [9], and in the UK this type of surgery is no longer done on the NHS unless there is no alternative [2]. The Cochrane review also found that transvaginal mesh offered no clear benefit over native tissue repair [8]. Mesh placed through the abdomen in sacrocolpopexy is a different procedure and is still used, but it has its own risks, so ask your surgeon to explain them.
Living with prolapse
Prolapse is not dangerous in most cases, and it often stays stable for years. Many women manage well with exercises, a pessary or simple adjustments. It can affect sex and confidence, so it helps to talk openly with your partner and your doctor; our articles on sexuality after hysterectomy and long-term effects after hysterectomy may also help.
Key points
- Prolapse after a hysterectomy is possible but uncommon; most women never need treatment for it.
- The biggest risk factor is weak pelvic support before surgery, including prolapse that led to the hysterectomy.
- Heaviness, a dragging feeling or a bulge in the vagina are the typical signs and are worth checking.
- Supervised pelvic floor training and pessaries work well for many women; surgery is available when they are not enough.
Sources
- NHS. Pelvic organ prolapse. nhs.uk
- NHS. Pelvic organ prolapse: treatment. nhs.uk
- Mant J, Painter R, Vessey M. Epidemiology of genital prolapse: observations from the Oxford Family Planning Association Study. British Journal of Obstetrics and Gynaecology, 1997. PubMed
- Dällenbach P, Kaelin-Gambirasio I, Jacob S, Dubuisson JB, Boulvain M. Incidence rate and risk factors for vaginal vault prolapse repair after hysterectomy. International Urogynecology Journal, 2008. University of Geneva archive
- Iglesia CB, Smithling KR. Pelvic Organ Prolapse. American Family Physician, 2017. aafp.org
- Hagen S, et al. Individualised pelvic floor muscle training in women with pelvic organ prolapse (POPPY): a multicentre randomised controlled trial. The Lancet, 2014. PubMed
- Hagen S, Stark D. Conservative prevention and management of pelvic organ prolapse in women. Cochrane Database of Systematic Reviews. cochrane.org
- Surgery for women with apical vaginal prolapse. Cochrane Database of Systematic Reviews, 2023. cochrane.org
- U.S. Food and Drug Administration. Urogynecologic surgical mesh implants. fda.gov
- Vaginal McCall culdoplasty versus laparoscopic uterosacral plication to prophylactically address vaginal vault prolapse. Gynecological Surgery, 2017. SpringerOpen
This article is for general information and is not a substitute for medical advice. If you have symptoms or questions about prolapse, talk to your doctor, gynecologist or a pelvic floor physiotherapist.





