Vaginal Hysterectomy: Who It Suits, What Happens and How Recovery Goes
A vaginal hysterectomy removes the uterus through the vagina, with no cut on the belly. Major gynecology guidelines and the largest review of randomized trials agree that, when it is technically possible, it is the route to consider first for non-cancer conditions: recovery is faster than after open surgery, the hospital stay is shorter than after laparoscopy, and there are no abdominal scars.[1][2] Yet it is now one of the least used routes in the United States.[3] This guide explains who it suits, what happens during the operation, the risks, and what recovery usually looks like week by week.
The short answer
- What is removed: the uterus and the cervix. The ovaries are usually left in place, and removing them through the vagina is not always possible.[4]
- Scars: none on the abdomen. The only stitches are at the top of the vagina, and they dissolve on their own.[4]
- Operation and stay: about 1 to 2 hours in theater; many women go home the same day or after 1 to 2 nights.[4][6]
- Recovery: most women are back to their usual activities within about 4 to 6 weeks.[5]
- Not for everyone: a very large uterus, a narrow vagina, or a need to see or treat problems higher in the pelvis can make another route safer.[1]
What a vaginal hysterectomy is
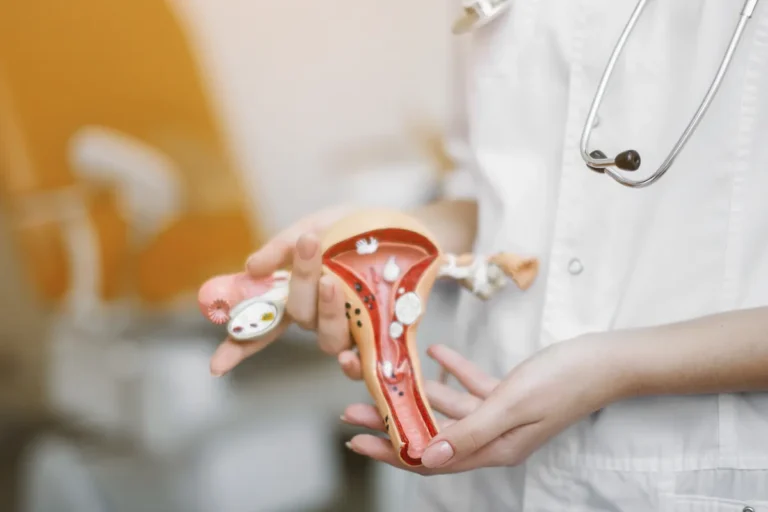
There are four main ways to reach the uterus: through an open cut on the belly (abdominal hysterectomy), through small keyhole cuts with a camera (laparoscopic hysterectomy, including robotic surgery), through the vagina, or with a mix of these. In a vaginal hysterectomy the surgeon works entirely from below: the uterus is freed from the ligaments and blood vessels that hold it in place and is then taken out through the vagina.[4]
Because the surgeon starts at the cervix, a vaginal hysterectomy is a total hysterectomy: the cervix is always removed with the uterus.[4] If you want to keep your cervix, that is a different operation, usually done by laparoscopy. Our guide to partial vs total hysterectomy explains the difference, and what a partial hysterectomy is covers the terms that often confuse patients.
Two related operations use the vaginal route with extra help from a camera:
- Laparoscopic-assisted vaginal hysterectomy (LAVH): part of the operation is done through keyhole cuts on the belly, then the uterus is finished off and removed through the vagina. It is useful when the ovaries need to come out or when the surgeon needs to look inside the abdomen.
- vNOTES: a newer technique in which the camera and instruments go in through the vagina itself, so there are still no belly cuts. Researchers say it needs more study before firm conclusions can be drawn.[2]
Why guidelines favor it
The American College of Obstetricians and Gynecologists (ACOG) states that the vaginal approach is preferred among the minimally invasive options for benign conditions, and that laparoscopy is the better alternative to open surgery when a vaginal hysterectomy is not suitable or feasible.[1]
The evidence behind this comes mainly from a Cochrane review updated in 2023, which pooled 63 randomized trials with 6,811 women.[2] Its main findings:
- Compared with open abdominal surgery, women returned to normal activities about 11 days sooner after a vaginal hysterectomy. If recovery after open surgery takes 42 days, after vaginal surgery it would be roughly 24 to 38 days. There were also fewer wound infections and shorter hospital stays.
- Compared with laparoscopic surgery, there was no clear difference in how quickly women got back to normal activities, but the vaginal operation was shorter and the hospital stay was shorter.
The authors concluded that, when technically feasible, vaginal hysterectomy should be performed in preference to abdominal hysterectomy. Much of the evidence was rated low or moderate quality, mostly because trials were small or poorly reported.[2]
Why fewer surgeons offer it
Despite this, vaginal hysterectomy has been falling out of use in the United States. In a 2025 study of more than 1.5 million hysterectomies for benign conditions, its share dropped from 22.6% in 2006 to 8.3% in 2020, and it is projected to fall below 8% by 2030.[3] It was done more often by surgeons and hospitals that treat many cases of prolapse and incontinence, and by surgeons who perform many hysterectomies. In practice, whether you are offered a vaginal hysterectomy can depend as much on your surgeon’s training as on your body.
It is reasonable to ask your surgeon directly: “Am I a candidate for a vaginal hysterectomy? If not, why not? How many do you perform?” If the answer depends on experience rather than your anatomy, a second opinion from a gynecologist or urogynecologist who does them regularly is an option.
Who it suits and who it may not
ACOG lists the factors that shape the choice of route: the size and shape of the vagina and uterus, how easy it is to reach the uterus, any disease outside the uterus, whether other procedures are needed at the same time, the surgeon’s training and experience, the hospital’s resources, whether the surgery is urgent or planned, and your own informed preference.[1]
Often a good fit
- Uterine prolapse. Vaginal hysterectomy is used much more often for prolapse than for other reasons,[3] and it is often combined with repairs of the vaginal walls. Read more about prolapse and hysterectomy.
- Heavy or abnormal bleeding with a normal-sized or moderately enlarged uterus, after other treatments have not helped.
- Small or moderate fibroids, and some precancerous changes of the cervix or uterine lining, depending on the case.
When another route may be safer
- A very large uterus, for example with big fibroids, that cannot be safely brought down through the vagina.
- A narrow vagina or a uterus that sits high and does not move down at all.
- A need to look inside the abdomen or treat something there: suspected endometriosis or dense scar tissue, an ovarian cyst, or a plan to remove the ovaries. The ovaries are not usually removed during a vaginal hysterectomy.[4]
- Known or suspected cancer, where a specialist cancer surgeon decides the route.
Your surgeon examines you to judge how well the uterus moves and how much room there is. If you are told a vaginal hysterectomy is not possible, it is fair to ask which of these reasons applies to you.
What happens on the day
Preparation is the same as for other hysterectomies; our list of things to do before your hysterectomy covers the practical side.
- Anesthesia. Either a general anesthetic, so you are asleep, or a spinal anesthetic, which numbs you from the waist down while you stay awake or lightly sedated.[4]
- Position. You lie on your back with your legs raised and supported, as for a pelvic exam.
- The operation. The surgeon makes a cut around the cervix at the top of the vagina, separates the bladder and bowel away from the uterus, seals and cuts the supporting ligaments and blood vessels, and removes the uterus and cervix through the vagina.[4]
- Closing. The top of the vagina is closed with dissolving stitches, forming what is called the vaginal cuff. A gauze pack may be placed in the vagina to reduce bleeding; it is normally removed within 24 hours.[4]
- Catheter. A thin tube drains urine from the bladder and is usually removed the next day, once you can walk to the bathroom.[4][5]
The operation usually takes about 1 to 2 hours.[4] Occasionally the surgeon cannot complete it safely from below and switches to keyhole or open surgery during the same anesthetic. Ask beforehand how likely that is in your case.[4]
Risks and complications
Serious complications are uncommon, but every hysterectomy carries some risk. The ones to know about are:[4][5]
- Bleeding. One UK hospital leaflet estimates that 1 to 2 in 100 women need a blood transfusion. A collection of blood at the top of the vagina (a vault hematoma) can cause pain, fever or smelly discharge.
- Infection of the urine, the vagina or the pelvis, usually treated with antibiotics. Compared with open surgery, there are fewer wound infections because there is no belly wound.[2]
- Injury to the bladder, ureters or bowel. Rare, but it may need repair and a longer stay.
- Blood clots in the legs or lungs. Walking early, leg exercises and, for some women, blood-thinning injections lower the risk.
- Changes in sex. Some women notice pain or reduced sensation, particularly when vaginal repairs are done at the same time. The same leaflet estimates perhaps 1 in 10, while noting it had no local data.[4]
Vaginal cuff opening
Rarely, the stitched top of the vagina opens again before it has fully healed (cuff dehiscence). This seems to be less common after a vaginal hysterectomy than after a total laparoscopic one. In a US study of hysterectomies done between 2006 and 2009, it happened after 0.11% of vaginal hysterectomies and 0.75% of total laparoscopic ones;[7] a Finnish study of more than 13,000 operations found 0.05% and 1.27%.[8] Sudden pelvic pain, a gush of watery fluid or bleeding, or a feeling that something is coming down, especially after sex or straining, needs urgent medical attention.
Recovery, week by week
Advice differs a little between hospitals, so follow what your own surgeon tells you. As a guide, based on the Royal College of Obstetricians and Gynaecologists (RCOG) and MedlinePlus:[5][6]
In the hospital
Some women go home the same day; others stay 1 to 3 nights.[5][6] Nurses check your blood pressure, pulse and bleeding, and you will be encouraged to get up and walk early. Expect some lower belly pain and cramping for at least the first few days, even without an abdominal cut, and take your pain relief regularly at first.
Weeks 1 and 2
- Bleeding: light bleeding or brown discharge, like a light period, is normal for 1 to 2 weeks and sometimes longer. Some women have a short gush of old blood around day 10. Use pads, not tampons.[5][6] Our guide to recovery week by week has more detail.
- Activity: walk every day, starting with short walks. Lift only light things, such as a 1-liter bottle of water.[5] MedlinePlus suggests nothing heavier than a gallon jug of milk for the first few weeks.[6]
- Bowels: drink plenty of water and eat fruit, vegetables and fiber to avoid constipation and straining.[6]
- Sitting: there is no belly wound, but the pelvis can feel sore for a while. A soft cushion and changing position often help.
Weeks 2 to 6
- Walking: many women can walk for 30 to 60 minutes after 2 to 3 weeks.[5]
- Driving: not for 24 hours after a general anesthetic, and usually not until you can do an emergency stop comfortably, often 2 to 4 weeks. Check with your insurer.[5]
- Work: some women return after 2 to 3 weeks; many after 4 to 6 weeks, depending on the job.[5]
- Heavier lifting and exercise: build up gradually. RCOG suggests avoiding heavy lifting, including children, until 3 to 4 weeks, swimming once bleeding has stopped, and contact or high-impact sports for at least 6 weeks.[5]
Sex and tampons
The vaginal cuff needs time to heal. RCOG advises usually allowing 4 to 6 weeks before sex,[5] while MedlinePlus says to wait at least 8 weeks, or about 12 weeks if vaginal repairs were also done, and to avoid tampons and douches for 8 to 12 weeks.[6] Ask your surgeon at your check-up which timing applies to you; it depends on how the cuff is healing. A lubricant helps if there is dryness or discomfort.
After the operation: what changes
- No more periods and no pregnancy. This is permanent.
- Menopause: if your ovaries are kept, they keep making hormones and you do not go into menopause straight away. If both ovaries are removed before menopause, you will have surgical menopause.
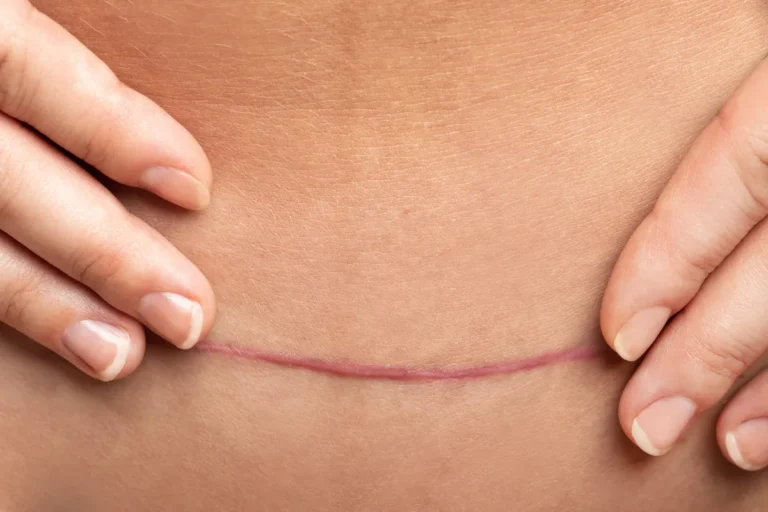
- No abdominal scars. If you are comparing routes, our page of hysterectomy scars and incisions shows what each type leaves.
When to call your doctor
Contact your surgeon or seek urgent care if you have:[5][6]
- A fever of 100.5°F (38°C) or higher.
- Vaginal bleeding heavier than a light period, or discharge with a bad smell.
- Belly pain that gets worse instead of better, or pain that your medicine does not control.
- Pain or burning when passing urine, needing to go very often, or being unable to pass urine.
- Nausea or vomiting, being unable to eat or drink, or being unable to pass gas or have a bowel movement.
- A painful, red, swollen or hot leg.
- A sudden gush of fluid from the vagina or a feeling that something is coming out.
Call 911 for shortness of breath, chest pain or coughing up blood, which can be signs of a blood clot in the lung.[5]
Sources
- American College of Obstetricians and Gynecologists. Committee Opinion No. 701: Choosing the route of hysterectomy for benign disease. Obstetrics & Gynecology. 2017;129(6):e155–e159. pubmed.ncbi.nlm.nih.gov
- Pickett CM, Seeratan DD, Mol BWJ, et al. Surgical approach to hysterectomy for benign gynaecological disease. Cochrane Database of Systematic Reviews. 2023;(8):CD003677. pubmed.ncbi.nlm.nih.gov
- Lerner V, Chen L, Xu X, et al. Current and future trends in performance of vaginal hysterectomy in the United States. Obstetrics & Gynecology. 2025;146(1):94–103. pubmed.ncbi.nlm.nih.gov
- Worcestershire Acute Hospitals NHS Trust. Vaginal hysterectomy +/- vaginal repair(s): patient information. worcsacute.nhs.uk
- Royal College of Obstetricians and Gynaecologists. Vaginal hysterectomy: recovering well. rcog.org.uk
- MedlinePlus (U.S. National Library of Medicine). Hysterectomy – vaginal – discharge. medlineplus.gov
- Hur HC, Donnellan N, Mansuria S, et al. Vaginal cuff dehiscence after different modes of hysterectomy. Obstetrics & Gynecology. 2011;118(4):794–801. pubmed.ncbi.nlm.nih.gov
- Ala-Nissilä S, Laurikainen E, Mäkinen J, et al. Vaginal cuff dehiscence is observed in a higher rate after total laparoscopic hysterectomy compared with other types of hysterectomy. Acta Obstetricia et Gynecologica Scandinavica. 2019;98(1):44–50. pubmed.ncbi.nlm.nih.gov
This article is for general information and is not a substitute for medical advice. Whether a vaginal hysterectomy suits you depends on your anatomy, your diagnosis and your surgeon’s experience, so always discuss your own situation with your gynecologist, and contact them or emergency services if you are worried about any symptom after surgery.