Robotic Hysterectomy: How It Works, Benefits, Risks and Recovery
A robotic hysterectomy is a keyhole operation to remove the uterus in which the surgeon controls the instruments from a console using a robotic system. It is often called a da Vinci hysterectomy, after the most widely used system. The name makes it sound futuristic, but the robot does not operate on its own: every movement comes from the surgeon’s hands.
This guide explains how a robotic hysterectomy is done, how it compares with laparoscopic, open and vaginal surgery, who is most likely to benefit, the risks to know about, what recovery looks like, and the questions worth asking your surgeon. If you are still deciding whether you need surgery at all, start with our overview of what a hysterectomy involves.
What is a robotic hysterectomy?
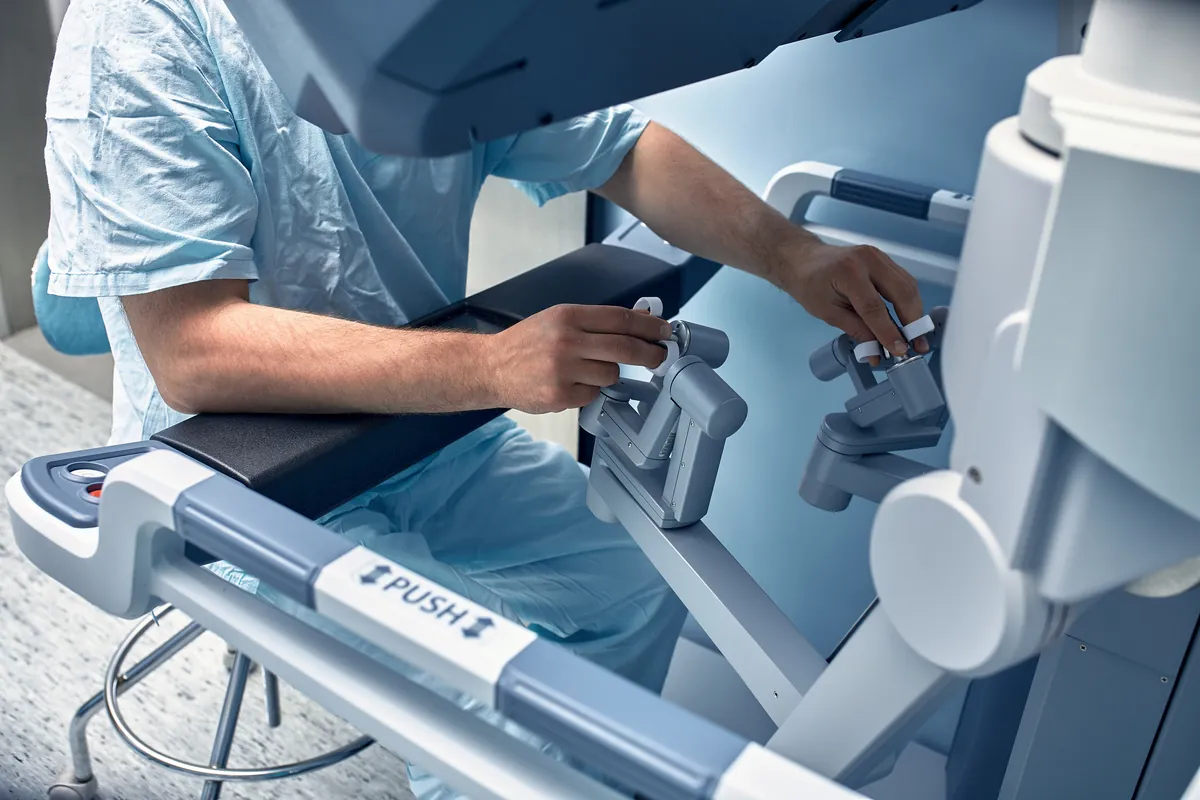
A robotic hysterectomy is a type of laparoscopic (keyhole) surgery. Instead of holding long instruments directly, as in standard laparoscopy, the surgeon sits at a console in the operating room and moves hand controls. The system translates those movements into smaller, steadier movements of instruments attached to robotic arms, which enter the abdomen through a few small incisions. A camera on one arm gives the surgeon a magnified, three-dimensional view of the pelvis.[1]
You may see it described as robotic-assisted laparoscopic hysterectomy, robot-assisted surgery or simply robotic surgery. The US Food and Drug Administration (FDA) is clear that these systems are controlled by the surgeon and cannot perform surgery by themselves.[2] The operation inside your body is the same as a standard keyhole hysterectomy; what changes is how the surgeon handles the instruments.[1]
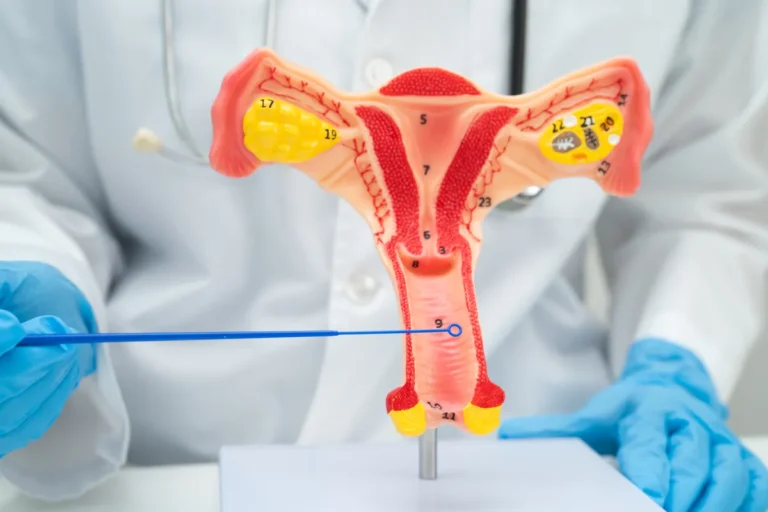
A robotic hysterectomy can be used for the same types of hysterectomy as other keyhole surgery: a total hysterectomy (uterus and cervix), a partial (supracervical) hysterectomy that keeps the cervix, or, in cancer care, more extensive operations. Whether the ovaries and fallopian tubes are removed is a separate decision you make with your surgeon.
How the operation is done
Details vary between hospitals, but a typical robotic hysterectomy follows these steps:[1]
- General anesthesia. You are fully asleep for the whole operation.
- Small incisions. The surgeon makes several small cuts in the abdomen, usually four or five, and fills the abdomen with gas to create space to work.
- Docking. The robotic arms are attached to the ports placed through those incisions. In one trial this took an average of about six minutes.[3]
- Surgery from the console. The surgeon sits at the console next to the operating table, while an assistant stays at your side to change instruments.
- Removing the uterus. In a total hysterectomy the uterus is usually removed through the vagina, and the top of the vagina (the vaginal cuff) is stitched closed. If the cervix is kept, or the uterus is too large to come out whole, it may need to be cut into smaller pieces first.
- Closing. The small skin incisions are closed with stitches or skin glue.
Cutting the uterus into pieces inside the body is called morcellation. The FDA recommends that when a powered morcellator is used, the tissue is kept inside a containment system, and that it is not used when cancer is suspected or known, because it can spread an unsuspected cancer such as uterine sarcoma.[4] If your uterus is large, ask your surgeon how they plan to remove it.
Robotic operations usually take longer than standard laparoscopic ones. In a Swiss randomized trial, the robotic operation took an average of 106 minutes compared with 75 minutes for conventional laparoscopy.[5] In a US trial, the total case time was on average 77 minutes longer with the robot.[3] Times shorten as surgical teams gain experience, and they vary a lot with the size of the uterus and previous surgery.
As with any keyhole surgery, there is a small chance that the surgeon has to switch to an open operation with a larger cut, for example because of bleeding, scar tissue or an injury that needs repair.[1] This is a safety decision, not a failure, and it is worth asking how often it happens to your surgeon.
Robotic vs laparoscopic, open and vaginal hysterectomy
There are four main routes for a hysterectomy. For non-cancerous conditions, the American College of Obstetricians and Gynecologists (ACOG) recommends vaginal hysterectomy whenever it is feasible, and laparoscopic surgery (with or without a robot) as the next choice when it is not. Open abdominal surgery is kept for cases where a minimally invasive route is not possible.[6] Our step-by-step guide to vaginal hysterectomy explains that route in detail.
| Route | How it is done | Main points |
|---|---|---|
| Vaginal | Uterus removed through the vagina, no abdominal cuts | Preferred route when feasible for non-cancerous conditions; no visible scars[6] |
| Laparoscopic | Several small abdominal cuts; surgeon holds the instruments | Faster recovery and shorter stay than open surgery[7] |
| Robotic | Several small abdominal cuts; surgeon controls robotic instruments from a console | Similar complication rates to laparoscopy, longer operation, higher cost[8][9] |
| Open (abdominal) | One larger cut, usually low across the abdomen | Used for very large uteri, some cancers or when keyhole surgery is not possible; longest recovery[7] |
What the evidence says about robotic vs laparoscopic surgery
Compared with open surgery, any minimally invasive approach (laparoscopic or robotic) has clear advantages: a faster return to normal activities, a shorter hospital stay and better quality of life.[1] The harder question is whether the robot adds anything over standard laparoscopy. So far, the answer for most women is: not much, except cost.
- Complications: a Cochrane review of randomized trials found little or no difference in complication rates between robotic and conventional laparoscopic hysterectomy, though the evidence was of low certainty.[8] A US study of more than 264,000 women with non-cancerous conditions found similar overall complication rates (5.5% robotic vs 5.3% laparoscopic).[9]
- Operating time: longer with the robot, by about 30 to 77 minutes on average in randomized trials.[3][5]
- Hospital stay: slightly shorter in some studies. In the US study, fewer women stayed more than two days after robotic surgery (19.6% vs 24.9%).[9] The Cochrane review found a difference of about a third of a day, based on very low-certainty evidence.[8]
- Pain and return to activity: no difference in two randomized trials.[3][5] One trial found a better quality-of-life score shortly after robotic surgery, but no long-term difference.[5]
- Cost: about $2,189 more per operation than laparoscopic hysterectomy in the US study.[9]
ACOG’s committee opinion on robotic surgery for non-cancerous conditions describes the quality of the evidence as “low to moderate” and says more research is needed to identify which patients benefit most.[1] In practice, a skilled surgeon using a familiar technique matters more than the technology itself.
Who may benefit most from a robotic hysterectomy?
The robot’s main practical advantage is that it can make keyhole surgery possible in women who might otherwise need open surgery. This matters because avoiding a large abdominal incision brings a real difference in recovery.
- Women with obesity. In a US database study of more than 533,000 benign hysterectomies, robotic surgery had become the most common approach for women with severe obesity by 2020 (40.8%). In that group, it was linked to less bleeding and fewer conversions to open surgery than standard laparoscopy.[10] Some of the authors worked for the company that makes the most widely used robot, so these results are best read alongside independent studies. See also our article on obesity and hysterectomy.
- Complex surgery. Some hospitals offer robotic surgery mainly for women with a large uterus from fibroids or adenomyosis, endometriosis or scar tissue from previous operations, where the extra dexterity may help.[11]
- Endometrial (womb) cancer. For early endometrial cancer, a large randomized trial found that keyhole surgery caused fewer moderate to severe complications than open surgery (14% vs 21%) and shorter hospital stays.[12] Robotic surgery is widely used for this operation.
When robotic surgery may not be the best choice
- When a vaginal hysterectomy is possible. ACOG recommends the vaginal route as the approach of choice for non-cancerous conditions whenever it is feasible. It needs no abdominal incisions.[6]
- Radical hysterectomy for early cervical cancer. In the LACC trial, women with early cervical cancer who had minimally invasive radical hysterectomy (laparoscopic or robotic) had lower survival than those who had open surgery. Disease-free survival at 4.5 years was 86.0% vs 96.5%, and overall survival at 3 years was 93.8% vs 99.0%.[13] Because of this trial, open surgery is now generally favored for this operation. Read more in our guide to radical hysterectomy for cervical cancer.
- Cancer surgery in general. The FDA notes that no robotic system has been specifically authorized to prevent or treat cancer, and that clearance for procedures like hysterectomy was based on 30-day outcomes, not long-term survival.[2] For cancer, the decision should come from a gynecologic oncologist.
- A very large uterus that cannot be removed safely through small incisions may still need open surgery.
Risks and complications
The risks of a robotic hysterectomy are largely those of any hysterectomy, because the operation itself is the same.[11] They include:
- Bleeding, sometimes needing a blood transfusion.
- Infection of the wounds, bladder or pelvis.
- Injury to the bladder, the ureters (the tubes from the kidneys) or the bowel. Most are found and repaired during surgery, but a small injury can show up days later.
- Blood clots in the legs or lungs.
- Conversion to open surgery.
- Problems with the vaginal cuff, such as a collection of blood behind the stitches or, rarely, the cuff opening up.[11]
- Longer-term changes, such as bladder symptoms or vaginal vault prolapse.[11] See our article on prolapse after hysterectomy.
Vaginal cuff opening (dehiscence) is uncommon but more frequent after keyhole hysterectomy than after vaginal or open surgery. In a 10-year study at a US academic hospital, it happened after 1.35% of total laparoscopic hysterectomies, compared with 0.24% across all routes.[14] This is one reason surgeons ask you to avoid sex and anything inside the vagina until the cuff has healed.
Risks linked to the robot itself
Like any machine, the robot can malfunction. An analysis of 14 years of reports to the FDA’s adverse-event database found that most reports were device malfunctions, such as broken or burnt pieces of instruments, electrical arcing, system errors or video problems. Some led to injuries, or to the operation being paused, restarted or converted to another technique. Gynecology had lower rates of injury and death per procedure than more complex specialties such as heart and chest surgery.[15] Because reporting is voluntary and not standardized, the true rate of complications is not known.[1]
Recovery after a robotic hysterectomy
Recovery after a robotic hysterectomy is similar to recovery after a standard laparoscopic one, and usually faster than after open surgery. NHS guidance says that after vaginal or keyhole surgery you may go home between 1 and 4 days later, compared with up to 5 days after abdominal surgery, which can take 6 to 8 weeks to fully recover from.[7] One UK hospital reports that most women go home after one to three nights.[11]
- Right after surgery: you may have a drip and a urinary catheter for about a day, feel sleepy or sick from the anesthetic, and feel bloated.[11]
- Shoulder pain: the gas used to inflate the abdomen often causes pain around the shoulders. It settles within a few days and moving around helps.[11] Bloating can last longer; see our article on swelly belly after hysterectomy.
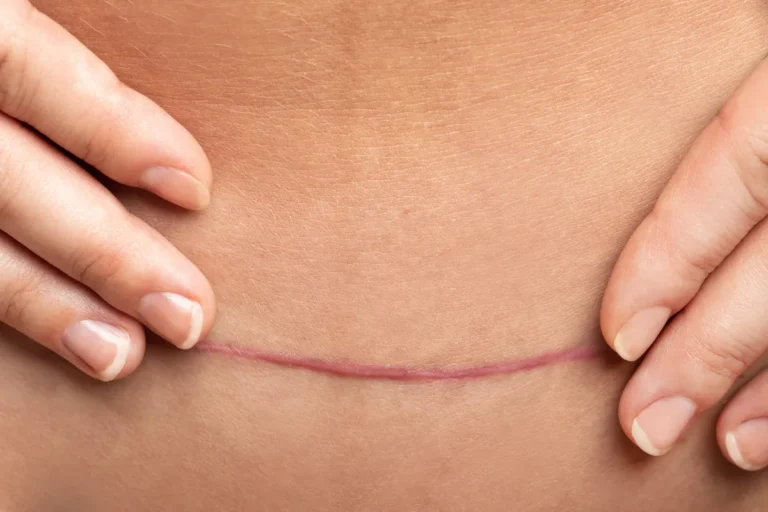
- Scars: several small scars on the abdomen, which usually fade over months. Our pictures of hysterectomy scars show what they look like.
- Driving: anything from 2 to 6 weeks, once you can wear a seatbelt comfortably and make an emergency stop.[7]
- Work: one UK hospital suggests planning six weeks off, less for some desk jobs and more for physical work.[11]
- Sex: wait until the scars have healed and any discharge has stopped, usually at least 4 to 6 weeks, and follow your surgeon’s advice about the vaginal cuff.[7]
Feeling well soon after keyhole surgery can be misleading: the inside, including the vaginal cuff, takes longer to heal than the small skin cuts. Our hysterectomy recovery week by week guide explains what to expect at each stage.
When to get urgent help
Contact your surgical team or go to the emergency department if you have any of these after going home:[11]
- A high fever.
- Abdominal pain or swelling that is getting worse rather than better.
- Being unable to pass urine, or passing very little.
- Swelling, redness or tenderness in one leg.
- Difficulty breathing or chest pain.
- Heavy bleeding from the vagina or a wound.
How much does a robotic hysterectomy cost?
Robotic surgery costs more than standard laparoscopy, mainly because of the equipment and the longer operating time. In the large US study, the extra cost was about $2,189 per operation.[9] What you pay yourself depends mostly on your insurance, deductible and whether every provider is in your network. Our guide to hysterectomy cost explains what is billed, what insurance usually covers and how to ask for an estimate.
Questions to ask your surgeon
Both the FDA and ACOG stress that a surgeon’s training and experience matter.[1][2] These questions can help you understand whether robotic surgery is right for you:
- Why do you recommend a robotic hysterectomy for me, rather than a vaginal or standard laparoscopic one?
- How many robotic hysterectomies do you perform each year?
- How often do you need to switch to open surgery, and what would make that likely in my case?
- Will you remove my cervix, ovaries or fallopian tubes, and why?
- How will the uterus be removed? Will it need to be cut into pieces, and if so, will a containment bag be used?
- How long will I likely stay in hospital, and when can I return to work?
- What will my share of the cost be, and are the anesthesiologist and hospital in my insurance network?
Frequently asked questions
Does the robot perform the surgery?
No. The surgeon controls every movement from the console, and the system cannot act on its own.[2] The robot is a tool that holds and moves the instruments and gives the surgeon a magnified 3D view.
Is a da Vinci hysterectomy the same as a robotic hysterectomy?
Yes. “Da Vinci” is the brand name of the most widely used robotic surgical system. Other systems exist, and the operation is essentially the same whichever one is used.
Is a robotic hysterectomy safer than a laparoscopic one?
For most non-cancerous conditions, studies show similar complication rates.[8][9] The robot may help in more difficult cases, such as severe obesity or a large uterus, where it can avoid open surgery.[10] Your surgeon’s experience with the chosen technique matters more than the technique itself.
Is a robotic hysterectomy less painful?
It is usually less painful than open surgery because the incisions are small. Compared with standard laparoscopy, randomized trials found no difference in pain or painkiller use.[3][5]
How long does a robotic hysterectomy take?
It depends on the size of the uterus, any scar tissue and whether the ovaries, tubes or lymph nodes are also removed. In one randomized trial, the robotic operation took an average of 106 minutes, about half an hour longer than standard laparoscopy.[5] Our article on how long a laparoscopic hysterectomy takes has more detail.
Sources
- American College of Obstetricians and Gynecologists’ Committee on Gynecologic Practice; Society of Gynecologic Surgeons. Robot-assisted surgery for noncancerous gynecologic conditions: ACOG Committee Opinion No. 810. Obstetrics & Gynecology. 2020;136(3):e22–e30. pubmed.ncbi.nlm.nih.gov
- US Food and Drug Administration. Computer-assisted surgical systems. fda.gov
- Paraiso MF, Ridgeway B, Park AJ, et al. A randomized trial comparing conventional and robotically assisted total laparoscopic hysterectomy. American Journal of Obstetrics and Gynecology. 2013;208(5):368.e1–368.e7. pubmed.ncbi.nlm.nih.gov
- US Food and Drug Administration. Power morcellation during gynecologic laparoscopic surgeries. fda.gov
- Sarlos D, Kots L, Stevanovic N, von Felten S, Schär G. Robotic compared with conventional laparoscopic hysterectomy: a randomized controlled trial. Obstetrics & Gynecology. 2012;120(3):604–611. pubmed.ncbi.nlm.nih.gov
- American College of Obstetricians and Gynecologists. Committee Opinion No. 701: Choosing the route of hysterectomy for benign disease. Obstetrics & Gynecology. 2017;129(6):e155–e159. pubmed.ncbi.nlm.nih.gov
- NHS. Hysterectomy: recovery. nhs.uk
- Lawrie TA, Liu H, Lu D, et al. Robot-assisted surgery in gynaecology. Cochrane Database of Systematic Reviews. 2019;4:CD011422. pubmed.ncbi.nlm.nih.gov
- Wright JD, Ananth CV, Lewin SN, et al. Robotically assisted vs laparoscopic hysterectomy among women with benign gynecologic disease. JAMA. 2013;309(7):689–698. pubmed.ncbi.nlm.nih.gov
- Cucinella G, Mathur M, Liu Y, et al. Trends and comparative study of robotic-assisted benign hysterectomy among morbidly obese patients in United States. Journal of Robotic Surgery. 2026;20(1):428. pubmed.ncbi.nlm.nih.gov
- University College London Hospitals NHS Foundation Trust. Robotic hysterectomy: minimal access surgery (patient information). uclh.nhs.uk
- Walker JL, Piedmonte MR, Spirtos NM, et al. Laparoscopy compared with laparotomy for comprehensive surgical staging of uterine cancer: Gynecologic Oncology Group Study LAP2. Journal of Clinical Oncology. 2009;27(32):5331–5336. pubmed.ncbi.nlm.nih.gov
- Ramirez PT, Frumovitz M, Pareja R, et al. Minimally invasive versus abdominal radical hysterectomy for cervical cancer. New England Journal of Medicine. 2018;379(20):1895–1904. pubmed.ncbi.nlm.nih.gov
- Hur HC, Donnellan N, Mansuria S, Barber RE, Guido R, Lee T. Vaginal cuff dehiscence after different modes of hysterectomy. Obstetrics & Gynecology. 2011;118(4):794–801. pubmed.ncbi.nlm.nih.gov
- Alemzadeh H, Raman J, Leveson N, Kalbarczyk Z, Iyer RK. Adverse events in robotic surgery: a retrospective study of 14 years of FDA data. PLoS One. 2016;11(4):e0151470. pubmed.ncbi.nlm.nih.gov
This article is for general information and is not a substitute for medical advice. The right type of hysterectomy depends on your diagnosis, anatomy and medical history, so always discuss your options with your own doctor or surgeon.