Reasons for a Hysterectomy: Common Conditions, Signs to Check and Alternatives
A hysterectomy is the surgical removal of the uterus (womb). It is one of the most common operations in women, but it is rarely the only option. Most hysterectomies are done for conditions that are not cancer: fibroids, heavy periods, endometriosis, adenomyosis and prolapse. For these, the NHS describes hysterectomy as something to consider when other treatments have not worked, symptoms are seriously affecting your life and you do not want any more children.[1] For some cancers, and for a few emergencies, it can be the main or the only treatment.
This guide explains the main reasons doctors recommend a hysterectomy, the symptoms that are worth getting checked, the alternatives for each condition and the questions to ask before you decide. If you want to understand the operation itself first, start with our guide to partial hysterectomy and how it compares with a total hysterectomy.
How common is hysterectomy, and why is it done?
In the United States, about 434,000 inpatient hysterectomies were performed in 2010, down from a peak of about 681,000 in 2002. Over the same years, operations for fibroids, abnormal bleeding, endometriosis and prolapse all fell, as more women were offered treatments that keep the uterus and more surgery moved to outpatient settings.[2]
Fibroids have long been the single most common reason. In a national survey of US hospital records, they accounted for 44% of hysterectomies in 2000 and 39% in 2004.[3] Other common benign (non-cancerous) reasons include abnormal bleeding, endometriosis, prolapse, adenomyosis and chronic pelvic pain.[2] Cancer and precancer make up a smaller share.

Common reasons for a hysterectomy (non-cancerous conditions)
Uterine fibroids
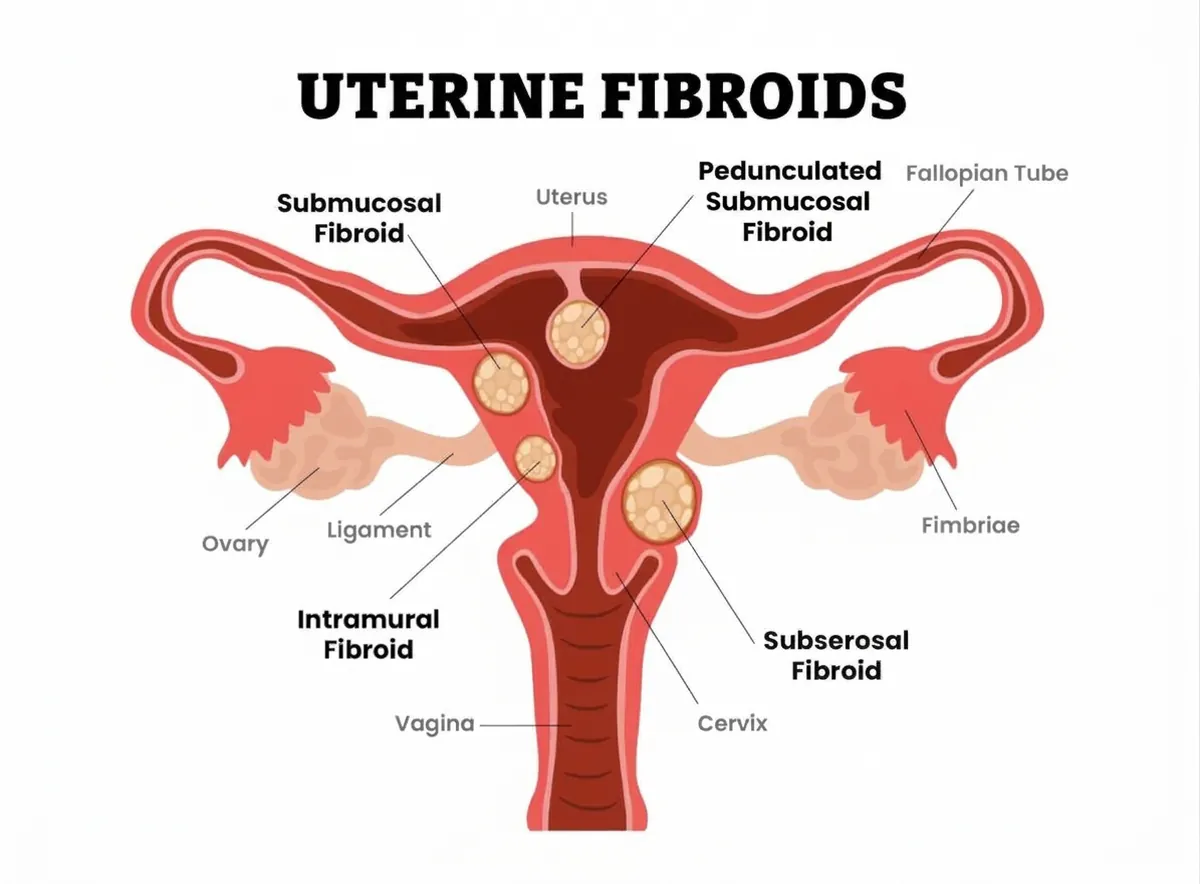
Fibroids are non-cancerous growths of the muscle of the uterus. Many cause no symptoms at all and need no treatment. When they do cause problems, the usual ones are heavy or long periods, pelvic pressure or a swollen tummy, needing to pee often and, sometimes, pain.[4]
Treatment starts with medicines for bleeding and pain. If these do not help, fibroids are very large or symptoms are getting worse, the options include removing only the fibroids (myomectomy), uterine artery embolization, endometrial ablation or a hysterectomy.[4] A hysterectomy is the only treatment that makes sure fibroids cannot come back, but it also ends any chance of pregnancy. Our guide to myomectomy vs hysterectomy for fibroids compares them in detail.
Heavy menstrual bleeding
Heavy periods are now defined by their effect on your life, not by an exact amount of blood: bleeding through pads or tampons, flooding, clots, or periods that leave you tired, anemic or stuck at home.[5] Sometimes a cause is found, such as fibroids, polyps or adenomyosis; often it is not.
Hysterectomy is a second-line treatment. The hormone-releasing intrauterine system (a levonorgestrel IUD, such as Mirena) can reduce menstrual blood loss by up to 90%,[5] and tablets such as tranexamic acid or hormonal medicines also help many women. If these fail, the next step is often endometrial ablation, a short procedure that destroys the lining of the uterus.
A Cochrane review of 10 randomized trials compared ablation with hysterectomy. Ablation meant a much faster return to normal life, by about three weeks compared with open surgery. But women who had a hysterectomy were more likely to see their bleeding improve, and ablation carried a risk of needing further surgery (about 5% to 13% in different comparisons, against none after hysterectomy). Satisfaction was similar or slightly higher after hysterectomy.[6] Both are reasonable choices, and the right one depends on how much you value a quick recovery against a definite end to periods.
Endometriosis
In endometriosis, tissue similar to the lining of the uterus grows outside it, most often on the ovaries, the tubes and the lining of the pelvis. It can cause severe period pain, pain during sex, pain when going to the toilet and fertility problems. Treatment usually starts with painkillers and hormonal medicines, then keyhole surgery to remove or destroy the patches.[1]
A hysterectomy may be considered when these have not worked and you do not want, or cannot have, children. It is important to know that removing the uterus does not remove endometriosis outside it, so the surgeon also needs to remove the visible disease. In a Cleveland Clinic study of 240 women followed for up to 7 years, those who had a hysterectomy were much less likely to need another operation than those who had only the patches removed: 77% of women who kept their ovaries had avoided further surgery after 7 years, compared with 45% after excision alone. Removing the ovaries as well lowered the risk a little more overall (92%), but made no clear difference for women aged 30 to 39.[7] Because removing the ovaries causes immediate menopause, this is a decision to discuss carefully. Read more in our article on hysterectomy for endometriosis.
Adenomyosis
Adenomyosis happens when the lining of the uterus grows into its muscular wall. The uterus becomes bulky and tender, and periods are often heavy and very painful. The same medicines used for heavy and painful periods are tried first. Unlike endometriosis, adenomyosis lives inside the uterus, so a hysterectomy cures it. The NHS notes it is considered only when other treatments have failed and you have finished having children.[1]
Uterine prolapse
A prolapse happens when the muscles and ligaments that hold the uterus weaken, often after childbirth and menopause, and the uterus drops into the vagina. You may feel a heaviness or a bulge, or have trouble with peeing, bowel movements or sex. Pelvic floor exercises and a vaginal pessary (a removable support device) help many women and avoid surgery altogether.
When surgery is needed, a vaginal hysterectomy with repair of the supporting tissues has traditionally been the standard. But it is not the only choice: the uterus can often be stitched back up into place (hysteropexy). A 2025 review of 16 studies with 2,544 women found no clear difference between the two in how often the prolapse came back, how satisfied women were or how often they needed another operation. Hysterectomy took longer, with more blood loss and a slightly longer hospital stay.[8] Our guide to prolapse after hysterectomy explains why support problems can also appear later.
Chronic pelvic pain
Pelvic pain that has lasted six months or more can come from the uterus, but also from the bladder, bowel, muscles, nerves or scar tissue. That is why a hysterectomy for pain alone needs a careful assessment first. In a US study of 308 women who had a hysterectomy for chronic pelvic pain, 74% were pain-free a year later, 21% had less pain and 5% had the same or more pain. Pain was more likely to persist in women in whom no cause had been found in the pelvis.[9]
Pelvic inflammatory disease and other reasons
Pelvic inflammatory disease (PID) is an infection that is treated with antibiotics. A hysterectomy is only considered when a severe infection has left lasting damage and you no longer want children.[1] Less common reasons include a hysterectomy as part of gender-affirming care for some transgender and nonbinary people,[10] and conditions such as polycystic ovary syndrome (PCOS), where hysterectomy is rarely the answer and is usually reserved for other problems that occur alongside it.
Cancer and precancer
For cancer of the uterus (endometrial cancer), surgery is the main treatment and usually includes a total hysterectomy, removing the uterus and cervix, often with the tubes and ovaries.[11] A hysterectomy is also recommended for cancers of the cervix, ovary and fallopian tube, and for advanced cancer it may be the only option.[1] Early cervical cancer is sometimes treated with a radical hysterectomy, which removes extra tissue around the cervix; see do you need a radical hysterectomy for cervical cancer.
Some changes are not cancer yet but can become cancer:
- Atypical endometrial hyperplasia (also called endometrial intraepithelial neoplasia): a thickened lining with abnormal cells. Hysterectomy is the definitive treatment. Women who want to keep their fertility can be treated with progestin, often through a hormonal IUD, with close follow-up.[12]
- Abnormal cervical cells (cervical dysplasia): these are usually treated with a small procedure on the cervix, not a hysterectomy. Our guide to LEEP for cervical dysplasia explains when a hysterectomy is considered.
- Inherited cancer risk: women with Lynch syndrome have a high lifetime risk of cancer of the uterus and ovaries. In a study of 315 women with Lynch syndrome, none of those who had a preventive hysterectomy and removal of the ovaries developed these cancers, while 33% of the comparison group developed endometrial cancer.[13] Preventive surgery is usually discussed once you have finished having children.
Emergency hysterectomy
Rarely, a hysterectomy is done as an emergency to save a life. The most common situation is severe bleeding after childbirth that cannot be controlled in any other way, for example when the placenta has grown too deeply into the wall of the uterus. Doctors try other measures first whenever possible. Heavy bleeding from a large fibroid or serious injury to the uterus are other, uncommon reasons.
At a glance: when a hysterectomy is considered
| Condition | When a hysterectomy is considered | Options that keep the uterus |
|---|---|---|
| Fibroids | Symptoms persist despite treatment, or fibroids are very large; no wish for pregnancy | Medicines, myomectomy, uterine artery embolization, ablation |
| Heavy periods | Other treatments have failed and you want periods to stop for good | Hormonal IUD, tranexamic acid, hormonal medicines, ablation |
| Endometriosis | Pain continues after medicines and surgery; family complete | Hormonal medicines, keyhole excision of the patches |
| Adenomyosis | Other treatments have failed; family complete | Hormonal IUD, hormonal medicines, painkillers |
| Prolapse | Symptoms are troublesome and surgery is chosen | Pelvic floor exercises, pessary, hysteropexy |
| Chronic pelvic pain | Pain clearly comes from the uterus and other causes have been looked for | Depends on the cause; pain management, physiotherapy |
| Atypical hyperplasia | Usually recommended | Progestin treatment with close follow-up, if fertility matters |
| Cancer | Usually the main treatment | Rarely; only in selected early cases |
Signs and symptoms worth getting checked
No symptom on its own means you need a hysterectomy. But these are worth discussing with a doctor, who can find the cause and talk you through all the options:
- Periods so heavy that you flood, pass large clots, change protection every hour or two, or feel tired and breathless (possible anemia).
- Bleeding between periods or after sex.
- Period pain that painkillers do not control, or pelvic pain on most days for months.
- Pain during sex, or when you pee or have a bowel movement around your period.
- A feeling of heaviness or a bulge in the vagina.
- A swollen lower tummy, pelvic pressure or needing to pee much more often.
Any bleeding after menopause needs to be checked by a doctor, even if it is only spotting or happens once. It is usually caused by something harmless, such as thinning of the vaginal lining or a polyp, but it can be an early sign of cancer of the uterus.[14] Get urgent medical help if you have very heavy bleeding with dizziness or fainting, or sudden severe pelvic pain with fever.
Does a hysterectomy solve the problem?
For most women having a hysterectomy for a benign condition, yes. In the Maryland Women’s Health Study, which followed 1,299 women for two years, symptoms such as problem bleeding, pelvic pain and fatigue improved a lot, and depression and anxiety scores fell. About 8% of women, however, still had as many severe symptoms two years later as before surgery.[15] Results are best when there is a clear cause in the uterus, which is why a good diagnosis before surgery matters.
It is also a major operation, with risks such as bleeding, infection and injury to the bladder or bowel, and a recovery of several weeks. If the ovaries are removed before menopause, you will go into surgical menopause. Keeping healthy ovaries is often possible, while removing the fallopian tubes at the same time is now recommended by the American College of Obstetricians and Gynecologists because it lowers the risk of the most common type of ovarian cancer.[16]
Questions to ask your doctor
- What exactly is causing my symptoms, and how sure are we?
- Which treatments that keep my uterus could I still try, and what are their chances of working?
- What would happen if I waited? (If you are close to menopause, this can change the answer.)
- What type of hysterectomy do you recommend, and why? Will my cervix, tubes or ovaries be removed?
- Can it be done by keyhole or through the vagina rather than through an open cut?
- How long will recovery take, and when can I go back to work?
The NHS also suggests asking yourself whether your symptoms seriously affect your quality of life, whether you have explored all the other options, and whether you might still want children.[1] A second opinion is reasonable for any planned operation. If your doctor is reluctant to operate, our article on getting a hysterectomy without a medical reason explains how these decisions are made, and our checklist for preparing for a hysterectomy helps once you have decided.
Sources
- NHS. Hysterectomy: why it’s done. nhs.uk
- Wright JD, Herzog TJ, Tsui J, et al. Nationwide trends in the performance of inpatient hysterectomy in the United States. Obstetrics & Gynecology. 2013;122(2 Pt 1):233–241. pubmed.ncbi.nlm.nih.gov
- Whiteman MK, Hillis SD, Jamieson DJ, et al. Inpatient hysterectomy surveillance in the United States, 2000–2004. American Journal of Obstetrics and Gynecology. 2008;198(1):34.e1–7. pubmed.ncbi.nlm.nih.gov
- NHS. Fibroids: treatment. nhs.uk
- Bofill Rodriguez M, Lethaby A, Jordan V. Progestogen-releasing intrauterine systems for heavy menstrual bleeding. Cochrane Database of Systematic Reviews. 2020;6(6):CD002126. pubmed.ncbi.nlm.nih.gov
- Bofill Rodriguez M, Lethaby A, Fergusson RJ. Endometrial resection and ablation versus hysterectomy for heavy menstrual bleeding. Cochrane Database of Systematic Reviews. 2021;2(2):CD000329. pubmed.ncbi.nlm.nih.gov
- Shakiba K, Bena JF, McGill KM, et al. Surgical treatment of endometriosis: a 7-year follow-up on the requirement for further surgery. Obstetrics & Gynecology. 2008;111(6):1285–1292. pubmed.ncbi.nlm.nih.gov
- Ruffolo AF, Salvatore S, Torella M, et al. The uterus debate in vaginal native tissue repair for pelvic organ prolapse: hysteropexy versus hysterectomy. A systematic review and meta-analysis. Maturitas. 2025;203:108755. pubmed.ncbi.nlm.nih.gov
- Hillis SD, Marchbanks PA, Peterson HB. The effectiveness of hysterectomy for chronic pelvic pain. Obstetrics & Gynecology. 1995;86(6):941–945. pubmed.ncbi.nlm.nih.gov
- Coleman E, Radix AE, Bouman WP, et al. Standards of Care for the Health of Transgender and Gender Diverse People, Version 8. International Journal of Transgender Health. 2022;23(Suppl 1):S1–S259. pubmed.ncbi.nlm.nih.gov
- American Cancer Society. Surgery for endometrial cancer. cancer.org
- American College of Obstetricians and Gynecologists. Management of endometrial intraepithelial neoplasia or atypical endometrial hyperplasia: ACOG Clinical Consensus No. 5. Obstetrics & Gynecology. 2023;142(3):735–744. pubmed.ncbi.nlm.nih.gov
- Schmeler KM, Lynch HT, Chen LM, et al. Prophylactic surgery to reduce the risk of gynecologic cancers in the Lynch syndrome. New England Journal of Medicine. 2006;354(3):261–269. pubmed.ncbi.nlm.nih.gov
- NHS. Postmenopausal bleeding. nhs.uk
- Kjerulff KH, Langenberg PW, Rhodes JC, et al. Effectiveness of hysterectomy. Obstetrics & Gynecology. 2000;95(3):319–326. pubmed.ncbi.nlm.nih.gov
- American College of Obstetricians and Gynecologists. ACOG Clinical Practice Update: Salpingectomy for the prevention of epithelial ovarian cancer. Obstetrics & Gynecology. 2026;148(4):e275–e280. pubmed.ncbi.nlm.nih.gov
This article is for general information and is not a substitute for medical advice. Always discuss your own situation with your gynecologist or doctor, and contact them or emergency services if you are worried about any symptom.