PCOS and Hysterectomy: Does It Help, and What Are the Alternatives?
If you live with polycystic ovary syndrome (PCOS) and years of irregular or heavy periods, acne, unwanted hair or fertility treatment have worn you down, it is natural to wonder whether a hysterectomy would end it all. The short answer is no: a hysterectomy does not cure PCOS. PCOS is a hormonal and metabolic condition that involves the whole body, not just the uterus, and removing the uterus leaves most of it in place.[1][2] There are a few situations in which someone with PCOS may still need or reasonably choose a hysterectomy, and this guide explains what the operation can and cannot change, when it is considered, and the treatments that are usually tried first.
What PCOS is
PCOS is one of the most common hormonal conditions in women. The World Health Organization (WHO) estimates that it affects 10 to 13% of women of reproductive age, and that up to 70% of them have not been diagnosed.[1] It usually starts around puberty and is linked to higher levels of androgens (hormones such as testosterone, which women also make in smaller amounts) and to insulin resistance, where the body needs more insulin than usual to keep blood sugar normal.[1][4]
Adults are diagnosed when they have at least two of these three features, once other causes have been ruled out:[1][2]
- Irregular or absent periods, because ovulation happens rarely or not at all.
- Signs of high androgens: excess facial or body hair, acne, scalp hair thinning, or raised testosterone on a blood test.
- Polycystic ovaries on ultrasound (or a raised anti-Müllerian hormone level in adults).
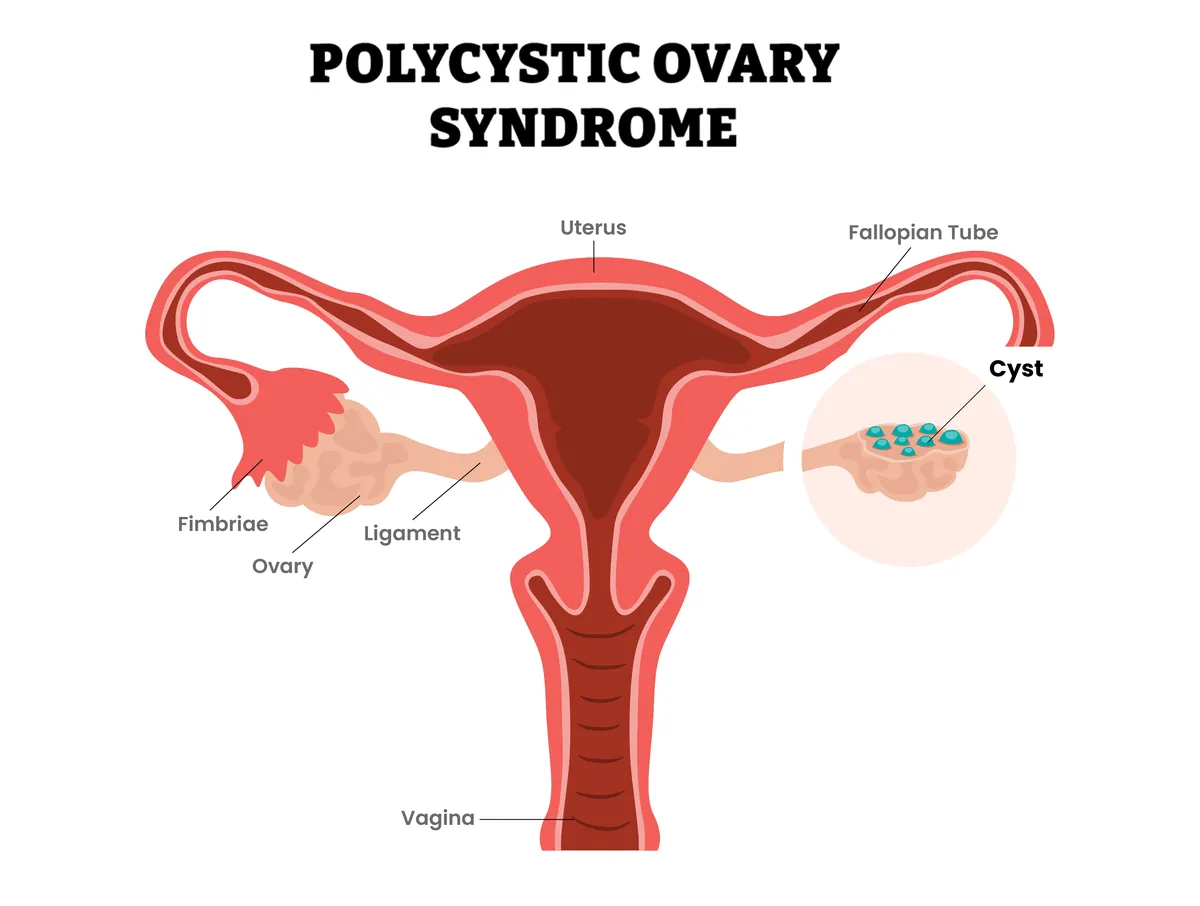
Despite the name, these are not true cysts. They are small egg-containing follicles that stopped developing, and you do not need them to be diagnosed.[1] Partly for this reason, an international consensus published in The Lancet in May 2026 renamed the condition polyendocrine metabolic ovarian syndrome (PMOS), a name that puts the hormonal and metabolic sides first. The new name is being introduced over three years, so you will see both terms for a while.[3] This article uses PCOS because it is still the name most people search for.
Symptoms and long-term health
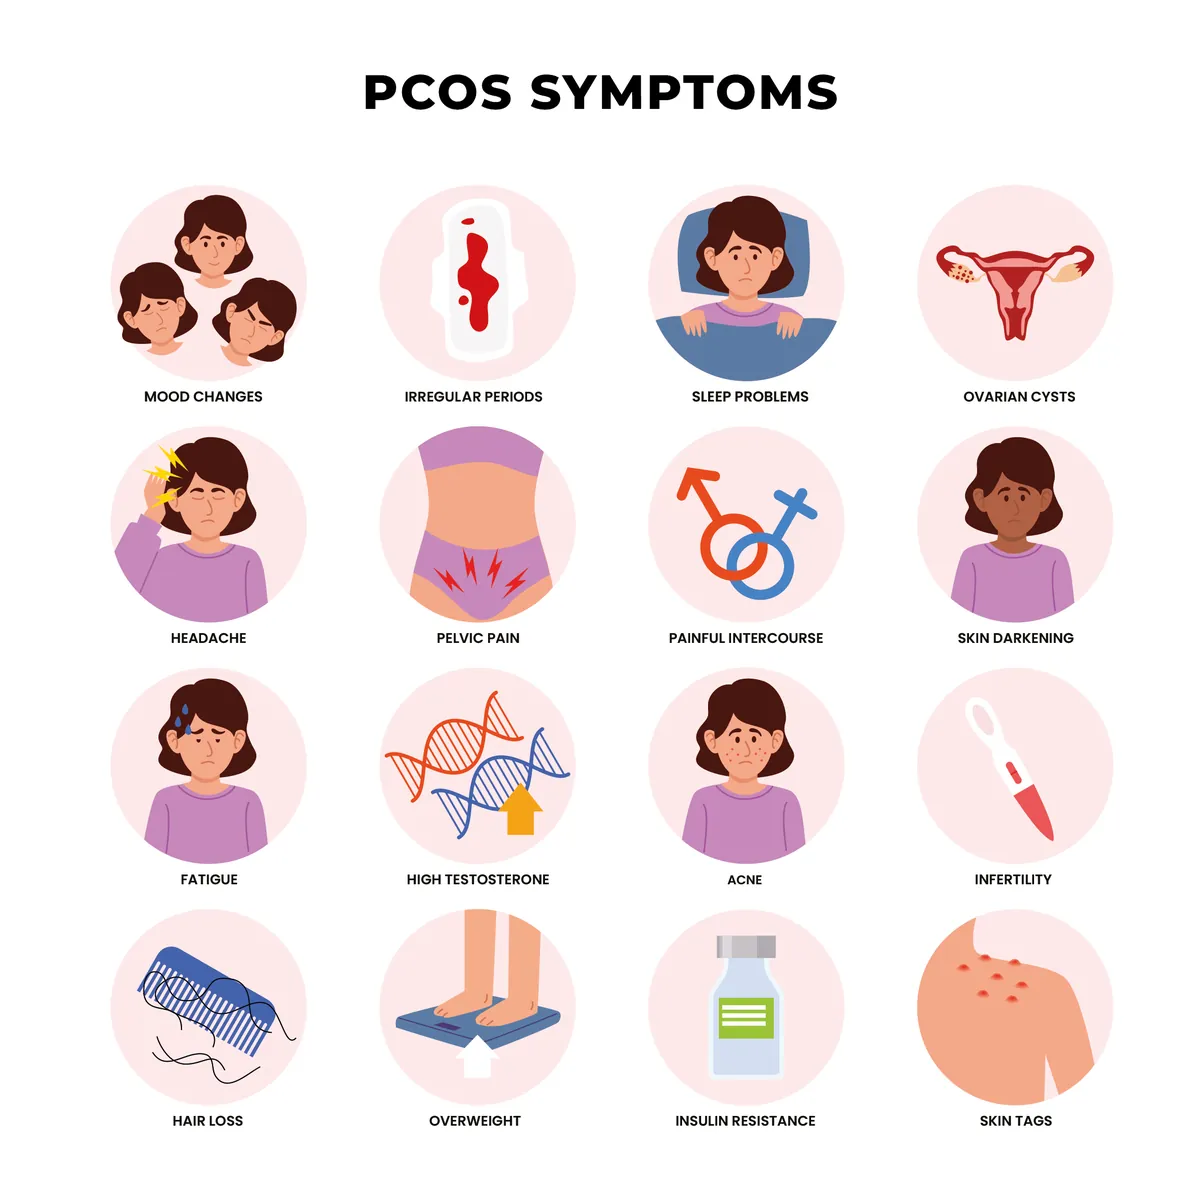
PCOS looks different in each person. Common symptoms include irregular, heavy or absent periods, difficulty getting pregnant, excess hair, scalp hair loss, acne or oily skin, weight gain, tiredness, darker patches of skin on the neck or armpits, and low mood or anxiety.[1][4]
Over the long term, PCOS raises the risk of type 2 diabetes, high blood pressure, high cholesterol, heart disease, sleep apnea, fatty liver disease and cancer of the lining of the uterus (endometrial cancer).[1][4] The international PCOS guideline therefore recommends checking blood sugar at diagnosis and every one to three years, a cholesterol test at diagnosis, a blood pressure check every year, and screening for depression and anxiety.[2]
Why a hysterectomy does not cure PCOS
A hysterectomy removes the uterus. Whether the ovaries are also removed (an oophorectomy) is a separate decision, and it changes the picture a great deal. Our guide to partial vs total hysterectomy explains the different operations.
If the ovaries are kept
The ovaries carry on making hormones, including androgens, and insulin resistance is not affected by removing the uterus. In practice:
- What changes: periods stop, so irregular and heavy bleeding ends. Because the lining of the uterus is gone, so is the risk of endometrial cancer, one of the more serious long-term risks of PCOS.[2][5] Pregnancy is no longer possible.
- What stays the same: excess hair, acne, scalp hair thinning, insulin resistance and the higher risk of diabetes and heart disease. Mood symptoms linked to PCOS do not go away either.[1][2]
Keeping the ovaries means there is no sudden menopause. You will still go through menopause at around the usual age; our article on menopause after a hysterectomy with ovaries intact explains how to recognise it without periods.
If the ovaries are removed too
Removing both ovaries takes away the main source of the excess androgens, so hair growth and acne may improve. But it also causes an immediate surgical menopause, with hot flushes, vaginal dryness, poorer sleep and faster bone loss, and it does not fix insulin resistance or the metabolic risks of PCOS.[1][2] Our guide to menopause after a total hysterectomy covers what to expect.
Removing healthy ovaries before menopause also has long-term costs. In the US Nurses’ Health Study, which followed about 30,000 women for up to 28 years after a hysterectomy for non-cancerous conditions, those who had both ovaries removed had a higher overall death rate than those who kept them (16.8% vs 13.3%), with more deaths from coronary heart disease and lung cancer, even though they had fewer deaths from ovarian cancer.[6] This was an observational study, so it cannot prove cause and effect, but it is one reason surgeons usually advise keeping healthy ovaries in women who are not at high risk of ovarian cancer. In the same study, the extra risk in women under 50 was seen mainly in those who never used estrogen therapy,[6] which is one reason hormone therapy is usually discussed after an early surgical menopause; see our page on hysterectomy and hormones.
At a glance: what a hysterectomy changes in PCOS
| Hysterectomy, ovaries kept | Hysterectomy with both ovaries removed | |
|---|---|---|
| Periods and heavy bleeding | Stop | Stop |
| Endometrial cancer risk | Removed with the uterus | Removed with the uterus |
| Excess hair and acne | Usually unchanged | Often improve |
| Insulin resistance, diabetes and heart risk | Unchanged | Unchanged; heart risk may rise without hormone therapy |
| Menopause | At the natural time | Immediately |
| Pregnancy | Not possible | Not possible |
When a hysterectomy may be considered
Hysterectomy is not a treatment for PCOS itself, and none of the international PCOS recommendations include it.[2] But having PCOS does not rule out a hysterectomy for another reason. The situations in which it comes up are:
- Endometrial cancer. In a 2014 meta-analysis, women with PCOS had about 2.8 times the odds of endometrial cancer compared with women without PCOS.[5] The absolute risk is still low, and the guideline does not recommend routine screening,[2] but if endometrial cancer is found, surgery to remove the uterus is usually the main treatment.[7] Any bleeding after menopause, or bleeding that changes pattern, should be checked.
- Heavy or irregular bleeding that has not responded to other treatment, once you are sure you do not want a future pregnancy. A hormonal IUD or other progestogen treatment is usually tried first, because it both controls bleeding and protects the lining of the uterus.[2][4]
- Another condition of the uterus, such as fibroids, adenomyosis or endometriosis, that is causing symptoms and has not responded to other options. Our articles on myomectomy vs hysterectomy for fibroids and hysterectomy for endometriosis cover these choices.
In each case the operation treats the other problem, not the PCOS. You will still need the usual checks for blood sugar, cholesterol, blood pressure and mood afterwards. For a wider view of why hysterectomies are done, see the reasons for a hysterectomy.
Treatments that work for PCOS
There is no cure for PCOS, but its symptoms and risks can be managed well.[1] The 2023 international guideline, developed with patient groups and the main endocrine and fertility societies, recommends treatment based on which symptoms bother you most.[2]
- Healthy lifestyle: recommended for everyone with PCOS. Healthy eating and physical activity improve metabolic health even if your weight does not change; the guideline suggests 150 to 300 minutes of moderate activity a week plus muscle strengthening twice a week.[2]
- Combined hormonal contraception: regulates periods, protects the lining of the uterus and can reduce excess hair and acne.[1][2]
- Progestogen treatment: a hormonal IUD or regular courses of progestogen tablets are options for protecting the lining of the uterus if you do not use the combined pill.[2][4]
- Metformin: a diabetes medicine that improves insulin resistance. The guideline suggests considering it, especially for adults with a higher body weight, alongside lifestyle changes.[2]
- Anti-androgen medicines such as spironolactone: for unwanted hair that has not improved enough after at least six months of the pill or cosmetic treatment. They must be used with reliable contraception because they could harm a developing baby.[2]
- Weight-loss medicines and surgery: for adults with a higher body weight, medicines such as semaglutide or liraglutide, or bariatric surgery, may be considered alongside lifestyle changes.[2]
- Mental health support: talking therapy or other treatment for depression or anxiety, which are more common with PCOS.[2][4]
If you want to get pregnant
Many women with PCOS get pregnant, some with help. The guideline recommends letrozole, a tablet taken for a few days each cycle, as the first medicine to trigger ovulation. If it does not work, the next options are injections of fertility hormones (gonadotrophins) or a keyhole operation on the ovaries called laparoscopic ovarian drilling, and then IVF.[2][4] A hysterectomy rules out carrying a pregnancy, so it is worth being sure about future plans before it is considered; our article on IVF after a hysterectomy explains the options if your ovaries are kept.
Questions to ask your doctor
- Which of my symptoms come from PCOS, and which might have another cause?
- What would a hysterectomy change for me, and what would stay the same?
- Would you keep my ovaries? If not, why, and would I need hormone therapy?
- Have I tried the medical options for my bleeding, such as a hormonal IUD?
- Is the lining of my uterus being protected, and do I need any tests for it?
- When were my blood sugar, cholesterol and blood pressure last checked?
- Could I see an endocrinologist or a gynecologist with experience in PCOS?
When to seek medical help
Contact a doctor promptly if you have:
- Any bleeding after menopause, or bleeding between periods or after sex.
- No period for more than three months without a known reason such as pregnancy or hormonal contraception.
- Very heavy bleeding, such as soaking a pad every hour for several hours, or feeling faint, dizzy or short of breath.
- Extreme thirst, passing a lot of urine or unexplained weight loss, which can be signs of diabetes.
- Sudden, severe pelvic pain, especially with fever or vomiting.
- Low mood or anxiety that affects your daily life, or thoughts of harming yourself; in that case seek help the same day.
Frequently asked questions
Will a hysterectomy stop my PCOS symptoms?
It will stop periods, and with them irregular or heavy bleeding. Symptoms driven by androgens and insulin resistance, such as excess hair, acne, weight gain and fatigue, usually continue if the ovaries are kept.
Does removing the ovaries cure PCOS?
No. It lowers androgen levels, so hair growth and acne may improve, but insulin resistance and the metabolic risks remain, and it causes an immediate menopause with its own health effects.[1][6]
Can you still have PCOS after a hysterectomy?
Yes. PCOS is a lifelong hormonal and metabolic condition, and a hysterectomy does not change the diagnosis. Without periods it is harder to track, so regular checks of blood sugar, cholesterol and blood pressure remain important. If your ovaries were kept, they can still form cysts and follicles; our article on ovarian cysts after a hysterectomy explains when to worry.
Does PCOS go away after menopause?
Periods stop at menopause, so problems with the menstrual cycle end. The metabolic side of PCOS, such as the higher risk of diabetes and heart disease, continues, so the regular health checks are still worthwhile.[1][2]
Sources
- World Health Organization. Polycystic ovary syndrome. Fact sheet. who.int
- Teede HJ, et al. Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Human Reproduction. 2023;38(9):1655–1679. academic.oup.com
- Endocrine Society. Polyendocrine Metabolic Ovarian Syndrome: new name to improve diagnosis and care of condition affecting 170 million women worldwide. Press release, May 12, 2026. endocrine.org
- NHS. Polycystic ovary syndrome. nhs.uk
- Barry JA, Azizia MM, Hardiman PJ. Risk of endometrial, ovarian and breast cancer in women with polycystic ovary syndrome: a systematic review and meta-analysis. Human Reproduction Update. 2014;20(5):748–758. pubmed.ncbi.nlm.nih.gov
- Parker WH, et al. Long-term mortality associated with oophorectomy versus ovarian conservation in the Nurses’ Health Study. Obstetrics & Gynecology. 2013;121(4):709–716.pubmed.ncbi.nlm.nih.gov
- NHS. Womb (uterus) cancer: treatment. nhs.uk
This article is for general information and is not a substitute for medical advice. Always discuss your own situation with your gynecologist or doctor, and contact them or emergency services if you are worried about any symptom.