Alternatives to Hysterectomy: Options for Fibroids, Heavy Periods, Prolapse and More
A hysterectomy is a good operation when it is the right one, but for most non-cancerous problems it is not the only choice. Fibroids, heavy periods, adenomyosis, endometriosis and prolapse can all be treated in ways that keep the uterus, and guidelines in the US and the UK ask doctors to offer these options before, or alongside, a hysterectomy.[1][2] Some of them are tablets or a hormonal IUD; others are short procedures with a recovery measured in days rather than weeks.
This guide goes through the alternatives condition by condition, with what the research says about how well each one works and how often women end up needing a hysterectomy later anyway. If you are not sure why a hysterectomy was suggested in the first place, start with our guide to the reasons for a hysterectomy.
Key points
- For heavy periods, UK guidelines recommend a hormonal IUD as the first treatment to consider. Hysterectomy comes after medicines and simpler procedures have been discussed.[2]
- Fibroids can be treated with medicines, removal of the fibroids only (myomectomy), uterine artery embolization or radiofrequency ablation. Satisfaction after embolization and after surgery was similar in randomized trials, but more women needed another procedure after embolization.[1][7]
- Endometrial ablation is a short procedure for heavy bleeding. About 1 in 8 women have a hysterectomy within 5 years, and the risk is higher in women under 40.[5][6]
- Prolapse can often be managed with pelvic floor training or a pessary, and when surgery is needed the uterus can often be lifted and kept.[17][18][19]
- A hysterectomy is the only treatment that guarantees fibroids and adenomyosis cannot come back, and it is still the standard treatment for cancer of the uterus.[1][13]
Before you choose: the questions that decide it
The best alternative depends less on the name of the condition than on a few practical questions. It is worth having clear answers to them before your appointment:
- Do you want the option of a future pregnancy? If yes, a hysterectomy and endometrial ablation are usually off the table, and myomectomy is often preferred over other fibroid procedures.[1][8]
- What bothers you most? Heavy bleeding, pain, pressure on the bladder or bowel, and a bulge in the vagina respond to different treatments.
- How close are you to menopause? Fibroids and heavy bleeding usually settle after menopause, so a treatment that controls symptoms for a few years may be all that is needed.
- How do you feel about a second procedure? Most alternatives have a higher chance of needing further treatment than a hysterectomy. Some women accept this to avoid a bigger operation; others prefer a definite answer.
- Has cancer or precancer been ruled out? Bleeding after menopause, bleeding between periods or a fast-growing mass need to be checked before any treatment is chosen.
Our checklist of questions to ask before a hysterectomy is useful for any of these conversations.
Alternatives for heavy menstrual bleeding
Heavy periods are now judged by their effect on your life, not by an exact amount of blood. Guidelines say treatment should aim to improve quality of life rather than focus on blood loss.[2]
Hormonal IUD (levonorgestrel intrauterine system)
A small T-shaped device placed in the uterus releases a progestogen that thins the lining. NICE, the body that writes clinical guidelines for England, recommends considering it as the first treatment for heavy periods when no cause is found, when fibroids are smaller than 3 cm and do not distort the cavity, or when adenomyosis is suspected.[2] A Cochrane review of 25 trials found that it probably reduces blood loss more than tablets do.[3] It is placed in the clinic in a few minutes and lasts several years. Irregular spotting is common in the first months, and periods often become very light or stop.
Tablets
If an IUD is not wanted or not suitable, the options are non-hormonal tablets taken only during the period (tranexamic acid, which helps the blood clot, and anti-inflammatory painkillers such as mefenamic acid or naproxen), or hormonal ones (the combined pill or cyclical progestogen tablets).[2] They do not change the uterus, so they work only while you take them.
Endometrial ablation
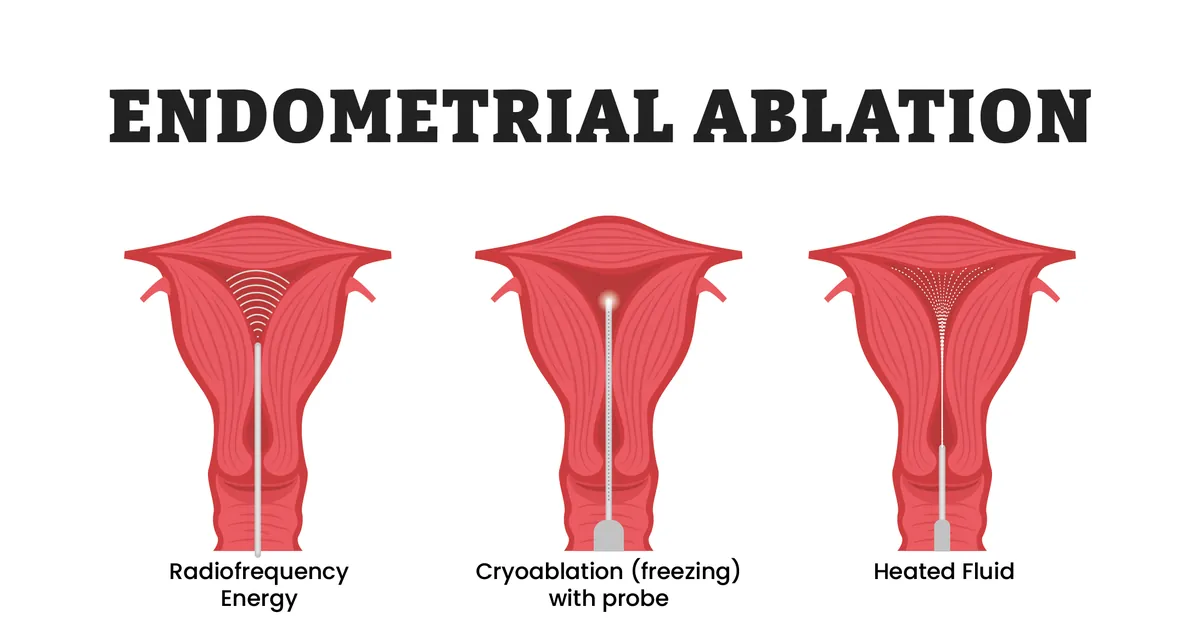
Ablation destroys the lining of the uterus with heat, cold, radiofrequency or microwave energy, using an instrument passed through the cervix. There are no cuts on the abdomen and most women go home the same day. NICE suggests it when medicines have failed or are not wanted.[2] It is only for women who do not want a future pregnancy and have not reached menopause. Contraception is still needed afterwards: pregnancy after ablation is unlikely but possible, and the risk of miscarriage and other problems is much higher.[22]
A Cochrane review of trials comparing ablation with hysterectomy found that women recovered about three weeks faster after ablation, but women who had a hysterectomy were more likely to see their bleeding improve and satisfaction was similar or slightly higher after hysterectomy.[4] The main drawback is that ablation does not always last:
- In a 2023 review of 53 studies with more than 48,000 women, 4.3% had a hysterectomy within a year of ablation and 12.4% within five years. Two studies that followed women for 10 years found about 21%.[5]
- In a US study of 3,681 women treated at Kaiser Permanente in Northern California, 21% later had a hysterectomy. Age mattered more than the type of device: the risk was more than 40% in women aged 40 or younger.[6]
Ablation also does not shrink fibroids. Fibroids inside the cavity (submucosal) can instead be removed through the cervix with a camera (hysteroscopic myomectomy).[2]
Alternatives for fibroids
Fibroids are non-cancerous growths of the muscle of the uterus. Many cause no symptoms, and fibroids that are not causing problems do not need treatment.[12] ACOG, the US college of obstetricians and gynecologists, notes that many women look for options other than hysterectomy because they want to keep the possibility of pregnancy or simply wish to keep their uterus.[1]
Medicines
- For bleeding: the same tablets and hormonal IUD used for heavy periods, although they work less well when fibroids are much larger than 3 cm or distort the cavity.[2]
- Hormone-lowering medicines (GnRH medicines): they shrink fibroids, but cause menopause-like symptoms and bone loss, so they are used for short periods, often to shrink fibroids before surgery.[1][2]
- Relugolix combination tablet (Myfembree): a once-daily tablet that combines a hormone blocker with low-dose hormones to protect against menopause symptoms. The FDA approved it in 2021 for heavy bleeding caused by fibroids, for up to 24 months because of the risk of bone loss.[10]
Myomectomy (removing only the fibroids)
A myomectomy removes the fibroids and repairs the uterus. It can be done through the cervix (for fibroids inside the cavity), by keyhole surgery or through a cut in the abdomen. It is the usual choice for women who want to get pregnant.[1] New fibroids can grow afterwards. Our guide to myomectomy vs hysterectomy compares the two operations in detail.
Uterine artery embolization (UAE)
An interventional radiologist passes a thin tube through an artery in the groin or wrist and releases tiny particles that block the blood supply to the fibroids, which then shrink.[12] It is done through a small puncture rather than a surgical cut.
- A Cochrane review of 7 randomized trials with 793 women found no clear difference in satisfaction between UAE and surgery (hysterectomy or myomectomy) at two or five years. UAE meant a shorter hospital stay, a faster return to normal activities and fewer blood transfusions, but more minor complications.[7]
- The same review estimated that if 7% of women need another operation within two years of surgery, 15% to 32% would need one within two years of UAE.[7]
- In the UK FEMME trial of 254 women who wanted to avoid a hysterectomy, myomectomy gave a modestly better quality of life after two years and fewer repeat procedures (7% vs 16%), while UAE meant a shorter hospital stay (2 vs 4 days).[8]
Radiofrequency ablation and focused ultrasound
These treatments destroy fibroids in place without removing them. Radiofrequency ablation uses a needle placed into the fibroid during keyhole surgery, through the vagina or through the cervix. A 2019 review of 32 prospective studies with 1,283 women found that fibroids shrank by about two-thirds after 12 months, women returned to work after about 5 days, and about 11.5% needed another fibroid procedure within 3 years.[9] One of the authors was a consultant to a company that makes one of these devices. MRI-guided focused ultrasound heats fibroids from outside the body. Both are suitable only for some fibroids, data on pregnancy afterwards are limited, and neither is available in every hospital.[1]
Alternatives for adenomyosis
In adenomyosis, the lining of the uterus grows into its muscular wall, causing heavy and painful periods. The NHS lists the hormonal IUD as the main treatment, with other hormonal contraception, anti-inflammatory painkillers and tranexamic acid as options. If these do not work, uterine artery embolization is a possibility. Because adenomyosis lives inside the uterus, a hysterectomy is the only way to cure it.[13]
Alternatives for endometriosis
Endometriosis grows mostly outside the uterus, so a hysterectomy on its own does not remove it.[14] The European guideline recommends painkillers and hormonal treatment (the pill, progestogens, a hormonal IUD or GnRH medicines) and keyhole surgery to remove the visible disease, with hysterectomy reserved for women who have finished having children and whose symptoms continue.[14] In 2022 the FDA also approved the relugolix combination tablet for moderate to severe endometriosis pain.[11]
Removing the uterus can still help, especially when adenomyosis is also present. In a Cleveland Clinic study, women who had a hysterectomy were less likely to need further surgery over 7 years than women who had only the endometriosis removed.[15] Our guide to hysterectomy for endometriosis explains these trade-offs, including whether to keep the ovaries.
Alternatives for uterine prolapse
A prolapse happens when the uterus drops into the vagina because its supports have weakened. If it does not bother you, no treatment is needed.[16]
Pelvic floor muscle training
In the POPPY trial of 447 women with mild to moderate prolapse in the UK, New Zealand and Australia, one-to-one pelvic floor training with a physical therapist reduced prolapse symptoms more than a leaflet with lifestyle advice after 12 months.[17] Training also helps bladder leaks, and it is worth doing before and after any surgery.
Pessary
A pessary is a removable ring or other shape, made of silicone, that sits in the vagina and holds the organs up. It is fitted in the clinic. In the Dutch PEOPLE trial, 440 women were randomly assigned to start with a pessary or with surgery. After two years, 76% of the pessary group and 82% of the surgery group felt much better; the pessary did not prove as good as surgery, partly because 54% of the women who started with a pessary switched to surgery. Discomfort was the most common problem with pessaries.[18] A pessary is still a reasonable first step, and a good long-term choice for women who prefer to avoid or delay an operation.
Surgery that keeps the uterus (hysteropexy)
When surgery is chosen, the uterus can often be stitched back into place rather than removed. A 2025 review of 16 studies with 2,544 women found no clear difference between hysteropexy and vaginal hysterectomy in how often the prolapse came back, how satisfied women were or how often they needed more surgery.[19] Our guide to prolapse after hysterectomy explains why support problems can also appear after the uterus is removed.
Alternatives for precancer and chronic pelvic pain
- Atypical endometrial hyperplasia (a thickened lining with abnormal cells): hysterectomy is the standard treatment, but women who want to keep their fertility, or who cannot safely have surgery, can be treated with a progestin, often through a hormonal IUD, with regular biopsies.[20]
- Abnormal cervical cells (cervical dysplasia): these are usually treated with a small procedure on the cervix. Our guide to LEEP for cervical dysplasia explains when a hysterectomy is considered.
- Chronic pelvic pain: pain can come from the bladder, bowel, muscles or nerves as well as the uterus, so the cause needs to be looked for first. In a US study of 308 women who had a hysterectomy for chronic pelvic pain, most improved, but pain was more likely to persist when no cause had been found in the pelvis.[21]
Alternatives at a glance
| Condition | Try first | Procedures that keep the uterus | Pregnancy still possible? |
|---|---|---|---|
| Heavy periods | Hormonal IUD, tranexamic acid, anti-inflammatories, hormonal tablets | Endometrial ablation; hysteroscopic removal of fibroids or polyps | Not after ablation |
| Fibroids | Watching, tablets for bleeding, hormonal IUD, relugolix combination | Myomectomy, uterine artery embolization, radiofrequency ablation, focused ultrasound | Yes, best studied after myomectomy |
| Adenomyosis | Hormonal IUD, hormonal tablets, painkillers, tranexamic acid | Uterine artery embolization | Discuss with your doctor |
| Endometriosis | Painkillers, hormonal treatment | Keyhole excision of the disease | Yes |
| Prolapse | Pelvic floor training, pessary | Hysteropexy | Discuss with your doctor |
| Atypical hyperplasia | Progestin, often by hormonal IUD, with close follow-up | — | Yes, with specialist care |
When a hysterectomy is the better choice
An alternative is not always the right answer. A hysterectomy is usually recommended for cancer of the uterus or cervix (see our guide to hysterectomy for cervical cancer), and it is a reasonable choice when other treatments have not worked, when fibroids are very large or numerous, or when you want a definite end to bleeding and do not want a future pregnancy.[1][2] Many women who choose a hysterectomy after trying other options are glad they did.
If you decide on surgery, you still have choices: keeping the cervix or not, keeping the ovaries, and having keyhole rather than open surgery. Our guide to partial hysterectomy explains the types, and our article on hysterectomy cost covers what insurance usually pays for, which also matters when comparing options.
When to seek urgent care
Whatever treatment you are using or considering, contact your doctor urgently or go to the emergency room if you have:
- Bleeding that soaks a pad or tampon every hour for two hours or more, or large clots with dizziness or fainting
- Severe pain in the lower abdomen that painkillers do not help
- A fever, or foul-smelling discharge, after any procedure on the uterus
- Any bleeding after menopause (this always needs to be checked, though not usually as an emergency)
Frequently asked questions
Can fibroids shrink without treatment?
Fibroids mainly affect women who have not been through menopause.[12] Hormone-lowering medicines (GnRH medicines) shrink them, but only for as long as they are taken, which is why they are mostly used for short periods before surgery.[1][2] Uterine artery embolization and radiofrequency ablation shrink fibroids for longer.[7][9]
Which alternative is least likely to need a hysterectomy later?
It depends on the condition. For heavy periods, about 1 in 8 women have a hysterectomy within five years of ablation, and more if they are younger.[5][6] For fibroids, repeat procedures were less common after myomectomy than after embolization in randomized trials.[7][8] A hysterectomy is the only option with no chance of the same problem returning in the uterus.
Can I get pregnant after an alternative treatment?
After a hormonal IUD is removed, or after tablets, yes. After a myomectomy, pregnancy is possible, and your doctor will advise on how long to wait and whether a cesarean is needed. The evidence on pregnancy after embolization, radiofrequency ablation or focused ultrasound is limited, so myomectomy is usually preferred if you want children. Endometrial ablation is not recommended if you want a future pregnancy.[1][7][22]
Does insurance cover the alternatives?
Coverage depends on your plan and the procedure. Before booking, ask your insurer whether the treatment is covered, whether it needs prior authorization and what you will pay in and out of network, especially for newer procedures such as radiofrequency ablation or focused ultrasound.
Is it reasonable to ask for a second opinion?
Yes. Many women see a gynecologist who specializes in fibroids or minimally invasive surgery, or an interventional radiologist for embolization, before deciding. Some alternatives are only offered at larger centers.
Sources
- American College of Obstetricians and Gynecologists. Management of symptomatic uterine leiomyomas. ACOG Practice Bulletin No. 228. Obstetrics & Gynecology. 2021;137(6):e100–e115. pubmed.ncbi.nlm.nih.gov
- National Institute for Health and Care Excellence (NICE). Heavy menstrual bleeding: assessment and management. NICE guideline NG88. 2018, last updated 2026. nice.org.uk
- Bofill Rodriguez M, Lethaby A, Jordan V. Progestogen-releasing intrauterine systems for heavy menstrual bleeding. Cochrane Database of Systematic Reviews. 2020;6(6):CD002126. pubmed.ncbi.nlm.nih.gov
- Bofill Rodriguez M, Lethaby A, Fergusson RJ. Endometrial resection and ablation versus hysterectomy for heavy menstrual bleeding. Cochrane Database of Systematic Reviews. 2021;2(2):CD000329. pubmed.ncbi.nlm.nih.gov
- Oderkerk TJ, Beelen P, Bukkems ALA, et al. Risk of hysterectomy after endometrial ablation: a systematic review and meta-analysis. Obstetrics & Gynecology. 2023;142(1):51–60. pubmed.ncbi.nlm.nih.gov
- Longinotti MK, Jacobson GF, Hung YY, Learman LA. Probability of hysterectomy after endometrial ablation. Obstetrics & Gynecology. 2008;112(6):1214–1220. pubmed.ncbi.nlm.nih.gov
- Gupta JK, Sinha A, Lumsden MA, Hickey M. Uterine artery embolization for symptomatic uterine fibroids. Cochrane Database of Systematic Reviews. 2014;(12):CD005073. pubmed.ncbi.nlm.nih.gov
- Manyonda I, Belli AM, Lumsden MA, et al. Uterine-artery embolization or myomectomy for uterine fibroids (FEMME trial). New England Journal of Medicine. 2020;383(5):440–451. nejm.org
- Bradley LD, Pasic RP, Miller LE. Clinical performance of radiofrequency ablation for treatment of uterine fibroids: systematic review and meta-analysis of prospective studies. Journal of Laparoendoscopic & Advanced Surgical Techniques. 2019;29(12):1507–1517. pubmed.ncbi.nlm.nih.gov
- Pfizer. Myovant Sciences and Pfizer receive FDA approval for MYFEMBREE, the first once-daily treatment for heavy menstrual bleeding associated with uterine fibroids. Press release, May 2021. pfizer.com
- Contemporary OB/GYN. FDA approves Myfembree for endometriosis pain. August 2022. contemporaryobgyn.net
- NHS. Fibroids: treatment. nhs.uk
- NHS. Adenomyosis. nhs.uk
- Becker CM, Bokor A, Heikinheimo O, et al.; ESHRE Endometriosis Guideline Group. ESHRE guideline: endometriosis. Human Reproduction Open. 2022;2022(2):hoac009. pmc.ncbi.nlm.nih.gov
- Shakiba K, Bena JF, McGill KM, Minger J, Falcone T. Surgical treatment of endometriosis: a 7-year follow-up on the requirement for further surgery. Obstetrics & Gynecology. 2008;111(6):1285–1292. pubmed.ncbi.nlm.nih.gov
- NHS. Pelvic organ prolapse. nhs.uk
- Hagen S, Stark D, Glazener C, et al. Individualised pelvic floor muscle training in women with pelvic organ prolapse (POPPY): a multicentre randomised controlled trial. The Lancet. 2014;383(9919):796–806. pubmed.ncbi.nlm.nih.gov
- van der Vaart LR, Vollebregt A, Milani AL, et al. Effect of pessary vs surgery on patient-reported improvement in patients with symptomatic pelvic organ prolapse: a randomized clinical trial. JAMA. 2022;328(23):2312–2323. pubmed.ncbi.nlm.nih.gov
- Ruffolo AF, Salvatore S, Torella M, et al. The uterus debate in vaginal native tissue repair for pelvic organ prolapse: hysteropexy versus hysterectomy. A systematic review and meta-analysis. Maturitas. 2025;203:108755. pubmed.ncbi.nlm.nih.gov
- American College of Obstetricians and Gynecologists. Management of endometrial intraepithelial neoplasia or atypical endometrial hyperplasia: ACOG Clinical Consensus No. 5. Obstetrics & Gynecology. 2023;142(3):735–744. pubmed.ncbi.nlm.nih.gov
- Hillis SD, Marchbanks PA, Peterson HB. The effectiveness of hysterectomy for chronic pelvic pain. Obstetrics & Gynecology. 1995;86(6):941–945. pubmed.ncbi.nlm.nih.gov
- American College of Obstetricians and Gynecologists. Endometrial ablation. Patient FAQ. acog.org
This article is for general information and is not a substitute for medical advice. The right alternative depends on your symptoms, your plans for pregnancy and the findings of your own tests, so always discuss your options with your gynecologist, and contact your doctor or emergency services if you are worried about any symptom.



