Tubal Ligation vs Hysterectomy: Key Differences, Risks and Recovery
Tubal ligation and hysterectomy are often mentioned in the same breath because both end the chance of pregnancy. They are very different operations, though. Tubal sterilization is a short procedure on the fallopian tubes, done mainly for birth control. A hysterectomy removes the uterus and is done to treat a medical problem such as fibroids, heavy bleeding, endometriosis or cancer. This guide compares the two: what each one involves, how well they prevent pregnancy, their risks and recovery, what they mean for your periods, hormones and ovarian cancer risk, and the questions worth asking before you decide.
The short answer
- If your only goal is permanent birth control, tubal sterilization (or your partner’s vasectomy) is the usual choice. A hysterectomy is a much bigger operation and is not normally offered just to prevent pregnancy.
- If you also have a gynecological problem that a hysterectomy would treat, such as large fibroids or heavy bleeding that other treatments have not helped, a hysterectomy deals with both issues at once. Your fallopian tubes can be removed at the same time.
- Neither procedure is meant to be reversed. Both should only be chosen if you are sure you do not want a pregnancy in the future.
What is tubal sterilization?
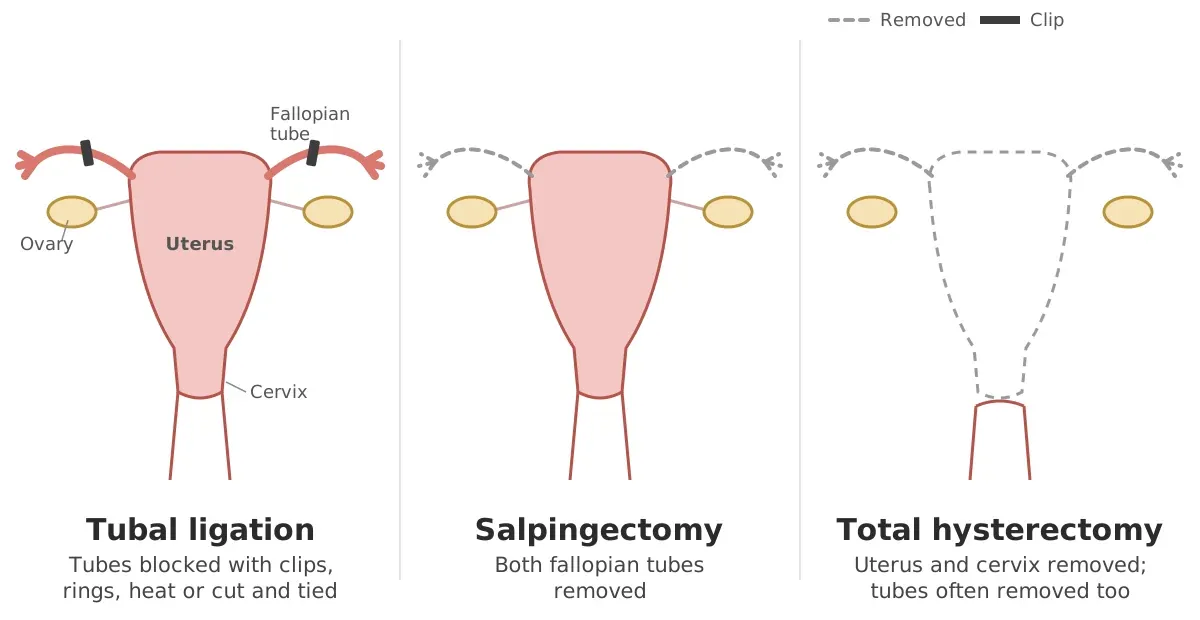
The fallopian tubes carry eggs from the ovaries to the uterus, and they are where sperm usually meets the egg. Tubal sterilization closes or removes the tubes so that sperm and egg cannot meet. The ovaries keep working and still release an egg each month, which is simply absorbed by the body [13]. The uterus stays in place, so periods continue.
There are two main ways to do it:
- Tubal ligation or occlusion (“getting your tubes tied”): the tubes are blocked with clips or rings, sealed with heat (coagulation), or tied and cut with a small piece removed [13].
- Bilateral salpingectomy: both tubes are removed completely. This has become more common because it may also lower the risk of the most common type of ovarian cancer (see below) [7].
Most procedures are done by laparoscopy (keyhole surgery) through one or two small cuts in the abdomen, usually under general anesthetic, and you normally go home the same day [13]. Sterilization can also be done during a cesarean section or shortly after giving birth. A device placed in the tubes through the vagina (Essure) was once an option but has not been sold in the US since the end of 2018 [14].
What is a hysterectomy?
A hysterectomy removes the uterus. In a total hysterectomy the cervix is removed too; in a partial (supracervical) hysterectomy the cervix is left in place. The ovaries and tubes are separate decisions: they can be kept or removed. Our comparison of partial vs total hysterectomy explains these options in more detail.
A hysterectomy is done to treat a condition, not mainly as contraception. Common reasons include fibroids, heavy menstrual bleeding, adenomyosis, endometriosis, prolapse and some cancers or precancers. See our guide to the signs and reasons you might need a hysterectomy. Ending fertility is a consequence of the operation, not its purpose. If you are thinking about a hysterectomy without a medical problem, our article on hysterectomy without a medical reason covers what doctors weigh up.
Side-by-side comparison
| Tubal ligation | Salpingectomy | Hysterectomy | |
|---|---|---|---|
| Main purpose | Permanent birth control | Permanent birth control; may lower ovarian cancer risk | Treating a gynecological condition |
| What is changed | Tubes blocked or cut | Tubes removed | Uterus removed (cervix too in a total hysterectomy) |
| Usual approach | Laparoscopy, or at cesarean birth | Laparoscopy, or at cesarean birth | Laparoscopic, vaginal, robotic or abdominal |
| Hospital stay | Usually home the same day | Usually home the same day | Same day to a few days |
| Recovery | About a week of taking it easy | About a week of taking it easy | Several weeks |
| Periods | Continue | Continue | Stop |
| Hormones | No change | No change | No direct change if ovaries are kept |
| Chance of pregnancy afterwards | Low, but not zero | Lower than tubal ligation | None |
| Reversible? | Not intended; reversal sometimes possible | No | No |
How well do they prevent pregnancy?
After a hysterectomy, pregnancy is not possible because there is no uterus for an embryo to grow in. If you are curious about the anatomy, see where sperm goes after a hysterectomy.
Tubal sterilization is very effective, but it is not perfect. The tubes can occasionally reconnect, immediately or years later [13]:
- UK family planning information gives a lifetime failure rate of about 1 in 200 [13].
- The largest US study, the Collaborative Review of Sterilization (CREST), followed more than 10,000 women. About 18 in 1,000 became pregnant within 10 years. The rate depended on the method used and was higher in women sterilized at a younger age [2].
- When the tubes are removed completely, there is nothing left to reconnect.
For comparison, a vasectomy fails in about 1 in 2,000 cases [13], and US guidelines describe it as safer, more effective and less expensive than female sterilization [1]. Hormonal IUDs and the contraceptive implant are at least as effective as tubal sterilization, have fewer risks and can be removed if you change your mind [1]. Our article on the Mirena IUD vs hysterectomy explains how a hormonal IUD can also lighten heavy periods.
Ectopic pregnancy after sterilization
Sterilized women are less likely to have an ectopic pregnancy than women using no contraception, because pregnancies of any kind are rare [1]. But when a pregnancy does happen after tubal sterilization, it is much more likely to be in the tube. In CREST, about one in three pregnancies after sterilization was ectopic [3]. An ectopic pregnancy can be life-threatening if the tube ruptures.
After tubal sterilization, get medical advice straight away if you have: a positive pregnancy test, a missed or unusually light period, unusual vaginal bleeding, or sudden or one-sided pain in the lower abdomen [13]. Go to an emergency department if you have severe abdominal pain, shoulder-tip pain, or feel faint.
Risks and recovery
Tubal sterilization
Laparoscopic sterilization is a safe procedure and serious complications are uncommon [1][13]. Possible risks include reactions to the anesthetic, bleeding, infection and, rarely, injury to the bowel, bladder or a blood vessel. Most people feel sore and tired for a few days and are advised to take it easy for about a week [13]. Some shoulder or abdominal discomfort from the gas used during laparoscopy is common and settles within a few days.
Hysterectomy
A hysterectomy is major surgery. Complications are uncommon, but the list is longer: heavy bleeding that may need a transfusion, infection, blood clots, and rare damage to the bladder, bowel or ureters (the tubes that carry urine from the kidneys) [11]. Recovery usually takes several weeks, and longer after an abdominal operation than after laparoscopic or vaginal surgery. Our week-by-week recovery guide explains what to expect, and our guide to hysterectomy scars shows how the incisions differ.
Because of these differences in risk and recovery, a hysterectomy is generally not recommended when the only goal is to prevent pregnancy.

Periods, hormones and menopause
After tubal sterilization, your ovaries and uterus keep working as before, so you still ovulate and have periods, and your hormones and sex drive are not affected [13]. Some women notice heavier or more painful periods afterwards. This is often because they have stopped hormonal contraception, which had been making their periods lighter [13].
You may come across the term “post-tubal ligation syndrome”, a claimed set of symptoms such as heavy periods and hormone changes caused by the procedure. It is not a recognized diagnosis. A CREST study that followed more than 9,000 sterilized women for up to 14 years and compared them with women whose partners had a vasectomy concluded that tubal sterilization does not cause a “post-tubal ligation syndrome” [5].
After a hysterectomy, periods stop. If your ovaries are kept, they continue to make hormones and you will not go into menopause straight away. However, menopause may arrive somewhat earlier than it otherwise would [11]. In one New Zealand study, 20.6% of women who had a hysterectomy reached menopause within five years, compared with 7.3% of similar women who did not have surgery [12]. If both ovaries are removed, menopause starts immediately. Read more in our article on menopause after hysterectomy with ovaries intact.
Effect on ovarian cancer risk
Many of the most common and most serious ovarian cancers (high-grade serous cancers) are now thought to begin in the fallopian tubes rather than in the ovary itself. That has changed how surgeons think about the tubes:
- In a Swedish national study, women who had a tubal sterilization had about a 28% lower risk of ovarian cancer than women without these operations. The figure was about 21% lower after hysterectomy, and about 65% lower after removal of both tubes [8].
- Studies from British Columbia and Ontario in Canada, where surgeons routinely offer to remove the tubes during a hysterectomy or instead of tying them, have found fewer ovarian cancers in women who had their tubes removed than in women who had a hysterectomy alone or a tubal ligation [9][10]. Follow-up is still relatively short and most women in these studies have not yet reached the age when ovarian cancer is most common, so the exact size of the benefit is still being worked out.
- The American College of Obstetricians and Gynecologists (ACOG) advises surgeons to discuss removing the tubes (opportunistic salpingectomy) with patients having a hysterectomy or a sterilization procedure [7]. Removing the tubes does not appear to affect how the ovaries work [7].
These are observational studies, so they show an association rather than proof, and ovarian cancer is uncommon to begin with. If you have a strong family history of ovarian or breast cancer, or a known BRCA gene change, the advice is different and may include removing the ovaries; talk to your doctor or a genetics service.
Regret and reversal
Most women who choose sterilization are happy with the decision, but age matters. In CREST, the chance of regretting sterilization within 14 years was about 20% for women sterilized at age 30 or younger, compared with about 6% for women sterilized after 30 [4]. This does not mean younger women should be refused: US guidelines state that a well-informed woman should not be turned away because of her age or the number of children she has [1]. It does mean the decision deserves time, and that long-acting reversible methods are worth considering if you are unsure.
Tubal ligation can sometimes be reversed with another operation, but success is not guaranteed and depends on your age, the method used and how much healthy tube is left. In the UK it is rarely available on the NHS and can be difficult and expensive to get privately [13]. After a salpingectomy there is nothing to reconnect, so IVF is the only route to pregnancy. After a hysterectomy, carrying a pregnancy is not possible; some women with their ovaries still in place have children through IVF and a gestational surrogate. See IVF after hysterectomy.
Does tubal ligation lead to a hysterectomy later?
Women who have had a tubal sterilization are more likely to have a hysterectomy in later years. In CREST, sterilized women were roughly four times as likely as women whose partners had a vasectomy to have a hysterectomy within five years, whatever their age at sterilization [6].
This does not show that the sterilization damaged the uterus. Since tubal sterilization does not appear to cause menstrual problems [5], other explanations are likely: for example, a woman who no longer needs to protect her fertility may be more willing to choose surgery for heavy periods or fibroids. If you are considering sterilization and already have troublesome periods, it is worth discussing whether another option would treat both, such as a hormonal IUD.
If you are having a hysterectomy anyway
If you already need a hysterectomy, you don’t need a separate sterilization procedure: the hysterectomy itself prevents pregnancy. The question to ask is whether your surgeon plans to remove your fallopian tubes at the same time, because that may lower your future ovarian cancer risk without affecting your ovaries’ hormones [7]. Surgeons generally won’t change the type of operation just to remove the tubes; for example, a vaginal hysterectomy should not be switched to a laparoscopic one only for this reason.
If your problem is fibroids and you might still want children, a hysterectomy is not the only choice; see myomectomy vs hysterectomy.
Questions to ask your doctor
- Which method of sterilization do you recommend for me: tubal ligation or salpingectomy? Why?
- Would a hormonal IUD, an implant or my partner’s vasectomy suit me just as well?
- Do I have a medical problem, such as fibroids or heavy bleeding, that should be treated at the same time?
- If I need a hysterectomy, will you remove my fallopian tubes? What about my ovaries?
- How long will recovery take, and when can I go back to work?
- How long should I keep using contraception after the procedure?
Key points
- Tubal sterilization is a short procedure for permanent birth control; a hysterectomy is major surgery to treat a medical condition.
- Tubal sterilization fails in roughly 1 in 200 women over a lifetime, and a pregnancy after it has a high chance of being ectopic.
- Tubal sterilization does not change your hormones or cause a “post-tubal ligation syndrome”; a hysterectomy ends periods and may bring menopause somewhat earlier even if the ovaries are kept.
- Removing the fallopian tubes, whether instead of tying them or during a hysterectomy, is linked to a lower risk of ovarian cancer.
- Both procedures are meant to be permanent. Women sterilized at 30 or younger are more likely to regret it later.
Sources
- American College of Obstetricians and Gynecologists. Benefits and Risks of Sterilization (Practice Bulletin No. 208, 2019), summary on Guideline Central.
- Peterson HB, et al. The risk of pregnancy after tubal sterilization: findings from the U.S. Collaborative Review of Sterilization. American Journal of Obstetrics and Gynecology, 1996.
- Peterson HB, et al. The risk of ectopic pregnancy after tubal sterilization. New England Journal of Medicine, 1997. Summary in the Embryo Project Encyclopedia.
- Hillis SD, et al. Poststerilization regret: findings from the United States Collaborative Review of Sterilization. Obstetrics and Gynecology, 1999.
- Peterson HB, et al. The risk of menstrual abnormalities after tubal sterilization. New England Journal of Medicine, 2000. Summary in American Family Physician.
- U.S. Collaborative Review of Sterilization Working Group. Higher hysterectomy risk for sterilized than nonsterilized women: findings from the U.S. Collaborative Review of Sterilization. Obstetrics and Gynecology, 1998.
- American College of Obstetricians and Gynecologists. Committee Opinion No. 774: Opportunistic Salpingectomy as a Strategy for Epithelial Ovarian Cancer Prevention. Obstetrics and Gynecology, 2019.
- Falconer H, et al. Ovarian cancer risk after salpingectomy: a nationwide population-based study. Journal of the National Cancer Institute, 2015.
- Sowamber R, et al. Serous Ovarian Cancer Following Opportunistic Bilateral Salpingectomy. JAMA Network Open, 2026.
- Bahrami F, et al. Effectiveness of opportunistic bilateral salpingectomy in preventing epithelial ovarian cancer: a population-based study. Journal of the National Cancer Institute, 2026.
- NHS. Hysterectomy: Complications.
- Farquhar CM, et al. The association of hysterectomy and menopause: a prospective cohort study. BJOG, 2005.
- FPA. Your guide to male and female sterilisation. Patient booklet, 2014.
- MDedge. Essure sales to halt in U.S. by end of 2018. News report, 2018.
This article is for general information and is not a substitute for medical advice. Please talk to your doctor or gynecologist about your own situation, and seek urgent care if you have severe abdominal pain, heavy bleeding or a positive pregnancy test after tubal sterilization.