Myomectomy vs Hysterectomy for Fibroids: Differences, Recovery and How to Choose
If fibroids are causing heavy periods, pain or pressure and medicines have not helped enough, the two operations you are most likely to hear about are a myomectomy and a hysterectomy. A myomectomy removes the fibroids and keeps the uterus. A hysterectomy removes the uterus, and the fibroids with it. Neither is “better” for everyone. The right choice depends on whether you may want a pregnancy, how many fibroids you have and where they sit, how you feel about fibroids coming back, and how much recovery time you can manage. This guide compares the two side by side and explains the options in between.
Fibroids in brief
Fibroids (doctors call them leiomyomas or myomas) are non-cancerous growths of the muscle of the uterus. They are very common: in a US study that screened women with ultrasound, more than 80% of Black women and nearly 70% of white women had developed fibroids by age 50.[3] Many never cause symptoms and need no treatment. When they do, the usual problems are heavy or long periods, pelvic pain or pressure, needing to pee often, back pain and pain during sex.[2] Fibroids depend on hormones and usually shrink after menopause.[2]
Where a fibroid grows matters a great deal when choosing a treatment, because it decides how a surgeon can reach it.
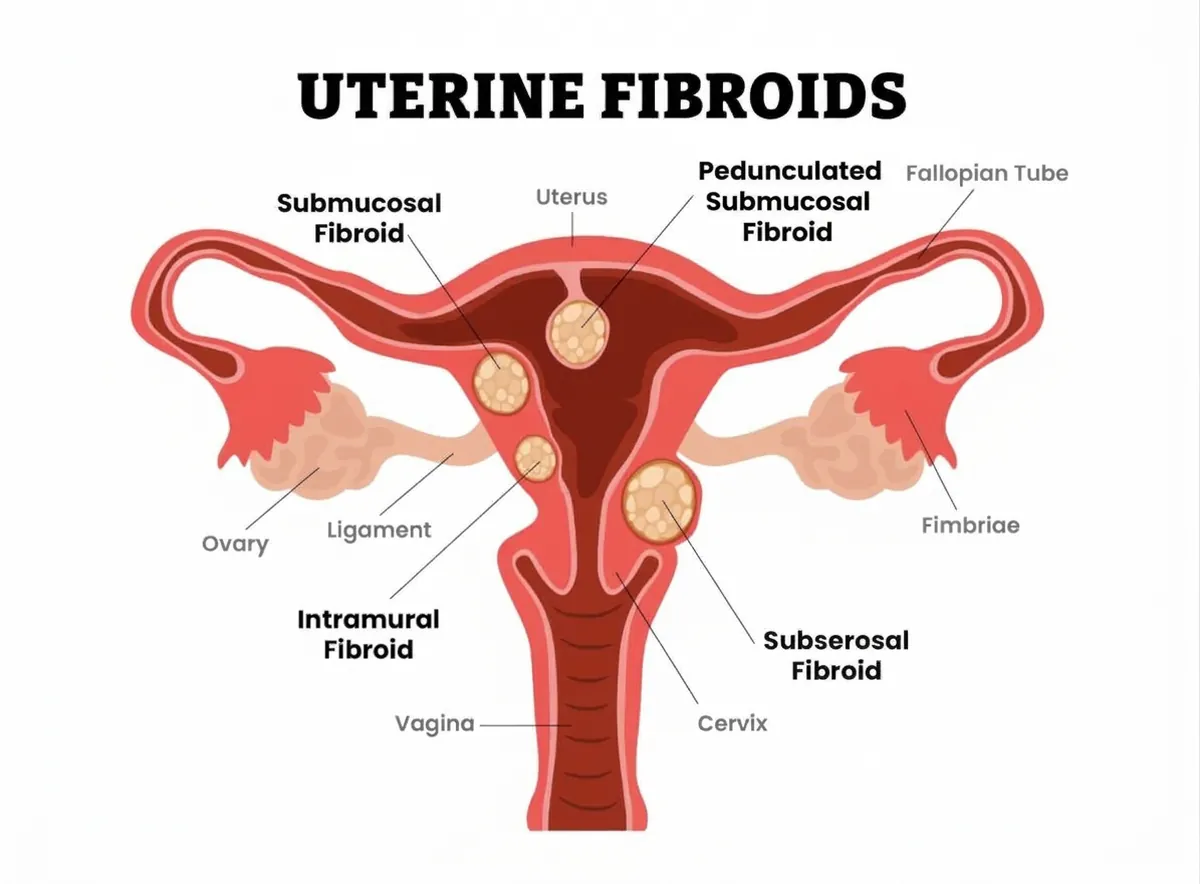
- Submucosal fibroids bulge into the cavity of the uterus. They are the type most linked to heavy bleeding and to trouble getting or staying pregnant, and they can often be removed from inside, through the vagina.[2][5]
- Intramural fibroids grow within the muscle wall. Deep or large ones are harder to remove without a bigger repair of the wall.
- Subserosal fibroids grow on the outer surface and tend to cause pressure on the bladder or bowel rather than heavy bleeding.
- Pedunculated fibroids hang on a stalk, either inside the cavity or on the outside.[2]
What a myomectomy involves
A myomectomy removes the fibroids and repairs the uterus so that it can still carry a pregnancy. The American College of Obstetricians and Gynecologists (ACOG) recommends it as a surgical option for women with symptomatic fibroids who want to keep their uterus.[1] There are three main ways to do it, and the method depends on the size, number and position of the fibroids:[5]
- Hysteroscopic myomectomy: a thin camera is passed through the vagina and cervix into the uterus, and fibroids inside the cavity are shaved away. There are no cuts on the tummy, and recovery takes from a few days to two weeks.[5]
- Laparoscopic (keyhole) or robotic myomectomy: the fibroids are removed through small cuts in the abdomen. Recovery usually takes one to two weeks.[5]
- Abdominal myomectomy (laparotomy): one larger cut, often low and horizontal, used when fibroids are large, numerous or deep. Recovery takes about four to six weeks.[5]
Myomectomy reduces bleeding and pelvic pain from fibroids, and it is the only fibroid treatment that may improve the chance of pregnancy, mainly when a submucosal fibroid is distorting the cavity.[5] Its risks include bleeding, infection, injury to the bladder or bowel, and scar tissue (adhesions) that can occasionally affect fertility. Rarely, bleeding cannot be controlled and the surgeon has to remove the uterus, so you will be asked to consent to an unplanned hysterectomy before the operation.[5]
What a hysterectomy for fibroids involves
Hysterectomy is the most common operation for fibroids in the United States,[1] and it is the only treatment that removes fibroids for good, because there is no uterus left for new ones to grow in.[2] Periods stop, and pregnancy is no longer possible.
A hysterectomy for fibroids does not have to be major open surgery, and it does not automatically mean menopause:
- Approach: depending on the size of the uterus, it can be done through the vagina, by laparoscopy or robotic surgery, or through an abdominal cut when the uterus is very large.
- Cervix: some women have a partial (supracervical) hysterectomy that keeps the cervix; others have a total hysterectomy. Our comparison of partial vs total hysterectomy explains the trade-offs.
- Ovaries: fibroids are a problem of the uterus, not the ovaries, so healthy ovaries are often left in place. If they are removed before menopause, menopause starts straight away; see our guide to menopause after a total hysterectomy.
Recovery is usually a few weeks after a vaginal or keyhole hysterectomy and around six weeks or more after an abdominal one. Our week-by-week recovery guide describes what to expect.
Myomectomy vs hysterectomy at a glance
| Myomectomy | Hysterectomy | |
|---|---|---|
| What is removed | The fibroids only | The uterus (with or without the cervix); ovaries are a separate decision |
| Pregnancy afterwards | Possible; a planned caesarean may be advised | Not possible |
| Periods | Continue, usually lighter | Stop |
| Can fibroids come back? | Yes, new fibroids are common over the years | No |
| Typical recovery | Days to 2 weeks (hysteroscopic or keyhole); 4 to 6 weeks (open) | A few weeks (vaginal or keyhole); about 6 weeks or more (open) |
| Main surgical risks | Bleeding, infection, adhesions, rarely an unplanned hysterectomy | Bleeding, infection, injury to bladder or bowel |
How to choose: the questions that matter
Do you want to keep the option of pregnancy?
This is usually the deciding question. If you might want to carry a pregnancy, a myomectomy (or a non-surgical option) is the route to discuss, because a hysterectomy ends that possibility. If you are sure your family is complete, both operations are reasonable and the other questions below carry more weight. Some women who are unsure about future children also value keeping the uterus for its own sake, and that is a valid reason too.
How do you feel about fibroids coming back?
A fibroid that has been completely removed does not regrow, but new ones can develop from the remaining muscle. In a study of 512 women followed after laparoscopic myomectomy, new fibroids were found on ultrasound in about 1 in 9 women after one year, about half after five years and most women after eight years. Far fewer needed another operation: about 7% by five years.[7] The more and the larger the fibroids, and the larger the uterus, the more likely they are to return.[5][7] If you are close to menopause, when fibroids naturally shrink, recurrence matters less.
How many fibroids, and where?
One or two fibroids, or a fibroid inside the cavity, can usually be removed with a quick recovery. Many large or deep fibroids may only be removable through an open operation with a longer recovery, and leave more chance of new ones. In that situation some women who do not want more children prefer a hysterectomy so that they only have one operation.
Is one operation riskier than the other?
It is often assumed that myomectomy is the riskier operation because it can bleed a lot. A 2013 systematic review of six studies with 1,520 women compared open myomectomy with open hysterectomy for a uterus up to about the size of a 16 to 18 week pregnancy. It found no difference in the rate of serious complications; hysterectomy was linked to more injury to nearby organs and longer hospital stays.[8] The studies were observational and of mixed quality, so the honest summary is that, for most women, the risks are broadly similar, and your surgeon’s experience with each operation matters.
Could there be something other than a fibroid?
Rarely, a growth that looks like a fibroid is a cancer called a uterine sarcoma. The US Food and Drug Administration (FDA) estimates that this is found in about 1 in 225 to 1 in 580 women having surgery for presumed fibroids. Because of this risk, the FDA recommends that if fibroid tissue is cut up inside the body to remove it through small cuts (power morcellation), it should only be done inside a containment bag, and that this technique should not be used in women with suspected cancer or in women over 50 having fibroid surgery.[10] Rapid growth of a fibroid after menopause or new bleeding after menopause should always be checked.
Pregnancy after a myomectomy
Many women go on to have healthy pregnancies after a myomectomy. The main concern is that the scar in the wall of the uterus could tear (uterine rupture) during pregnancy or labor. This is uncommon: a 2016 systematic review of 23 studies found rupture in about 0.6% of pregnancies after a myomectomy, and most of these happened before labor had started.[9] Whether you are offered a planned caesarean depends on how deep and how large the repair was; your surgeon’s operation notes are important for whoever looks after a future pregnancy.[5] Ask your surgeon how long to wait before trying to conceive, as advice varies with the type of operation.
Options to consider before surgery
Neither operation is the only answer. Fibroids that cause no symptoms can simply be watched, and several treatments can be tried first or instead.[1][4] Our article on minimally invasive alternatives for fibroids covers them in more depth.
- Medicines for heavy bleeding: anti-inflammatory painkillers, tranexamic acid, the combined pill or a hormonal IUD can ease bleeding, although they do not remove fibroids.[2][4]
- Hormone-lowering medicines: GnRH medicines shrink fibroids for a while, but they cause menopause-like symptoms, are usually limited to short courses, and fibroids tend to regrow when they stop.[2] A newer once-daily tablet that combines relugolix with low-dose hormones was approved by the FDA in 2021 for heavy bleeding from fibroids, for up to 24 months because of the risk of bone loss.[11]
- Uterine artery embolization (UAE): a radiologist blocks the blood supply to the fibroids through a small tube in the groin or wrist, and they shrink.[4] In the UK FEMME trial, which randomly assigned 254 women who wanted to avoid a hysterectomy, myomectomy gave a modestly better quality of life two years later, and fewer women needed another fibroid procedure (7% after myomectomy vs 16% after UAE), but UAE meant a shorter hospital stay (2 vs 4 days).[6]
- Endometrial ablation: destroys the lining of the uterus to reduce heavy bleeding. It is only suitable if you do not want a future pregnancy.[2][4]
- Other procedures: radiofrequency ablation and focused ultrasound can destroy fibroids without removing them, but they are not suitable for every fibroid and are not available everywhere.[1][2]
Questions to ask your surgeon
- How many fibroids do I have, how big are they and where are they?
- Could my fibroids be removed through the vagina or by keyhole surgery, or would I need an open operation?
- How likely am I to need another treatment within five years with each option?
- How many myomectomies and hysterectomies like mine do you do each year?
- If I have a hysterectomy, will you keep my cervix and my ovaries?
- If I have a myomectomy, will I need a caesarean in a future pregnancy, and how long should I wait before trying?
- Will any tissue be morcellated, and if so, will a containment bag be used?
- What would happen if I waited or tried medicine or UAE first?
Our checklist on how to prepare for a hysterectomy includes more questions for your pre-operative appointment, and our guide to the reasons for a hysterectomy puts fibroids in context with other conditions.
When to seek urgent care
Whatever you decide, contact a doctor straight away or go to an emergency department if you have:
- Very heavy bleeding, such as soaking through a pad every hour for several hours, or passing large clots.
- Feeling faint, dizzy or short of breath, which can be a sign of serious blood loss or anaemia.
- Sudden, severe pelvic or abdominal pain.
- After surgery: fever, worsening pain, a red, hot or leaking wound, or foul-smelling discharge.
- During a pregnancy after a myomectomy: severe or constant abdominal pain, bleeding, or reduced movements of the baby.
Frequently asked questions
Is a myomectomy easier to recover from than a hysterectomy?
It depends more on how the operation is done than on which one it is. A hysteroscopic myomectomy usually means a few days off, a keyhole myomectomy one to two weeks, and an open myomectomy four to six weeks,[5] which is similar to an open hysterectomy.
Will a hysterectomy for fibroids put me into menopause?
Not if your ovaries are kept. Your periods will stop, but your ovaries will keep making hormones until your natural menopause. Menopause starts straight away only if both ovaries are removed.
Can I get pregnant after a hysterectomy?
No. Without a uterus a pregnancy cannot be carried. If your ovaries are kept, your own eggs could still be used through IVF with a gestational carrier; see our articles on IVF after a hysterectomy and surrogacy.
Can I have a myomectomy if I do not want children?
Yes. Myomectomy is an option for anyone who wants to keep the uterus, whatever the reason.[1] It is worth weighing the chance of needing another treatment later, especially if you have many fibroids and menopause is still years away.
Sources
- American College of Obstetricians and Gynecologists. Management of symptomatic uterine leiomyomas. Practice Bulletin No. 228. Obstetrics & Gynecology. 2021;137:e100–e115. acog.org
- US Department of Health and Human Services, Office on Women’s Health. Uterine fibroids. womenshealth.gov
- Baird DD, et al. High cumulative incidence of uterine leiomyoma in black and white women: ultrasound evidence. American Journal of Obstetrics and Gynecology. 2003;188(1):100–107. pubmed.ncbi.nlm.nih.gov
- NHS. Fibroids: treatment. nhs.uk
- Healthwise. Myomectomy. HealthLink BC. healthlinkbc.ca
- Manyonda I, et al. Uterine-artery embolization or myomectomy for uterine fibroids (FEMME trial). New England Journal of Medicine. 2020;383(5):440–451. nejm.org
- Predictors of leiomyoma recurrence after laparoscopic myomectomy. Journal of Minimally Invasive Gynecology. 2007. pubmed.ncbi.nlm.nih.gov
- Pundir J, Walawalkar R, Seshadri S, Khalaf Y, El-Toukhy T. Perioperative morbidity associated with abdominal myomectomy compared with total abdominal hysterectomy for uterine fibroids. Journal of Obstetrics and Gynaecology. 2013. pubmed.ncbi.nlm.nih.gov
- Gambacorti-Passerini, Gimovsky, Locatelli, Berghella. Trial of labor after myomectomy and uterine rupture: a systematic review. Acta Obstetricia et Gynecologica Scandinavica. 2016;95(7):724–734. pubmed.ncbi.nlm.nih.gov
- US Food and Drug Administration. Power morcellation during gynecologic laparoscopic surgeries. fda.gov
- Pfizer. Myovant Sciences and Pfizer receive FDA approval for MYFEMBREE, the first once-daily treatment for heavy menstrual bleeding associated with uterine fibroids. Press release, May 2021. pfizer.com
This article is for general information and is not a substitute for medical advice. Always discuss your own situation with your gynecologist or surgeon, and contact them or emergency services if you are worried about any symptom.