Hysterectomy for Cervical Cancer: When It’s Needed, Radical vs Simple, and Recovery
Hysterectomy is one of the main treatments for early cervical cancer, but it is not the only one, and it is not always the best one. Whether surgery is offered, and which kind, depends mostly on the stage of the cancer: how big the tumor is and whether it has spread. For some small tumors a simple hysterectomy is enough. Others need a radical hysterectomy, a larger operation that also removes the tissue around the cervix. And once the cancer has grown beyond a certain size, chemotherapy combined with radiation usually works better than surgery.
This guide explains what cervical cancer is, how it is found and staged, when a hysterectomy is recommended, how a radical hysterectomy differs from a simple one, why open surgery is usually preferred for the radical operation, the options that preserve fertility, and what recovery and life afterwards look like. If you are reading because of an abnormal smear rather than a cancer diagnosis, our guide to LEEP for cervical dysplasia is a better place to start: precancerous changes are treated very differently.
What is cervical cancer?
The cervix is the narrow lower part of the uterus that opens into the vagina. Cervical cancer starts when cells on the surface of the cervix change and begin to grow out of control. Almost all cases are caused by a long-lasting infection with a high-risk type of human papillomavirus (HPV), a very common virus passed on through sexual contact. Most HPV infections clear by themselves; the problem is the small number that persist for years.[1]
The change from abnormal cells to cancer is usually slow. The World Health Organization estimates it typically takes 15 to 20 years, although it can be faster (5 to 10 years) in people with a weakened immune system, such as untreated HIV.[1] That long window is why screening works so well: precancerous changes can be found and removed long before they become cancer.
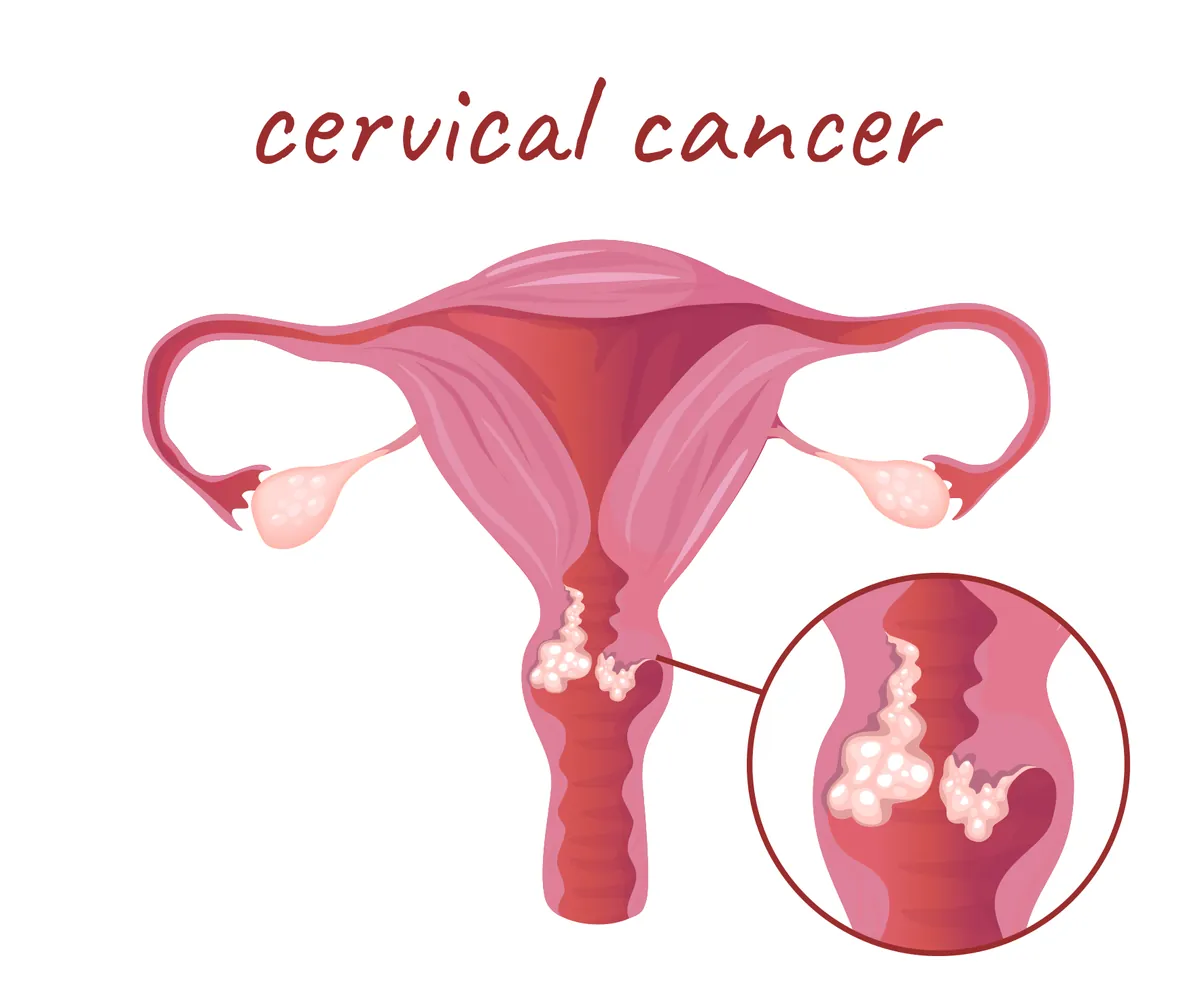
The two main types are squamous cell carcinoma, which starts in the flat cells covering the outer cervix and is the most common, and adenocarcinoma, which starts in the glandular cells lining the cervical canal. Both are treated in broadly the same way, stage by stage.
How common is it?
The American Cancer Society estimates that about 13,490 new cases of invasive cervical cancer will be diagnosed in the United States in 2026, and about 4,200 women will die from it. It is most often found between the ages of 35 and 64, with an average age at diagnosis of 50, and it is rare before 20.[2] Worldwide it is far more common: around 604,000 new cases and 280,000 deaths in 2024, most of them in countries without organized screening and vaccination.[1]
Risk factors
- Persistent high-risk HPV infection, by far the most important factor.[1]
- Not being screened, or long gaps between screening tests.
- A weakened immune system: women living with HIV are about six times more likely to develop cervical cancer.[1]
- Smoking.
Symptoms and diagnosis
Early cervical cancer often causes no symptoms at all, which is why it is usually found through screening. When symptoms do appear, the NHS lists:[3]
- Vaginal bleeding that is unusual for you: during or after sex, between periods, after menopause, or periods heavier than usual
- Changes in vaginal discharge
- Pain during sex
- Pain in the lower back, the pelvis or the lower tummy
These symptoms have many possible causes, and most of them are not cancer. They are still worth getting checked, because cancer found early is much easier to treat.[3] Bleeding after menopause should always be reported to a doctor.
Diagnosis usually follows a step-by-step path. An abnormal screening result (an HPV test, a Pap test or both) leads to a colposcopy, a close look at the cervix with a magnifying instrument. Any suspicious area is sampled with a biopsy. If the biopsy shows cancer, a cone biopsy or LEEP may be done to measure exactly how deep it goes, and imaging such as MRI, CT or PET scans shows whether it has spread.
Stages of cervical cancer, and why they decide treatment
Stage is the single most important factor in choosing treatment.[4] Most doctors use the system of the International Federation of Gynecology and Obstetrics (FIGO), last revised in 2018. Scans and pathology results can now be used to assign the stage, and cancer in the lymph nodes moves a case to stage III regardless of tumor size.[5] In simplified terms:
| Stage | What it means (simplified) |
|---|---|
| IA | Cancer visible only under the microscope. IA1: less than 3 mm deep. IA2: 3 to less than 5 mm deep. |
| IB | Cancer still confined to the cervix but larger. IB1: under 2 cm. IB2: 2 to under 4 cm. IB3: 4 cm or more.[5] |
| II | Spread beyond the uterus to the upper vagina (IIA) or to the tissue beside the cervix, called the parametrium (IIB), but not to the pelvic wall. |
| III | Spread to the lower vagina or the pelvic wall, blocking a kidney, or to the lymph nodes in the pelvis (IIIC1) or along the aorta (IIIC2).[5] |
| IV | Spread to the bladder or rectum (IVA) or to distant organs (IVB). |
As a rule of thumb, surgery is the main treatment for stages IA, IB1, IB2 and IIA1, while larger or more advanced cancers are usually treated with chemoradiation. The next sections explain why.
When is a hysterectomy recommended for cervical cancer?
Based on the American Cancer Society’s summary of current treatment guidelines, the usual options by stage are:[4]
- Stage IA1: a cone biopsy alone may be enough if the edges are clear, especially for women who want to keep their fertility. If fertility is not a concern, a simple hysterectomy is an option. If the cancer has invaded small blood or lymph vessels (lymphovascular invasion), it is treated like stage IA2.
- Stage IA2: a radical hysterectomy with removal of the pelvic lymph nodes, or radiation. Fertility-sparing surgery is possible.
- Stages IB1 and IB2: a radical hysterectomy with pelvic lymph node removal is the standard surgery. For women who want children, a radical trachelectomy may be possible. Women who are not fit for surgery can have radiation instead.
- Stage IIA1: radical hysterectomy with lymph node removal. Chemoradiation is usually added if the cancer has reached the lymph nodes or the parametrium, or if the edges of the removed tissue are not clear.
- Stages IB3 and IIA2: chemoradiation is the most common choice, although a radical hysterectomy is also an option in some centers.
- Stages IIB, III and IVA: chemoradiation (radiation given together with cisplatin or carboplatin), usually followed by internal radiation (brachytherapy). Hysterectomy is not the standard treatment.
- Stage IVB: treatment focuses on chemotherapy, sometimes with immunotherapy, to control the cancer and its symptoms.
Other factors also matter: the type of cancer, exactly where the tumor sits, your age and general health, and whether you want to have children.[4] Your case should be discussed by a team that includes a gynecologic oncologist, a surgeon who specializes in cancers of the female reproductive organs.
Why not just operate on larger tumors?
It can feel counterintuitive that a bigger cancer is less likely to be treated with surgery. The reason is that larger tumors are more likely to have spread into the tissue around the cervix or into the lymph nodes. If surgery finds that, radiation and chemotherapy are usually needed afterwards anyway, and having both major surgery and pelvic radiation adds up the side effects of each. For these cancers, chemoradiation from the start is usually the preferred treatment. In a trial of women who had a radical hysterectomy and were then found to have cancer in the lymph nodes, the parametrium or the surgical margins, adding chemotherapy to radiation raised four-year survival from 71% to 81%.[6]
Simple vs radical hysterectomy
The word “radical” has nothing to do with how drastic the decision is. It describes how much tissue is removed:[7]
| Simple (total) hysterectomy | Radical hysterectomy | |
|---|---|---|
| Uterus and cervix | Removed | Removed |
| Parametrium and ligaments beside the cervix | Left in place | Removed |
| Upper vagina | Left in place | About 1 inch (2 to 3 cm) removed |
| Pelvic lymph nodes | Not part of the operation itself (assessed separately when needed for cancer) | Often removed at the same time |
| Ovaries | Usually kept unless there is another reason | Usually kept unless there is another reason |
| Hospital stay | Shorter | Usually longer |
There is also a modified radical hysterectomy, which removes less of the vagina and surrounding tissue than a full radical operation.[7] Note that a partial (supracervical) hysterectomy, which leaves the cervix in place, is never used to treat cervical cancer: the cervix is where the cancer is.
The SHAPE trial: when a simple hysterectomy may be enough
For decades, a radical hysterectomy was standard for almost all stage IB cancers. A large international trial published in 2024, known as SHAPE, tested whether a simple hysterectomy (with lymph node assessment) was enough for low-risk cancers: tumors of 2 cm or less with limited invasion into the cervix. Among 700 women followed for a median of 4.5 years, the cancer came back in the pelvis within three years in 2.52% after simple hysterectomy and 2.17% after radical hysterectomy, a difference small enough to count as equivalent. The simple operation caused far fewer bladder problems: after the first month, 4.7% had urinary leakage compared with 11.0%, and 0.6% had trouble emptying the bladder compared with 9.9%.[8]
If your tumor is small, it is reasonable to ask whether you fit the low-risk criteria and whether a simple hysterectomy is an option for you.
Open or minimally invasive radical hysterectomy?
For most benign conditions, keyhole surgery (laparoscopic or robotic) is preferred over open surgery because recovery is faster. Radical hysterectomy for cervical cancer is an important exception.
In 2018, the LACC trial compared minimally invasive and open radical hysterectomy in 631 women with early cervical cancer. The trial was stopped early because the keyhole group did worse: 86.0% were alive and free of cancer at four and a half years, compared with 96.5% after open surgery, and overall survival at three years was 93.8% versus 99.0%.[9] A large US study published at the same time found that four-year mortality was 9.1% after minimally invasive radical hysterectomy and 5.3% after open surgery, and that survival nationally began to fall when keyhole surgery became common.[10]
The reasons are still being studied. As a result, an open radical hysterectomy through an abdominal incision is the preferred approach in most cases, although keyhole surgery may still be discussed for a small group of women with very early cancers.[7] If a minimally invasive radical hysterectomy is offered, ask why it is being recommended in your case. These results apply to radical surgery for cervical cancer, not to hysterectomy for fibroids, heavy bleeding or other benign conditions.
Lymph nodes and sentinel node mapping
Because cervical cancer often spreads first to the lymph nodes in the pelvis, they are usually checked during surgery. Traditionally many nodes on both sides are removed (pelvic lymph node dissection). Some centers now use sentinel lymph node mapping: a dye or tracer is injected into the cervix to find the first nodes the cancer would reach, so fewer nodes need to be removed. It may be considered for some stage I cancers and works best for tumors under 2 cm.[7] Removing fewer nodes lowers the risk of lymphedema, explained below.
Fertility-sparing options
For women with early cancer who want to become pregnant, a hysterectomy is not the only path:[4][7]
- Cone biopsy may be enough for some stage IA1 cancers with clear edges, and, combined with lymph node removal, for some stage IA2 cancers.
- Radical trachelectomy removes the cervix, the upper vagina and nearby lymph nodes but keeps the body of the uterus. A permanent stitch is placed to keep the lower opening of the uterus closed. It is an option for some stage IA2, IB1 and IB2 cancers.
After a trachelectomy, some women carry a pregnancy to term and deliver by cesarean section, but the risk of miscarriage may be higher.[7] These operations need careful selection and close follow-up, so they are usually done in specialist centers. If you will need radiation or a hysterectomy instead, ask before treatment about options to preserve fertility. Our guides to IVF after hysterectomy and surrogacy explain the options when the ovaries are kept.
Do the ovaries have to be removed?
Usually not. In both simple and radical hysterectomy for cervical cancer, the ovaries are generally left in place unless there is another medical reason to remove them.[7] Keeping them means you do not go into menopause straight after surgery, which matters a great deal for younger women. If the ovaries are removed, menopause starts immediately; our article on menopause after a total hysterectomy explains what that involves.
Pelvic radiation is different: it can damage the ovaries and cause early menopause even when they are not removed.[11]
Side effects of a radical hysterectomy
All hysterectomies share the general risks of major surgery, such as bleeding, infection and blood clots. A radical hysterectomy has some extra ones because it removes more tissue close to the nerves of the bladder and the lymph channels of the legs:[7]
- Bladder problems. Some of the nerves that control the bladder run through the tissue that is removed. Some women have trouble emptying the bladder and need a catheter for a while after surgery.[7] In the SHAPE trial, about 1 in 10 women still had trouble emptying the bladder after the first month.[8] For many it improves over time. “Nerve-sparing” techniques aim to reduce this.
- Lymphedema. Removing lymph nodes can cause long-term swelling in the legs. It is not common, but tell your team early if you notice swelling, because treatment works best when started early.[7]
- A shorter vagina. Because the upper vagina is removed, the vagina is shorter. The ability to feel sexual pleasure does not change: the lining of the vagina and the area around the clitoris keep their sensitivity.[7]
- Infertility. Removing the uterus means pregnancy is no longer possible.
If radiation is also needed after surgery, its own side effects are added: bladder and bowel irritation, narrowing of the vagina and possible early menopause.[11]
Chemoradiation: the main alternative to surgery
For larger and more advanced cancers, and for women who cannot have surgery, the standard treatment is chemoradiation: external radiation to the pelvis given together with low-dose chemotherapy (usually cisplatin), followed by brachytherapy, in which a radiation source is placed inside the vagina and cervix for short periods.[4] For some high-risk stage III and IVA cancers, the immunotherapy drug pembrolizumab may be added.[4]
Short-term side effects include tiredness, diarrhea, nausea and lower blood counts, which usually improve in the weeks after treatment. Longer-term effects can include narrowing and shortening of the vagina, bladder irritation, bowel changes and early menopause.[11] Regularly stretching the vagina with a dilator, or through sexual activity, helps prevent narrowing.[11] A hysterectomy after chemoradiation is possible for some women but uncommon.[4]
Recovery after surgery for cervical cancer
Recovery depends on the type of operation. After a laparoscopic or vaginal simple hysterectomy, most women stay in hospital for 1 to 2 days and recover over 2 to 3 weeks. After an abdominal hysterectomy, the stay is typically 3 to 5 days and full recovery takes about 4 to 6 weeks.[7] A radical hysterectomy usually means a longer stay, and recovery can take longer, especially if you go home with a catheter.
Our week-by-week recovery guide covers walking, driving, lifting, work and sex in detail.
When to call your care team
- Fever, chills, or a wound that becomes red, hot, swollen or starts to leak
- Heavy vaginal bleeding, or a discharge that smells bad
- Being unable to pass urine, or pain and burning that does not settle
- Pain, swelling or redness in one leg, or sudden shortness of breath or chest pain (call emergency services)
- Severe pain that is getting worse instead of better
Outlook and follow-up
Cervical cancer found early has a good outlook. According to US national cancer data, five-year relative survival is about 92% when the cancer is still confined to the cervix, 64% when it has spread to nearby tissue or lymph nodes, and 21% when it has spread to distant organs.[12] These figures are averages from people diagnosed years ago; they cannot predict what will happen to any one person, and treatment keeps improving.
After treatment you will have regular check-ups, usually more often in the first few years. These visits may include a pelvic examination and, depending on your treatment, tests of cells from the top of the vagina. Women treated for cervical cancer or a high-grade precancer still need follow-up testing after a hysterectomy.[13] Our guide to Pap smears after hysterectomy explains what that testing involves, and our article on vaginal cancer after hysterectomy covers a related, rarer cancer.
Hysterectomy for other reasons and cervical cancer risk
Two common questions come up for women who have a hysterectomy for a benign condition:
- If your cervix was removed (total hysterectomy) for a non-cancerous reason, and you never had a high-grade precancer or cervical cancer, you no longer need cervical screening.[13]
- If your cervix was kept (partial or supracervical hysterectomy), you can still develop cervical cancer, so you need to keep going for regular cervical screening.[14]
A hysterectomy is not done to prevent cervical cancer in healthy women. Prevention relies on HPV vaccination and screening. In a nationwide Swedish study, girls vaccinated against HPV before the age of 17 had an 88% lower risk of invasive cervical cancer than unvaccinated women.[15]
Questions to ask your care team
- What stage and type of cancer do I have, and how sure are we of the stage?
- Is surgery or chemoradiation the better option for me, and why?
- Do I fit the low-risk criteria for a simple hysterectomy instead of a radical one?
- Will the operation be open or minimally invasive? If minimally invasive, why?
- Will you use sentinel lymph node mapping?
- Can my ovaries be kept? Is there a way to preserve my fertility?
- How likely am I to need radiation after surgery?
- How many radical hysterectomies does your team perform each year?
- What support is available for bladder, sexual and emotional recovery?
For a broader look at the conditions that lead to a hysterectomy, see our guide to the reasons for a hysterectomy, and for the basics of the operation itself, our overview of what a hysterectomy involves.
Sources
- World Health Organization. Cervical cancer (fact sheet). Updated 2026. who.int
- American Cancer Society. Key statistics for cervical cancer. cancer.org
- NHS. Symptoms of cervical cancer. nhs.uk
- American Cancer Society. Treatment options for cervical cancer, by stage. cancer.org
- Bhatla N, Berek JS, Cuello Fredes M, et al. Revised FIGO staging for carcinoma of the cervix uteri. International Journal of Gynecology & Obstetrics. 2019;145(1):129–135. pubmed.ncbi.nlm.nih.gov
- Peters WA 3rd, Liu PY, Barrett RJ 2nd, et al. Concurrent chemotherapy and pelvic radiation therapy compared with pelvic radiation therapy alone as adjuvant therapy after radical surgery in high-risk early-stage cancer of the cervix. Journal of Clinical Oncology. 2000;18(8):1606–1613. pubmed.ncbi.nlm.nih.gov
- American Cancer Society. Surgery for cervical cancer. cancer.org
- Plante M, Kwon JS, Ferguson S, et al. Simple versus radical hysterectomy in women with low-risk cervical cancer. New England Journal of Medicine. 2024;390(9):819–829. pubmed.ncbi.nlm.nih.gov
- Ramirez PT, Frumovitz M, Pareja R, et al. Minimally invasive versus abdominal radical hysterectomy for cervical cancer. New England Journal of Medicine. 2018;379(20):1895–1904. pubmed.ncbi.nlm.nih.gov
- Melamed A, Margul DJ, Chen L, et al. Survival after minimally invasive radical hysterectomy for early-stage cervical cancer. New England Journal of Medicine. 2018;379(20):1905–1914. pubmed.ncbi.nlm.nih.gov
- American Cancer Society. Radiation therapy for cervical cancer. cancer.org
- National Cancer Institute, SEER Program. Cancer stat facts: cervical cancer. seer.cancer.gov
- US Preventive Services Task Force. Cervical cancer: screening. Final recommendation statement, 2018. uspreventiveservicestaskforce.org
- NHS. Hysterectomy: considerations. nhs.uk
- Lei J, Ploner A, Elfström KM, et al. HPV vaccination and the risk of invasive cervical cancer. New England Journal of Medicine. 2020;383(14):1340–1348. pubmed.ncbi.nlm.nih.gov
This article is for general information and is not a substitute for medical advice. Treatment for cervical cancer depends on the stage and type of cancer, your health and your plans for the future, so always discuss your options with your own doctor or gynecologic oncologist.